UNITED STATES
SECURITIES AND EXCHANGE COMMISSION
Washington, D.C. 20549
FORM 10-K
| ANNUAL REPORT PURSUANT TO SECTION 13 OR 15(d) OF THE SECURITIES EXCHANGE ACT OF 1934 | |||||
For the fiscal year ended December 31 , 2025
OR
| TRANSITION REPORT PURSUANT TO SECTION 13 OR 15(d) OF THE SECURITIES EXCHANGE ACT OF 1934 | |||||
For the transition period from _________ to ___________
Commission file number 001-41346
(Exact name of registrant as specified in its charter)
| (State or other jurisdiction of incorporation or organization) | (I.R.S. Employer Identification No.) | ||||
(Address and zip code of principal executive offices)
Telephone Number (713 ) 660-0557
(Registrant's telephone number, including area code)
Securities registered pursuant to Section 12(b) of the Act:
| Title of each class | Trading Symbol | Name of each exchange on which registered | ||||||||||||
The | ||||||||||||||
Securities registered pursuant to Section 12(g) of the Act: None
Indicate by check mark if the registrant is a well-known seasoned issuer, as defined in Rule 405 of the Securities Act. Yes o No þ
Indicate by check mark if the registrant is not required to file reports pursuant to Section 13 or Section 15(d) of the Act. Yes o No þ
Indicate by check mark whether the registrant (1) has filed all reports required to be filed by Section 13 or 15(d) of the Securities Exchange Act of 1934 during the preceding 12 months (or for such shorter period that the registrant was required to file such reports), and (2) has been subject to such filing requirements for the past 90 days. Yes þ No o
Indicate by check mark whether the registrant has submitted electronically every Interactive Data File required to be submitted pursuant to Rule 405 of Regulation S-T (§ 232.405 of this chapter) during the preceding 12 months (or for such shorter period that the registrant was required to submit such files). Yes þ No o
Indicate by check mark whether the registrant is a large accelerated filer, an accelerated filer, a non-accelerated filer, smaller reporting company, or an emerging growth company. See the definitions of “large accelerated filer,” “accelerated filer,” “smaller reporting company,” and “emerging growth company” in Rule 12b-2 of the Exchange Act.
| Large accelerated filer | o | þ | ||||||||||||
| Non-accelerated filer | o | Smaller reporting company | ||||||||||||
| Emerging growth company | ||||||||||||||
If an emerging growth company, indicate by check mark if the registrant has elected not to use the extended transition period for complying with any new or revised financial accounting standards provided pursuant to Section 13(a) of the Exchange Act. o
Indicate by check mark whether the registrant has filed a report on and attestation to its management's assessment of the effectiveness of its internal control over financial reporting under Section 404(b) of the Sarbanes-Oxley Act (15 U.S.C. 7262(b)) by the registered public accounting firm that prepared or issued its audit report. þ
If securities are registered pursuant to Section 12(b) of the Act, indicate by check mark whether the financial statements of the registrant included in the filing reflect the correction of an error to previously issued financial statements. o
Indicate by check mark whether any of those error corrections are restatements that required a recovery analysis of incentive-based compensation received by any of the registrant’s executive officers during the relevant recovery period pursuant to §240.10D-1(b). o
Indicate by check mark whether the registrant is a shell company (as defined in Rule 12b-2 of the Act). Yes o No þ
The aggregate market value of voting common stock held by non-affiliates at June 30, 2025 was approximately $524.0 million. At March 2, 2026, there were 6,968,350 shares of common stock outstanding.
DOCUMENTS INCORPORATED BY REFERENCE
Portions of the registrant’s definitive proxy statement for its 2026 Annual Meeting of Shareholders (the “Proxy Statement”) are incorporated by reference into Part III of this Annual Report on Form 10-K and will be filed within 120 days of the registrant’s fiscal year end.
INTRODUCTORY NOTE
Unless the context dictates otherwise, references in this Annual Report on Form 10-K to “Nutex,” the “Company,” “we,” “us,” “our,” and similar words are references to Nutex Health Inc., a Delaware corporation, and its consolidated subsidiaries and affiliated entities, as appropriate, including its consolidated variable interest entities (“VIEs”) and “Nutex” refers to Nutex Health Inc.
On April 9, 2024, the Company effected a 1-15 reverse stock split and on July 2, 2024, the Company effected an additional 1-10 reverse stock split, or an aggregate of 1-150 (together, the “2024 Reverse Stock Splits”).
Unless otherwise indicated, all authorized, issued, and outstanding stock and per share amounts referred to in this Annual Report on Form 10-K have been adjusted to reflect the 2024 Reverse Stock Splits for all prior periods presented. Proportionate adjustments for the 2024 Reverse Stock Splits were made to the exercise prices and number of shares issuable under the Company’s equity incentive plans, and the number of shares underlying outstanding equity awards, as applicable. See Note 1 - Organization and Operations for information and disclosures relating to adjustments related to the 2024 Reverse Stock Splits.
CAUTIONARY NOTE REGARDING FORWARD-LOOKING STATEMENTS
This Annual Report contains “forward-looking statements” within the meaning of Section 27A of the Securities Act of 1933, as amended (the “Securities Act”), and Section 21E of the Securities and Exchange Act of 1934, as amended (the “Exchange Act”). We intend such forward-looking statements to be covered by the safe harbor provisions for forward-looking statements contained in the Private Securities Litigation Reform Act of 1995 and include this statement for purposes of complying with these safe harbor provisions.
This document contains certain forward-looking statements with respect to our financial condition, results of operations and business, plans, objectives and strategies. These forward-looking statements can be identified by the fact that they do not relate only to historical or current facts. Forward-looking statements often use words such as “estimate,” “project,” “predict,” “will,” “would,” “should,” “could,” “may,” “might,” “anticipate,” “plan,” “intend,” “believe,” “expect,” “aim,” “goal,” “target,” “objective,” “commit,” “advance,” “likely” or similar expressions that convey the prospective nature of events or outcomes.
These forward-looking statements reflect our current views with respect to future events and are based on numerous assumptions and assessments made by us in light of our experience and perception of historical trends, current conditions, business strategies, operating environments, future developments and other factors we believe appropriate. By their nature, forward-looking statements involve known and unknown risks and uncertainties because they relate to events and depend on circumstances that will occur in the future. The factors described in the context of such forward-looking statements in this document could cause our plans, actual results, performance or achievements, industry results and developments to differ materially from those expressed in or implied by such forward-looking statements. Although we believe that the expectations reflected in such forward-looking statements are reasonable, we cannot assure you that such expectations will prove to have been correct and persons reading this document are therefore cautioned not to place undue reliance on these forward-looking statements, which speak only as of the date of this Annual Report. We do not assume any obligation to update the information contained in this document (whether as a result of new information, future events or otherwise), except as required by applicable law.
i
NUTEX HEALTH INC.
FORM 10-K FOR THE YEAR ENDED DECEMBER 31, 2025
TABLE OF CONTENTS
| Page | ||||||||
PART I
Item 1. Business
Overview
Nutex Health Inc. (“Nutex Health” or the “Company”) is a physician-led, healthcare services and operations company with 26 hospital facilities (as of December 31, 2025) in 12 states (hospital division), and a primary care-centric, risk-bearing population health management division. Our hospital division implements and operates innovative health care models, including micro-hospitals, specialty hospitals and hospital outpatient departments (“HOPDs”). The population health management (“PHM”) division owns and operates provider networks such as independent physician associations (“IPAs”).
We employ 944 full-time employees, contract more than 280 doctors at our facilities and partner with over 3,600 physicians and specialists within our IPA networks. Our corporate headquarters is based in Houston, Texas. We were incorporated on April 13, 2000 in the state of Delaware.
Operating Segments
We report the results of our operations as three segments: (i) the hospital division, (ii) the PHM division, and (iii) the real estate division.
Hospital Division. Our hospital division develops and operates a network of micro-hospitals, specialty hospitals and HOPDs providing comprehensive and high-quality 24/7 care. Our full-service care delivery model provides concierge-level care traditionally offered by larger hospitals in a patient-friendly and cost-effective setting. We provide a full spectrum of healthcare services, including emergency room care, inpatient care, and behavioral health, and offer a complementary suite of ancillary services, including onsite imaging (CT scan, X-ray, MRI, ultrasound, etc.), certified and accredited laboratories, and onsite inpatient pharmacies. As of December 31, 2025, we owned and operated 26 healthcare facilities across 12 states and had an additional nine de novo micro-hospitals under various stages of development.
Our micro-hospitals generate revenue from both emergency services and in-patient services, providing operating leverage and significant earning potential at each facility. We believe that wait times at our hospitals are significantly lower than traditional ER settings and patients are welcomed by a friendly attentive staff and physician team. Our hospital division generally operates as an out-of-network provider and, as such, does not have negotiated reimbursement rates with most insurance companies. Our patients with commercial insurance coverage have historically applied out of network benefits and patient co-pays to settle invoices. In the future, we expect to contract directly with more commercial payors whose reimbursement rates for our services are more closely aligned with the value offered.
When developing new hospitals, we provide a turn-key process from location selection, real estate design, and development of the facility to staffing, training and operations. Our corporate management and administrative teams provide a comprehensive suite of operational and managerial services to our hospitals, including management, billing, collections, human resources and recruiting, legal, accounting, regulatory, legislative and marketing / business development. Most of our licensed micro-hospitals average approximately 15,000 to 25,000 square feet and include seven to eight emergency treatment rooms, two to ten in-patient beds for both short- and long-term stays and advanced imaging equipment, laboratory and pharmacy services. Our staffing at each facility includes four to ten physicians and hospitalists depending on the community’s needs.
Most of our hospitals have contractual relationships with separately owned professional entities (the “Physician LLCs”) and real estate entities (the “Real Estate Entities”). The Physician LLCs employ the doctors who work in our hospitals. The Real Estate Entities, which generally have the same ownership as the related Physician LLCs, own the land and hospital buildings in which the hospitals operate and lease the buildings to the hospitals. We have no ownership interest in any of the Physician LLCs and have a 51% interest in one of the Real Estate Entities, but provide back office accounting for each. Many of these entities are owned in part, and in some cases controlled, by our Chairman and Chief Executive Officer.
The Physician LLCs are consolidated by the Company as variable interest entities (VIEs) because they do not have significant equity at risk, and we have historically provided support to the Physician LLCs in the event of cash shortages and received the benefit of their cash surpluses.
1
Population Health Management Division. Our population health management division establishes and operates provider networks such as IPAs. Through its Management Services Organization (“MSO”), Nutex provides management, administrative, and other support services to its affiliated hospitals and physician groups.
An IPA is a business entity organized and owned by a network of independent physician practices. Once established, the IPA enrolls patients and negotiates managed care contracts with insurers to provide comprehensive care to their patients, often for a value-based fixed annual fee known as a capitated rate. The IPA entities are not owned by us, but are managed by our MSO which provides management, administrative, and other support services. Presently, we manage one IPA located in Los Angeles, California with over 230 primary care physicians ("PCPs"), 2,800 specialists and ancillary providers and an enrollment of approximately 32,750 patients. We have established three other IPAs, one each in Houston, South Florida and Phoenix. As of the date of this filing, our Houston IPA has over 90 contracted PCPs, 320 specialists and manages over 1,900 Medicare Advantage (“MA”) patients. Our South Florida IPA is contracted with approximately 90 PCPs and manages over 3,700 members, including over 250 MA patients. Our Phoenix IPA is contracted with 19 PCPs and 60 specialists. In total, the Company’s IPAs now have approximately 38,000 members across their platform, including commercial and Medicaid managed care members. We consolidate the IPA entities in our financial statements as VIEs since we manage these entities.
Real Estate Division. The Real Estate Entities own the land and hospital buildings which are leased to our hospital entities. One Real Estate Entity owns the Company's headquarters building. The Real Estate Entities have mortgage loans payable to third parties which are collateralized by the land and buildings. We own 100% of the Company's headquarters building purchased in December 2025. In addition, we purchased 51% ownership of an Indiana-based micro-hospital facility. Other than the aforementioned properties, we do not have direct ownership interest in these entities, which are owned and, in some instances, controlled by related parties, including our CEO. We consolidate the Real Estate Entities we do not have direct ownership in as VIEs in instances where our hospital entities are guarantors or co-borrowers under their outstanding mortgage loans. Since the second quarter of 2022, we deconsolidated 18 Real Estate Entities after the third-party lenders released our guarantees of associated mortgage loans, leaving two Real Estate Entities we do not directly own as current VIEs consolidated in our financial statements.
Sources of Revenue
The following table shows revenue for each of our operating segments (in thousands):
Year Ended December 31, | |||||||||||||||||
2025 | 2024 | 2023 | |||||||||||||||
Hospital division revenue | $ | 844,162 | $ | 449,064 | $ | 218,070 | |||||||||||
Population health management division revenue | 31,095 | 30,885 | 29,576 | ||||||||||||||
Total revenue | $ | 875,257 | $ | 479,949 | $ | 247,646 | |||||||||||
Our hospital division receives payment for facility services rendered by us from federal agencies, private insurance carriers, and patients. The Physician LLCs receive payment for doctor services from these same sources. On average, greater than 99% of our net patient service revenue is paid by insurers, federal agencies, and other non-patient third parties. The remaining revenues are directly paid by our patients in the form of copays, deductibles, and self-payment. As noted, we generally operate as an out-of-network provider and, as such, do not have negotiated reimbursement rates with most insurance companies.
The population health management division recognizes revenue for capitated payments and management fees for services to IPAs and physician groups monthly. Capitation revenue consists primarily of capitated fees for medical services provided by physician-owned entities we consolidate as VIEs. Capitated arrangements are made directly with various managed care providers including HMOs. Capitation revenues are typically paid to us monthly in the period services are provided based on the number of enrollees selecting us as their healthcare provider. Capitation is a fixed payment amount per patient per unit of time paid in advance for the delivery of health care services, whereby the service providers are generally liable for excess medical costs. We receive management fees that are based on gross capitation revenues of the IPAs or physician groups we manage.
2
Our Strategy
Our mission is to make exceptional concierge-level healthcare more accessible to people in the communities we serve. Our business strategy is to increase stockholder value through earnings growth and cash flow generation by:
•Developing and operating innovative micro-hospitals – We currently operate 26 micro-hospital facilities in 12 states and four IPAs. We plan to grow our operations by expanding our innovative micro-hospital model into additional states and developing IPAs which leverage our presence and physician relationships in each community we serve.
•Providing a patient-centric care model – We fulfill the healthcare needs of patients seeking immediate and convenient access to primary and emergency care. Producing a compelling work environment for physicians helps us deliver superior patient experiences and clinical outcomes.
•Offering a differentiated provider engagement and partnership strategy – Having high satisfaction and retention rates of physicians helps us in delivering superior patient experiences. Financially, we are aligned with our physician partners who are co-investors with us in their community’s micro-hospitals or IPAs and, in many instances, are stockholders of Nutex. Our relationships with physician partners are critical to our success.
•Having a scalable go-to-market strategy – Robust administrative support where key support functions including billing and collection, purchasing, marketing, legal and compliance, human resources and financial operations are centralized, allowing our physicians and hospitalists to focus on patient care. Building out IPA networks in the same communities as our micro-hospitals helps drive patient volume and results in greater revenue from increased capitation and full-risk contracts. To complement our organic growth plans, we may, in the normal course of business, consider and review opportunistic acquisitions.
Our Growth Strategy
We are focused on expanding patient access to quality healthcare by broadening our clinical services at existing facilities and by opening or acquiring new micro-hospital facilities in high demand areas of the United States. We are also seeking to establish IPAs in many of the locales where we operate micro-hospitals in order to leverage our community presence and relationships with in-market physicians.
We expect to open four new hospital facilities in 2026. These facilities are either under construction or in advanced planning stages. We anticipate launching one to three additional IPAs per year, principally in geographic areas around our existing micro-hospitals. There is no guarantee that any or all of the planned new hospitals or new IPAs will be successfully launched in the anticipated time frames.
3
The following map shows our existing and planned presence across the United States:
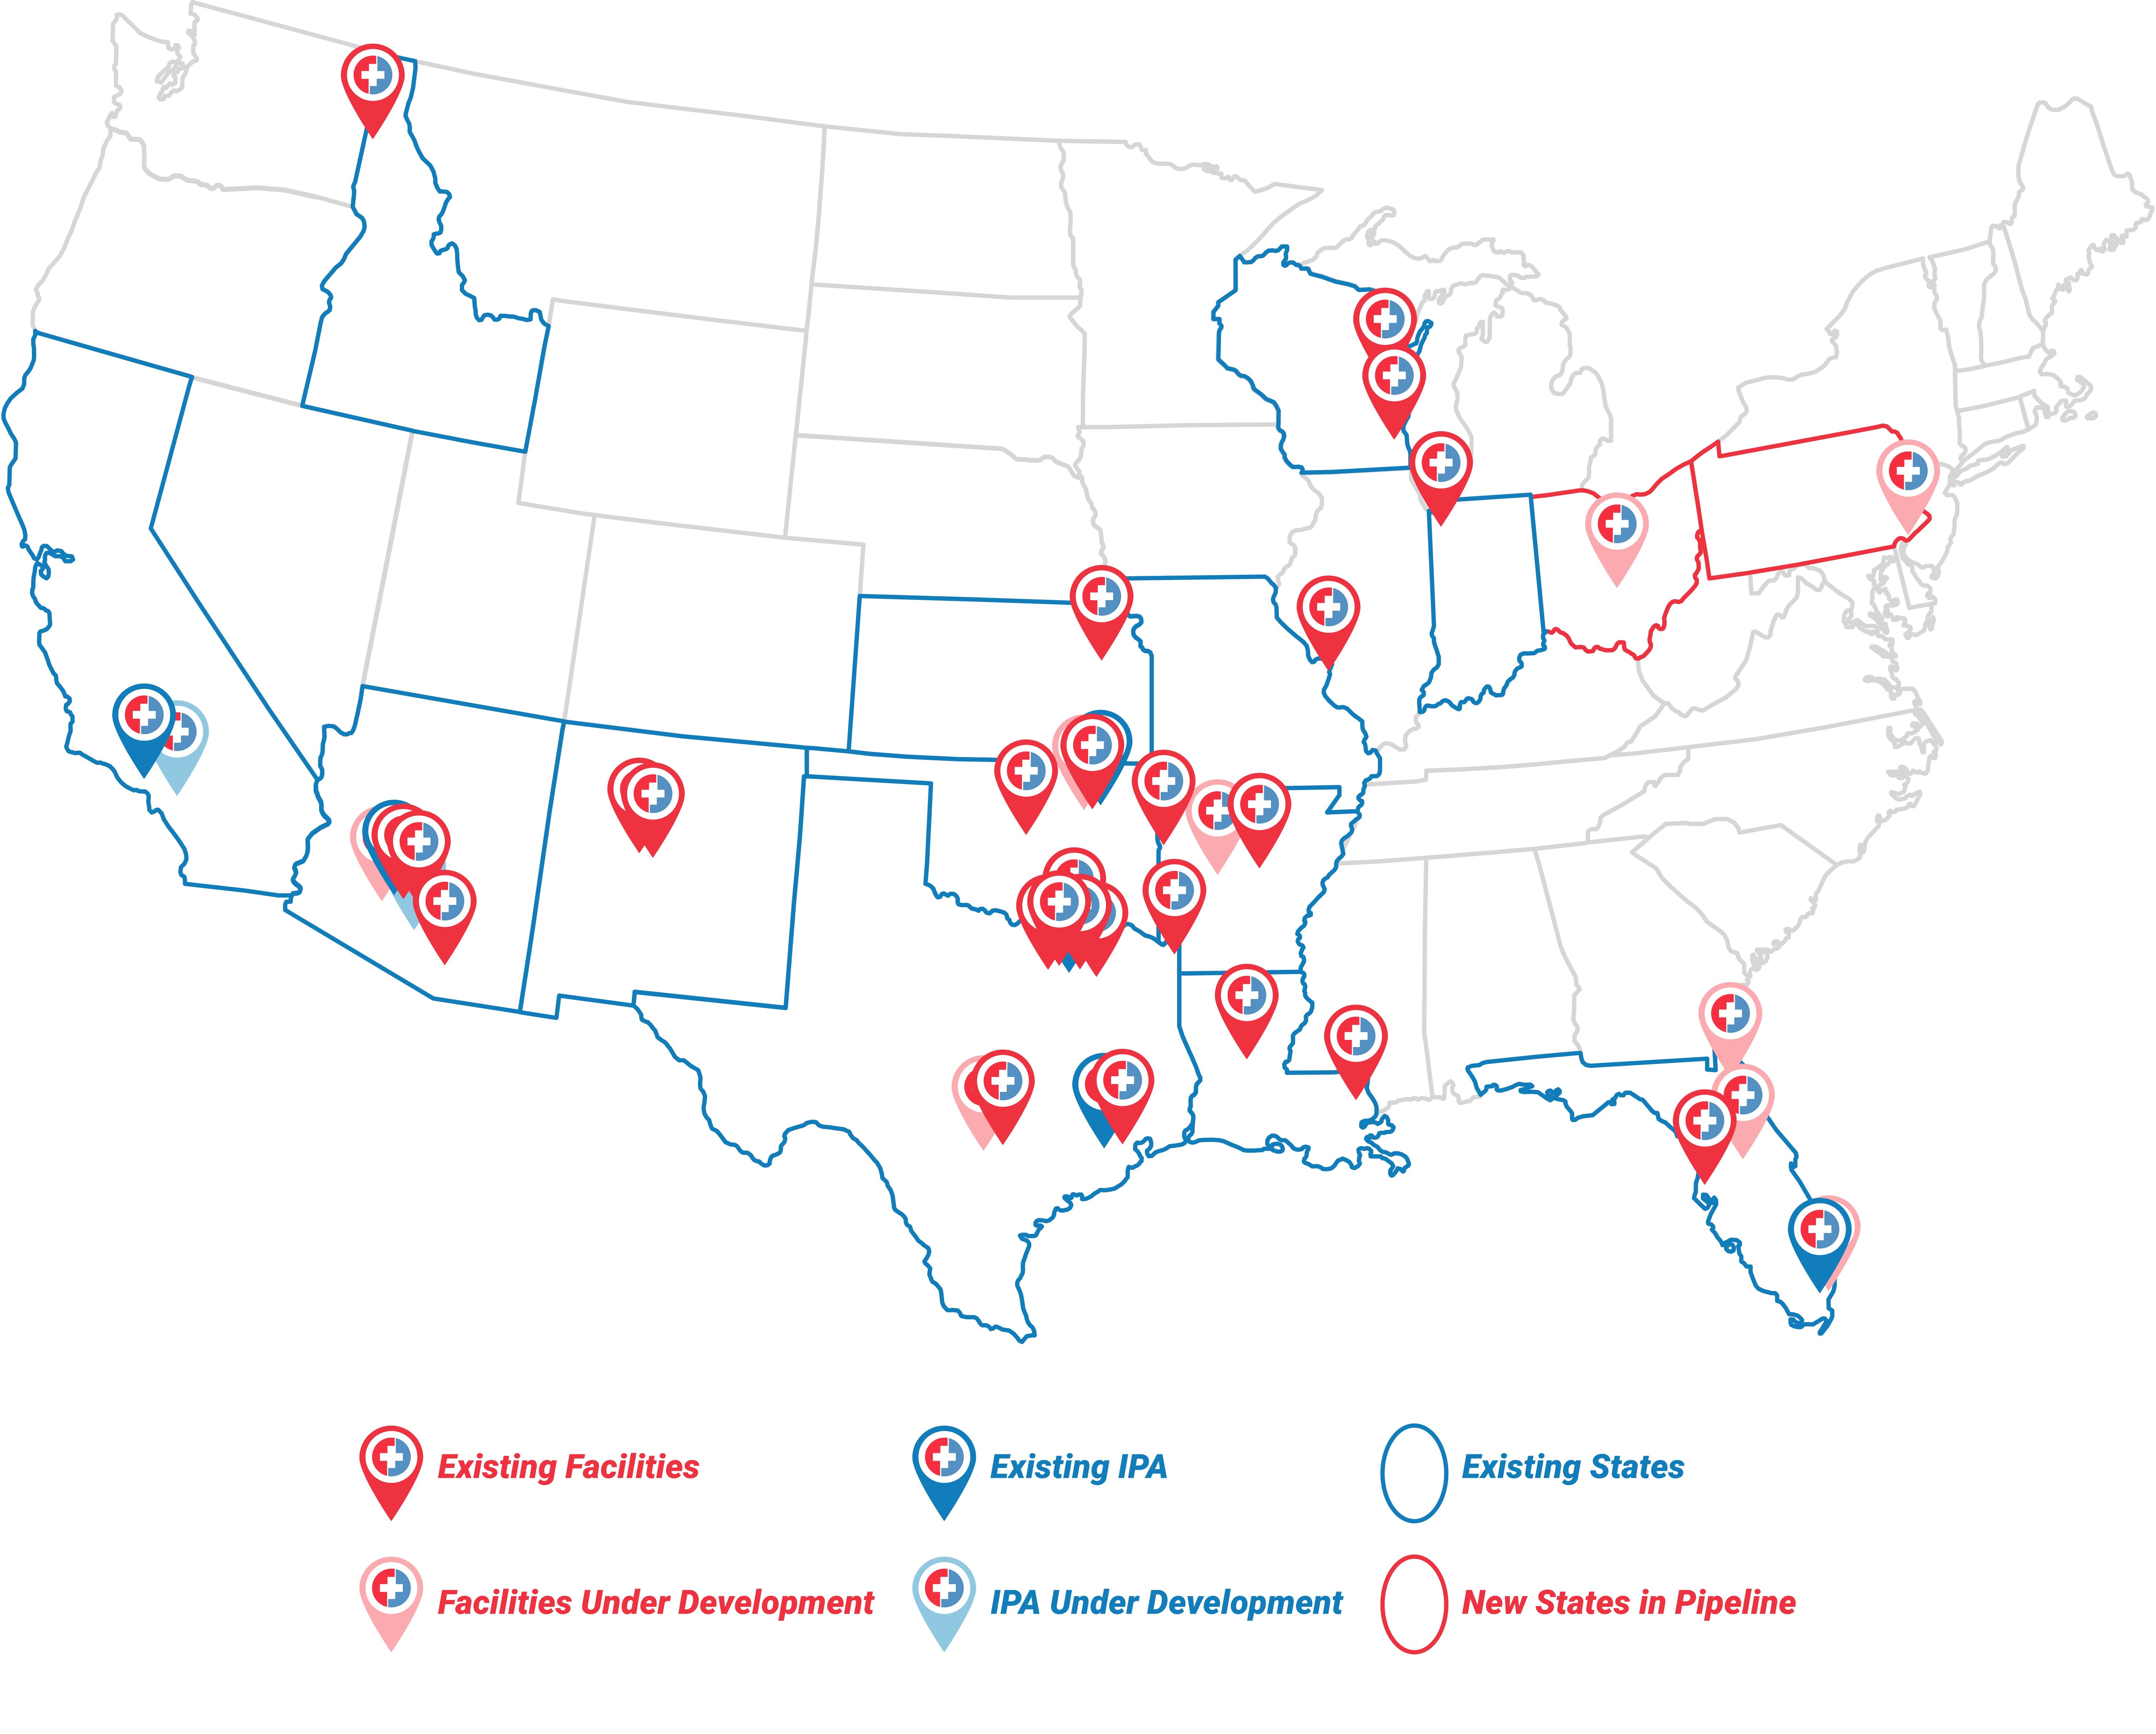
Our process for opening a new micro-hospital begins with identifying high demand markets. Generally, we place our micro-hospitals in larger suburban or rural locations. Before entering a new state, we investigate the regulation and licensing requirements for our business and the construction design and permitting requirements of the targeted community. Next, we identify and contract with in-market physicians who will co-invest with us and become the on-site management of the new facility.
For each new hospital location, three entities are usually created:
•Real estate entity – our hospital facilities are designed and constructed to meet our specific needs and governmental regulations for micro-hospitals. Construction of new facilities or major renovation of existing buildings to meet our specifications requires significant financial resources. In most cases, these financial resources are provided by a newly established real estate entity that is independently owned by the in-market physicians and other partners, including in many cases, members of our executive management team. The real estate entities often enter into mortgage loans to finance the acquisition of the associated land or the build out of facilities. In some instances, Nutex may participate as a co-borrower or guarantor of this indebtedness. Nutex does not own any of the real estate entities, but enters into a long-term market rate lease of the facility for its operations with the real estate entity. Nutex also contracts with this entity to provide administrative services, including financial accounting and other responsibilities.
•Physician LLC entity – the in-market physicians create and independently own the physician entity. In certain states, state laws and regulations prohibit non-physician ownership of physician practices. The physician entity employs or contracts with physicians who staff the new location. We contract with the physician entities to
4
provide administrative services, including claims billing and collections, financial accounting and other responsibilities.
•Hospital facility entity – Nutex typically has 60% or more equity ownership of new hospital facilities and in-market physicians usually own much of the remaining equity. The participation by in-market physicians in owning the hospital facility is a key factor in our success. The hospital facility contracts with the physician entity to provide physician staffing and enters into a lease of the physical facility with the associated real estate entity. The hospital facility provides the operating equipment and supplies and employs nursing and other staffing for local operations.
Our relationships with physician partners are critical to our success. The physician partners’ financial participation through ownership in whole, or in part, of the above entities aligns our interests towards achieving common business goals and helps us target a high satisfaction and retention rate of physicians.
Having good physician relationships is also fundamental to our success in developing and operating IPAs. We begin development of new IPAs by identifying underserved markets. As noted previously, we are focused on launching IPAs in markets around our micro-hospitals. Doing so leverages our existing physician relationships and increases visibility of our micro-hospitals in the marketplace. Once the physician provider network is secured, we work to contract with health insurance plans and begin enrolling patients in the new IPA.
We may achieve our growth strategy in part by acquiring or contracting existing healthcare facilities and IPAs. We currently have an IPA presence in the top three states for seniors: California, Florida, and Texas, which make up a quarter of the nation’s seniors.
Competition
The healthcare industry is highly competitive and highly fragmented. We face competition in every aspect of our business, including in offering a favorable payment structure for existing physician partners and attracting physician partners who are not contracted with us, from a range of large and medium-sized local and national companies that provide care under a variety of models that could attract patients, providers, and payors. Our primary competitors are free-standing emergency departments and traditional large local hospital systems that are developing micro-hospitals to increase their footprint in their local communities. Our competitors typically vary by geography, and we may also encounter competition in the future from other new entrants.
Since there are no substantial capital expenditures required for providing healthcare services, as facilities and equipment may be leased, there are few financial barriers to entry. Other companies or hospital groups could enter the micro-hospital market in the future and divert some, or all, of our business. Our ability to compete successfully varies from location to location and depends on a number of factors that include, but are not limited to, the number of competing facilities in the local market and the types of services available at those facilities, our local reputation for quality care of members, the commitment and expertise of our medical staff, our local service offerings and community programs, the cost of care in each locality, and the physical appearance, location, age and condition of our facilities.
Our growth strategy and our business could be adversely affected if we are not able to continue to operate in existing geographies, successfully expand into new geographies or maintain or establish new relationships with physician partners. See “Risk Factors.”
The principal competitive factors in our business include the nature and caliber of relationships with physicians; patient healthcare quality, outcomes, and cost; the strength of relationships with payors; the quality of the physician experience; local geography leadership position; and the strength of the underlying economic model. We believe our business, partnership and operations model enables us to compete favorably.
The Healthcare Industry
According to the Centers for Medicare & Medicaid Services, or CMS, national healthcare expenditures grew 7.2% in 2024 to $5.3 trillion. Federal expenditure for healthcare increased by 5.5% due to the initial impacts of the Inflation Reduction Act on federal Medicare spending and faster spending growth for Medicare hospital and physician spending, while private health insurance spending increased by 8.8%. CMS anticipates that total U.S. healthcare annual expenditures will account for approximately 20.3% of the total U.S. gross domestic product by 2033.
5
Hospital services, the market within the healthcare industry in which we primarily operate, is the largest single category of healthcare expenditures. In 2024, hospital care expenditures increased 9.2% from the previous year and totaled about $1.7 trillion. CMS projects that the hospital services category will grow at an average of 5.5% annually from 2028 through 2033, reaching nearly $2.7 trillion by 2033.
The U.S. hospital industry includes acute care, rehabilitation and psychiatric facilities that are either public (government owned and operated), not-for-profit private (religious or secular), or for-profit institutions (investor owned). According to the American Hospital Association, there are approximately 5,112 community hospitals in the U.S., which are not-for-profit owned, investor owned, or state or local government owned. Of these hospitals, approximately 35% are located in non-urban communities. Hospital facilities offer a broad range of healthcare services, including internal medicine, general surgery, cardiology, oncology, orthopedics, OB/GYN and emergency services. In addition, hospitals offer other ancillary services, including psychiatric, diagnostic, rehabilitation, home care and outpatient surgery services.
Patients needing the most complex care are more often served by larger and/or more specialized urban hospitals. We believe opportunities exist in selected markets to create micro-hospitals serving the community’s emergency medical needs which expand the reach of healthcare services and have lower wait times for care than often seen in larger hospital emergency departments.
Physician and clinical services expenditures grew 7.4% to $978.0 billion in 2023, faster growth than the 4.6% in 2022. Relative spending for primary care in the U.S. is lower than that of many other developed nations. Preventative primary care is an important focus of U.S. healthcare education to consumers with the goal of improving patient care outcomes through early detection and treatment of illnesses. It also has the added benefit of reducing healthcare costs as extended hospital stays and more costly treatments may be avoided.
Consumers desire affordable primary care with access to specialists as needed. We believe this need may be met in markets we service through our IPAs. Our IPAs offer a trusted network of primary care physicians and specialists fostering closer patient-physician relationships.
Governmental Regulation
The healthcare industry is heavily regulated and closely scrutinized by federal, state and local governments. Comprehensive statutes and regulations govern the manner in which we provide and bill for services and collect reimbursement from governmental programs and private payors, our contractual relationships with our providers, vendors and clients, our marketing activities and other aspects of our operations. Of particular importance are:
•No Surprises Act;
•the federal physician self-referral law, commonly referred to as the Stark Law;
•the federal Anti-Kickback Act;
•the criminal healthcare fraud provisions of the Health Insurance Portability and Accountability Act (HIPAA);
•the federal False Claims Act;
•reassignment of payment rules that prohibit certain types of billing and collection;
•similar state law provisions pertaining to anti-kickback, self-referral and false claims issues;
•state laws that prohibit general business corporations, such as us, from practicing medicine; and
•laws that regulate debt collection practices as applied to our debt collection practices.
Arbitration process
Federal Rules Applicable to Out-of-Network Billing
Congress enacted the No Surprises Act (“NSA”) effective January 1, 2022, to protect patients from surprise medical bills incurred when they receive emergency medical services from out-of-network healthcare providers, as well as non-emergency services at in-network facilities, and air ambulance services. The NSA achieves this by relieving patients from financial liability for surprise bills and creating an Independent Dispute Resolution (“IDR”) process for billing disputes between providers and insurers. The patient is not involved in this process, and payment is issued directly to the provider. The IDR process safeguards providers by promoting fair reimbursement from payors, helping ensure their continued ability to deliver care.
6
•Independent Dispute Resolution. Under the IDR provisions, Nutex Health and the insurer first must try to agree on a price for the services. If negotiations fail, either party has four days to initiate IDR proceedings. If the parties pursue IDR, either the parties or the Department of Health and Human Services (“HHS”) selects a certified independent dispute resolution entity (“CIDRE”) to determine the final payment amount.
•Certified Independent Dispute Resolution Entity. The CIDRE has the sole discretion to determine both the eligibility of claims submitted for the IDR process, subject to federal and state regulations, and the amount the payor owes the provider.
•The CIDRE makes a threshold determination of IDR eligibility and sets the payment amount by choosing between the offers of each party; the provider and insurer each submit a final offer, and the CIDRE selects one party’s offer as the award after reviewing and evaluating all statutorily required information submitted by both parties.
•In deciding which offer to award, the CIDRE must consider several factors outlined in the law, only one of which is the insurer’s qualifying payment amount (“QPA”), defined as the “median of the contracted rates recognized by the plan or issuer . . . for the same or a similar item or service” offered in the same insurance market and geographic area. Among the other factors to be considered are the complexity or acuity of the case, the doctor’s expertise, and the scope of services provided at the facility. See also below “Legal Challenges to HHS Final Rule – Federal Court removes restrictions imposed on arbitrators in 2022 HHS final Rules (TMA II).”
•Arbitration Awards Are Binding. In the absence of a fraudulent claim or evidence of a misrepresentation of facts to the CIDRE, the IDR award is binding upon the parties involved and payment of the award must be made not later than 30 days after the date on which the payment determination is made.
•Patients are not involved in open negotiations or the IDR process, and payors must issue any IDR award payments directly to the provider.
•The NSA empowers HHS to assess penalties against insurers for failure to comply with the NSA, including timely payment of CIDRE awards. However, as illustrated by the pending legislation discussed below under “Future Expectations,” significant enforcement gaps remain in the current law.
•Reopening of Disputes Closed Prior to June 6, 2025 Only for CIDRE Clerical, Jurisdictional or Procedural Errors. On June 6, 2025 HHS published a Technical Assistance allowing the reopening of arbitration cases closed prior to June 6, 2025 solely for clerical, jurisdictional or procedural errors by the CIDRE. Errors by the parties or substantive disputes among the parties, in particular, with respect to the qualifying payment amount and related statutorily prescribed factors, will not result in a reopening. In addition, HHS has increased the number of CIDREs from 13 to 16 and updated the federal submission portal with respect to, among other things, service-code modifier fields, duplicate-dispute validation, and resubmission rules.
•Legal challenges to HHS Final Rule. The final rule has been the subject of multiple legal challenges. Beginning in September 2022, the Texas Medical Association (“TMA”) filed several actions in federal court in Texas, seeking, among other things, to invalidate the IDR related provisions of the final rule.
•Federal Court vacates 2021 HHS interim final rules to ensure fair and accurate rates (TMA III). On November 30, 2022, the TMA filed a lawsuit challenging the methodology of the federal regulator’s calculation of the QPA. The interim final rules allowed consideration of all negotiated rates, including those provided in contracts with providers who do not actually provide the particular service (ghost rates). On August 24, 2023, the federal district court vacated several aspects of the regulations mandating the methodology for the QPA calculation. On October 30, 2024, the United States Court of Appeals for the Fifth Circuit (“Fifth Circuit”) reversed the district court’s vacatur of the QPA calculation methodology. However, on December 17, 2024, the Fifth Circuit ordered that the mandate be withheld and on May 30, 2025 vacated the previous opinion and held an en banc oral argument on September 24, 2025. No final en banc opinion has been issued. We cannot predict how such final opinion will affect the QPA calculation or the opinion’s impact on out-of-network payments awarded in the IDR process.
•Federal Court removes restrictions imposed on arbitrators in 2022 HHS final rules (TMA II).
On August 2, 2024, the Fifth Circuit upheld a ruling by district court disallowing provisions of the federal rules established under the NSA which would have required arbitrators (i) to prioritize the insurer established QPA over any of the other factors listed below and (ii) to justify in writing the arbiter’s reliance on any factors beyond the QPA. The Fifth Circuit held that the NSA requires that the arbitrator must consider several factors of equal weight in determining the out-of-network rate. These factors include:
7
•The qualifying payment amount, which Congress intended as the median rate the insurer would have paid for comparable services in the same geographic area if provided by an in-network provider or facility;
•The doctor’s level of training;
•the market share of the doctor or insurer in the geographic region;
•the acuity of the patient or the complexity of the case;
•the scope of services of the facility; and
•the good faith efforts (or lack of good faith efforts) made by the out-of-network provider or the plan to enter into network agreements and, if applicable, contracted rates between the parties during the previous four years.
Accordingly, in their payment determination, the CIDREs must consider all factors listed above, including, but not prioritizing, the QPA.
IDR Claims Process
The process for out-of-network claims submitted in the IDR process is subject to the bifurcated nature of many states which have their own surprise billing rules for fully insured claims (and for certain types of providers) and the differing rules governing the determination whether individual claims may be bundled or “batched” when submitting to the CIDRE. As a result, eligibility determinations require involved processes, and Nutex aims to comply with all applicable laws and regulations in each of the jurisdictions in which it operates, including the eligibility rules in effect at the time a claim is being submitted to federal arbitration.
Our claims for out-of-network services are subject to the following federally mandated process once we submit a payment request to the applicable insurance company:
•Initial Payment or Denial. Under the NSA, insurers must issue either an initial payment or a notice of denial to a provider within 30 days after receiving a bill for an out-of-network service.
•Negotiation Period. If the provider disagrees with the insurer’s determination, the provider may initiate a 30-business-day open negotiation period with the insurer regarding the claim.
•IDR Process. If the dispute is not resolved through negotiation, either party may proceed to the IDR process within four business days.
•Payment Timeline. The IDR process is intended to take no more than 30 days, but in practice can take between three to five months before we receive IDR approved and adjusted payments, including the 30 days deadline for the payor to submit payments after the award has been determined.
•Late Payment or Non-Payment. Currently, HHS has the authority to impose financial penalties on payors for late payment or non-payment upon application of the provider. If the No Surprises Enforcement Act is passed and signed into law, payors would face automatic financial penalties for late or non- payment. See “Future Expectations” below.
Effective May 1, 2024, we engaged HaloMD, a third-party tech-enabled expert, to further support our out-of-network claims and determine which claims would be beneficial to arbitrate. HaloMD specializes in independent dispute resolution through the NSA and state regulations for out-of-network healthcare providers. HaloMD verifies the eligibility of claims to be submitted to arbitration. Given the complexity of the federal arbitration process and its interaction with state surprise billing laws, it is crucial for providers like Nutex to seek tech-enabled expert assistance in the highly complex submission process. This third-party expertise, such as that provided by HaloMD, helps the Company navigate the complexity of submission of claims in bifurcated states where either state or federal law may apply, depending on the insurance coverage and services provided.
“Bifurcated” states are states in which some out-of-network services are subject to the federal IDR process and others are subject to a specified state law or all-payer model agreement. The out-of-network services subject to either federal or state jurisdiction differ from state to state, rendering the medical billing process highly complex. HaloMD assists Nutex throughout our arbitration process in the bifurcated states of Texas, Florida, New Mexico, and the non-bifurcated states of Arizona, Arkansas, Idaho, Indiana, Kansas, Louisiana, Oklahoma, and Wisconsin, when we conclude that the payor has not properly paid or underpaid a claim for services as required under the NSA. In that regard, HaloMD works closely with us in navigating the following key areas:
8
•Documentation Submission. Based on the information and data we provide to HaloMD, using a proprietary data driven process, HaloMD submits the required documentation to the CIDRE through the federal portal.
•Eligibility Determination. It is the CIDRE who determines the eligibility of the claims submitted to arbitration based on the information provided through the federal portal. All payors have the right to object to whether the claim is eligible for IDR review or subject to a similar state law dispute resolution process based upon the type of insured member.
•Jurisdictional Eligibility. Jurisdictional eligibility depends on whether a state is “bifurcated,” which means that state laws regarding surprise billing only partially align with federal law.
•State Laws. Certain states have their own surprise billing laws, which must meet specified requirements to take precedence over the federal process but may not cover all claims. In our case, Texas, Florida, and New Mexico are bifurcated states where state law takes precedence for most out-of-network claims.
•Claim Submission. Providers must attest to the best of their knowledge whether a claim falls under state or federal jurisdiction based on the type of insurance plan and the services involved. The CIDRE then determines whether the dispute is eligible to proceed under the federal IDR process. Where applicable, state law procedures and requirements govern the equivalent arbitration process under state law.
•Federal Arbitration Process. Under the federal arbitration process, both the insurer and the provider submit offers indicating the amounts they are willing to pay or receive, respectively. Based on the information submitted through the federal portal, the CIDRE selects either the insurer’s or the provider’s offer to determine the payment.
•Offer Determination. HaloMD, using proprietary data analysis and benchmarking, determines the appropriate offer amount on our behalf.
•Independent Review. The IDR process allows an independent review of a provider’s services and payment requests. Prior to federal arbitration, the insurer had been the sole arbiter of the amount payable for out-of-network services.
•For the first time, independent federal arbitration offers providers a venue to submit claims to an independent arbiter, which we believe has resulted in payments that more accurately reflect fair and reasonable value of the services provided.
•In this fully transparent process, both the payor and the provider submit offers indicating the amounts they are willing to pay or receive, respectively.
•Based on the information submitted through the federal portal by HaloMD, the CIDRE selects either the insurer’s or the provider’s offer to determine the payment.
IDR Industry Trends. According to arbitration data published by the Center for Medicare and Medicaid Services (CMS), CIDREs are making significant progress in improving the overall Federal IDR process:
•From mid-2022 to May 2025, 3,324,051 disputes were filed, a number much higher than anticipated. The regulations implemented under the NSA estimated that the IDR process would annually resolve 17,333 disputes, with an additional 4,899 disputes from air ambulance providers.
•During the fourth quarter of 2024, approximately 85% of disputes were decided in favor of the provider (the higher offer), resulting in a median winning offer of over four times the median in-network rate of each insurer. From January 1 through June 30, 2025, providers prevailed in approximately 88% of payment determinations.
•In its bi-monthly report as of May 31, 2025, CMS reported that between April 15, 2022 and May 31, 2025, the number of disputes closed was 2,831,804, of which 539,664 were found ineligible and 2,152,045 resulted in a payment determination.
•The Federal IDR program dispute closure volume continued to rise month over month in 2025. CIDREs closed 264,805 disputes in May 2025, 8% more than April 2025 (244,705) and 26% more than were initiated in March 2025 (209,637).
Future Expectations. We expect the federal arbitration process for out-of-network services will continue to evolve. On July 23, 2025, the No Surprises Enforcement Act was introduced both in the House and in the Senate and referred to committee, primarily to mandate financial penalties to be imposed on insurers for late payment or non-payment of IDR awards. We cannot predict whether this legislation will be approved and signed into law. Future federal court decisions and regulatory changes may adversely affect our ability to collect the revenue for our services that we believe is fair and reasonable.
Cost of arbitration. There is a significant cost to enter the arbitration process. The arbitration process includes expenses associated with third party providers, including IDR entities, which typically collect fees at the beginning of the process,
9
before the claim award amounts are decided by arbitrators. According to the CMS, as of July 23, 2025, the nonrefundable administrative fee was $115 per party per dispute and the certified IDR entity fee ranged from $375 to $800 for single determinations and $75 to $1,150 for batched determinations. The total cost of arbitration for all Nutex hospital and professional services for the years ended December 31, 2025 and 2024 was $138.3 million and $57.7 million, respectively, including the fees paid to HaloMD.
Regulatory Licensing and Certification. Many states, including Arizona, Arkansas, Florida, Indiana, Kansas, Louisiana, New Mexico, Ohio, Oklahoma, Texas, and Wisconsin, require regulatory approval, including licensure and certification, before establishing certain types of clinics offering certain professional and ancillary services, including the services Nutex offers. The operations of the Nutex owned and managed hospitals are subject to extensive federal, state, and local regulation relating to, among other things, the adequacy of medical care, equipment, personnel, operating policies and procedures, and proof of financial ability to operate. Our ability to operate profitably depends in part on the ability of Nutex owned and managed facilities and its providers to obtain and maintain all necessary licenses and other approvals, and maintain updates to their enrollment in the Medicare and Medicaid programs, including the addition of new hospital locations, providers and other enrollment information. In addition, certain ancillary services such as the provision of diagnostic laboratory testing require additional state and federal licensure and regulatory oversight, including oversight by CMS, under Clinical Laboratory Improvement Amendments of 1988, or CLIA, which requires all clinical laboratories to meet certain quality assurance, quality control and personnel standards, and comparable state laboratory licensing authorities. Standards for testing under CLIA are based on the complexity of the tests performed by the laboratory, with tests classified as “high complexity,” “moderate complexity,” or “waived.” Nutex owned and managed facilities hold CLIA Certificates of Waiver and perform certain CLIA-waived tests, which subject such clinics to certain CLIA requirements. Sanctions for failure to comply with applicable state and federal licensing, certification and other regulatory requirements include suspension, revocation or limitation of the applicable authorization, significant fines and penalties and/or an inability to receive reimbursement from government healthcare programs and other third-party payors.
Nutex providers must meet minimum requirements to commence participation or continue participation with Nutex through a credentialing process, including, without limitation, having a valid current medical license and DEA registration, if required for the provider’s scope of practice, the absence of any debarment, suspension, exclusion or other restriction from receiving payments from any government or other third-party payor program, and clearing National Practitioner Data Bank of any reports and/or disciplinary actions. Nutex’s credentialing program is designed to meet CMS and the National Committee for Quality Assurance, or NCQA, credentialing requirements as well as applicable federal and state laws. Providers are generally recredentialed every three years or more often if necessary, which is consistent with industry guidelines. In addition, network providers are required under their participating provider agreements with Nutex to have established an ongoing quality assurance program. Moreover, Nutex’s contracts may allow Nutex to withhold compensation from time to time based upon the providers meeting certain quality metrics, including HEDIS quality measures and care coordination metrics.
State Corporate Practice of Medicine and Fee-Splitting Laws. Our arrangements with our affiliated professional entities and other physician partners are subject to various state laws, commonly referred to as corporate practice of medicine and fee-splitting laws, which are intended to prevent unlicensed persons from interfering with or influencing the physician’s professional judgment and prohibiting the sharing of professional service fees with non-professional or business interests. These laws vary from state to state, including those where the Company does business, and are subject to broad interpretation and enforcement by state regulators.
A determination of non-compliance against us and/or our affiliated professional entities or other physician partners based on the reinterpretation of existing laws or adoption of new laws could lead to adverse judicial or administrative action, civil or criminal penalties, receipt of cease-and-desist orders from state regulators, loss of provider licenses, and/or restructuring of these arrangements.
Healthcare Fraud and Abuse Laws. We are subject to a number of federal and state healthcare regulatory laws that restrict certain business practices in the healthcare industry. These laws include, but are not limited to, federal and state anti-kickback, false claims, self-referral and other healthcare fraud and abuse laws.
The federal Anti-Kickback Statute ("AKS"), prohibits, among other things, knowingly and willfully offering, paying, soliciting, or receiving remuneration, directly or indirectly, in cash or kind, to induce or reward either the referral of an individual for, or the purchase, order or recommendation of, any good or service, for which payment may be made under federal and state healthcare programs such as Medicare and Medicaid. A person or entity does not need to have actual knowledge of the statute or specific intent to violate it in order to have committed a violation.
10
Several courts have interpreted AKS’s intent requirement to mean that if any one purpose of an arrangement involving remuneration is to induce referrals of federal healthcare covered business, the AKS has been violated.
The AKS includes statutory exceptions and regulatory safe harbors that protect certain arrangements. By way of example, the AKS safe harbor for value-based arrangements and the safe harbor for arrangements between managed care organizations and downstream contractors both require, among other things, that the arrangement does not induce a person or entity to reduce or limit medically necessary items or services furnished to any patient. Failure to meet the requirements of an applicable AKS safe harbor, however, does not render an arrangement illegal. Rather, the government may evaluate such arrangements on a case-by-case basis, taking into account all facts and circumstances, including the parties’ intent and the arrangement’s potential for abuse, and may be subject to greater scrutiny by enforcement agencies.
The Stark Law prohibits a physician who has a financial relationship, or who has an immediate family member who has a financial relationship, with entities providing designated health services, or DHS, from referring Medicare and Medicaid patients to such entities for the furnishing of DHS, unless an exception applies. The Stark Law also prohibits the entity from billing for any such prohibited referral. Unlike the AKS, the Stark Law is violated if the financial arrangement does not meet an applicable exception, regardless of any intent by the parties to induce or reward referrals or the reasons for the financial relationship and the referral.
The Federal False Claims Act ("FCA") prohibits a person from knowingly presenting, or caused to be presented, a false or fraudulent request for payment from the federal government, or from making a false statement or using a false record to have a claim approved. A claim includes “any request or demand” for money or property presented to the United States government. Moreover, the government may assert that a claim including items and services resulting from a violation of the AKS or the Stark Law constitutes a false or fraudulent claim for purposes of the civil FCA. Penalties for a violation of the FCA include fines for each false claim, plus up to three times the amount of damages caused by each false claim. Private individuals also have the ability to bring actions under these false claims’ laws in the name of the government alleging false and fraudulent claims presented to or paid by the government (or other violations of the statutes) and to share in any amounts paid by the entity to the government in fines or settlement. Such suits, known as qui tam actions, are pervasive in the healthcare industry.
Further, the Civil Monetary Penalties Statute authorizes the imposition of civil monetary penalties, assessments, and exclusion against an individual or entity based on a variety of prohibited conduct, including, but not limited to offering remuneration to a federal health care program beneficiary that the individual or entity knows or should know is likely to influence the beneficiary to order or receive health care items or services from a particular provider. Moreover, in certain cases, providers who routinely waive copayments and deductibles for Medicare and Medicaid beneficiaries can also be held liable under the AKS and civil FCA. One of the statutory exceptions to the prohibition is non-routine, unadvertised waivers of copayments or deductible amounts based on individualized determinations of financial need or exhaustion of reasonable collection efforts. The HHS’ Office of Inspector General emphasizes, however, that this exception should only be used occasionally to address special financial needs of a particular patient. Although this prohibition applies only to federal healthcare program beneficiaries, the routine waivers of copayments and deductibles offered to patients covered by commercial payors may implicate applicable state laws related to, among other things, unlawful schemes to defraud, excessive fees for services, tortious interference with patient contracts and statutory or common law fraud.
HIPAA also established federal criminal statutes that prohibit, among other things, knowingly and willfully executing, or attempting to execute, a scheme to defraud any healthcare benefit program, including private third-party payors, and knowingly and willfully falsifying, concealing, or covering up a material fact or making any materially false, fictitious or fraudulent statement in connection with the delivery of or payment for healthcare benefits, items or services. Similar to the AKS, a person or entity does not need to have actual knowledge of the statute or specific intent to violate it in order to have committed a violation.
Several states in which we operate have also adopted similar fraud and abuse laws as described above. The scope of these laws and the interpretations of them vary from state to state and are enforced by state courts and regulatory authorities, each with broad discretion. Some state fraud and abuse laws apply to items or services reimbursed by any payor, including patients and commercial insurers, not just those reimbursed by a federally funded healthcare program.
Violation of any of these laws or any other governmental regulations that apply may result in significant penalties, including, without limitation, administrative civil and criminal penalties, damages, disgorgement, fines, additional reporting requirements and compliance oversight obligations, in the event that a corporate integrity agreement or other
11
agreement is required to resolve allegations of noncompliance with these laws, the curtailment or restructuring of operations, exclusion from participation in governmental healthcare programs and/ or individual imprisonment.
Healthcare Reform. In the United States, there have been, and we expect there will continue to be, a number of legislative and regulatory changes to the healthcare system, many of which are intended to contain or reduce healthcare costs. By way of example, in the United States, the Patient Protection and Affordable Care Act, as amended by the Health Care and Education Reconciliation Act (collectively, the “ACA”) substantially changed the way healthcare is financed by both governmental and private insurers. The ACA required, among other things, CMS to establish a Medicare shared savings program that promotes accountability and coordination of care through the creation of Accountable Care Organizations (ACOs). The Medicare shared savings program allows for providers, physicians and other designated health care professionals and suppliers to form ACOs and voluntarily work together to invest in infrastructure and redesign delivery processes to give coordinated high-quality care to their Medicare patients, avoid unnecessary duplication of services and prevent medical errors. ACOs that achieve quality performance standards established by CMS are eligible to share in a portion of the Medicare program’s cost savings. ACO program methodologies and participation requirements are updated by CMS for each performance year and participants are expected to comply with such program requirements and required to report on performance after the close of the year. ACOs that fail to comply with such program requirements can face penalties or even termination of their participation in the Medicare shared savings program.
Additionally, the Center for Medicare and Medicaid Innovation continues to test an array of value-based alternative payment models, including the Global and Professional Direct Contracting Model to allow Direct Contracting Entities to negotiate directly with the government to manage traditional Medicare beneficiaries and share in the savings and risks generated from managing such beneficiaries. Although we currently do not participate in these pilot payment models, we may choose to do so in the future. Additional changes that may affect our business include the expansion of new programs such as Medicare payment for performance initiatives for physicians under the Medicare Access and CHIP Reauthorization Act of 2015, which first affected physician payment in 2019. At this time, it is unclear how the introduction of the Medicare quality payment program will impact overall physician reimbursement. In addition, there likely will continue to be regulatory proposals directed at containing or lowering the cost of healthcare, as government healthcare programs and other third-party payors transition from FFS to value-based reimbursement models, which can include risk-sharing, bundled payment and other innovative approaches. It is possible that the federal or state governments will implement additional reductions, increases, or changes in reimbursement in the future under government programs that may adversely affect us or increase the cost of providing our services. The implementation of cost containment measures or other healthcare reforms may prevent us from being able to generate revenue or attain growth, any of which could have a material impact on our business.
Further, healthcare providers and industry participants are also subject to a growing number of requirements intended to promote the interoperability and exchange of patient health information. An example is the 21st Century Cures Act, also known as the Cures Act, which was passed and signed into law in December 2016, which includes provisions related to data interoperability, information blocking and patient access. On April 5, 2021, healthcare providers and certain other entities became subject to information blocking restrictions pursuant to the Cures Act that prohibit practices that are likely to interfere with the access, exchange or use of electronic health information, except as required by law or specified by the HHS as a reasonable and necessary activity. Violations may result in penalties or other disincentives. It is unclear at this time what the costs of compliance with the new rules will be, and what additional risks there may be to our business. Additionally, the potential impact of new policies that may be implemented as a result of the new administration is currently uncertain.
Data Privacy and Security Laws. We are subject to a number of federal and state laws and regulations that govern the collection, use, disclosure, and protection of health-related and other personal information, including health information privacy and security laws, data breach notification laws, and consumer protection laws and regulations (e.g., Section 5 of the FTC Act). For example, HIPAA imposes obligations on “covered entities,” including certain healthcare providers, such as the affiliated professional entities, health plans, and healthcare clearinghouses, and their respective “business associates” that create, receive, maintain or transmit individually identifiable health information for or on behalf of a covered entity, as well as their covered subcontractors with respect to safeguarding the privacy, security and transmission of individually identifiable health information. Entities that are found to be in violation of HIPAA, whether as the result of a breach of unsecured PHI, a complaint about privacy practices, or an audit by HHS, may be subject to significant civil, criminal, and administrative fines and penalties and/or additional reporting and oversight obligations if required to enter into a resolution agreement and corrective action plan with HHS to settle allegations of HIPAA non-compliance.
12
In addition, certain state laws, such as the California Confidentiality of Medical Information Act (CMIA), the California Consumer Privacy Act of 2018 (CCPA), and the California Privacy Rights Act (CPRA), govern the privacy and security of personal information, including health-related information in certain circumstances, some of which are more stringent than HIPAA and many of which differ from each other in significant ways and may not have the same effect, thus complicating compliance efforts.
Failure to comply with these laws, where applicable, can result in the imposition of significant civil and/or criminal penalties and private litigation. Privacy and security laws, regulations, and other obligations are constantly evolving, may conflict with each other to complicate compliance efforts, and can result in investigations, proceedings, or actions that lead to significant civil and/or criminal penalties and restrictions on data processing.
Federal and State Insurance and Managed Care Laws. Regulation of downstream risk-sharing arrangements, including, but not limited to, at-risk and other value-based arrangements, varies significantly from state to state. Some states require downstream entities and risk-bearing entities to obtain an insurance license, a certificate of authority, or an equivalent authorization, in order to participate in downstream risk-sharing arrangements with payors. In some states, statutes, regulations and/or formal guidance explicitly address whether and in what manner the state regulates the transfer of risk by a payor to a downstream entity. However, the majority of states do not explicitly address the issue, and in such states, regulators may nonetheless interpret statutes and regulations to regulate such activity. If downstream risk-sharing arrangements are not regulated directly in a particular state, the state regulatory agency may nonetheless require oversight by the licensed payor as the party to such a downstream risk-sharing arrangement. Such oversight is accomplished via contract and may include the imposition of reserve requirements, as well as reporting obligations. Further, state regulatory stances regarding downstream risk-sharing arrangements can change rapidly and codified provisions may not keep pace with evolving risk-sharing mechanisms and other new value-based reimbursement models. Certain of the states where we currently operate or may choose to operate in the future regulate the operations and financial condition of risk bearing organizations like us and our affiliated providers.
Employees
We had 944 full-time employees as of December 31, 2025, including our named executive officers. None of our employees are covered by collective bargaining agreements, and we have not experienced any strikes or work stoppages related to labor relation issues. We believe we have good relations with our employees.
Human Capital Management
Attracting, developing, and retaining talented people who embrace our culture, execute our strategy, and enable us to compete effectively in our industry is critical to our success. Our mission is to make concierge-level health care more accessible to all communities we choose to enter, with a practice centered on patients’ experience and satisfaction. Our vision is to be leaders in individualized patient care and innovators in the future of health care. Patient care is our number one priority and every single decision that we make as a company revolves around creating the best possible patient care. We understand that our success is directly correlated to ensuring that we have the right team members and that each of our team members is passionate about the important role that they play in executing our mission and improving the health outcomes for all of our patients. As such, we aim to attract and retain qualified and passionate partner doctors, hospitalists and support staff who represent a diverse array of perspectives and skills who work together as a cohesive team that embodies our values and support our mission.
Our ability to recruit and retain partner doctors, hospitalists and support staff depends on a number of factors, including providing ownership opportunities, competitive compensation and benefits, development and career advancement opportunities, and a collegial work environment. We invest in those areas in an effort to ensure that we continue to be the employer of choice for our team members.
Where You Can Find More Information
We file annual, quarterly and current reports, proxy statements and other information required by the Securities Exchange Act of 1934, as amended (the “Exchange Act”), with the Securities and Exchange Commission (the “SEC”). Our SEC filings are also available to the public from the SEC’s internet site at http://www.sec.gov.
On our Internet website, http://www.nutexhealth.com, on the “Investors” webpage under the caption “SEC Filings,” we post the following recent filings as soon as reasonably practicable after they are electronically filed with or furnished to the
13
SEC: our annual reports on Form 10-K, our quarterly reports on Form 10-Q, our current reports on Form 8-K, and any amendments to those reports filed or furnished pursuant to Section 13(a) or 15(d) of the Exchange Act.
Item 1A. Risk Factors
Our business, financial condition, and operating results are affected by a number of factors, whether currently known or unknown, including risks specific to us or the healthcare industry, as well as risks that affect businesses in general. The risks disclosed in this Annual Report could materially adversely affect our business, financial condition, cash flows, or results of operations and thus our stock price. These risk factors may be important to understanding other statements in this Annual Report and should be read in conjunction with the consolidated financial statements and related notes in Part II, Item 7, “Management’s Discussion and Analysis of Financial Condition and Results of Operations” and Part II, Item 8, “Financial Statements and Supplementary Data” of this Annual Report on Form 10-K. These disclosures reflect the Company’s beliefs and opinions as to factors that could materially and adversely affect the Company and its securities in the future. References to past events are provided by way of example only and are not intended to be a complete listing or a representation as to whether or not such factors have occurred in the past or their likelihood of occurring in the future. Because of such risk factors, as well as other factors affecting the Company’s financial condition and operating results, past financial performance may not reflect future performance, and investors should not use historical trends to anticipate results or trends in future periods.
Our operations and financial results are subject to various risks and uncertainties, including but not limited to those described below, which could harm our business, reputation, financial condition, and operating results.
Summary of Risk Factors
This summary provides an overview of the risks we face and should not be considered a substitute for the comprehensive discussion of risk factors discussed immediately following this summary.
Risks Related to Nutex Health Inc.
•Regulatory and litigation uncertainty under the No Surprises Act may reduce our cash collections and increase dispute costs.
•Our third-party provider in the federal and state arbitration process, HaloMD, has been, and may in the future be, subject to lawsuits filed by health insurance providers, which may have an adverse impact on our reputation, financial condition and the trading price of our common stock.
•Sales of a substantial amount of our Common Stock by our stockholders, or the perception that such sales could occur, could cause the price of our Common Stock to fall.
•Our obligation to issue additional shares of our common stock to former doctor owners of under construction hospitals may cause significant dilution of the voting power of our current stockholders.
•Short sellers of our stock may be manipulative and may drive down the market price of our common stock.
•We may be subject to risks of litigation and disputes.
•If we are unable to maintain an effective system of disclosure controls and procedures and internal controls over financial reporting, we may not be able to accurately or timely report our financial condition or results of operations, which may adversely affect our results of operations, our stock price and investor confidence in our company.
•We may be required to take write-downs or write-offs, restructuring and impairment or other charges that could have a significant negative effect on our financial condition, results of operations and stock price, which could cause you to lose some or all of your investment.
•Our current business plans require a significant amount of capital. If we are unable to generate sufficient cash from operations, borrow money on commercially reasonable terms, or sell equity at reasonable values, we may not be able to execute our business plans and our prospects, financial condition and results of operations could be materially adversely affected.
•We may decide to close underperforming hospitals which may result in a temporary decrease in overall revenues.
•We may experience difficulties in managing our growth and expanding our operations.
Risks Related to Our Business and Industry
•Reimbursement methodology and timing for our medical services is subject to change, and the reimbursement amount that we receive for emergency services could be subject to a significant and sustained decline.
14
•The estimates and assumptions we are required to make in connection with the preparation of our financial statements may prove to be inaccurate.
•Public health emergencies could negatively affect our operations, business and financial condition, and our ability to generate revenue could be negatively impacted if the U.S. economy remains unstable for a significant amount of time.
•We rely on our management team and key employees and our business, financial condition, cash flows and results of operations could be harmed if we are unable to retain qualified personnel.
•Our growth depends in part on our ability to identify and develop successful hospitals in new geographies, physician partners and patients. If we are not able to successfully execute upon our growth strategies, there may be a material adverse effect on our business, financial condition, cash flows and results of operations.
•In his capacity as the co-owner of the real estate entities that lease the land and buildings to our hospital facilities, Dr. Vo, our Chairman, CEO and major stockholder, may have conflicts of interest with the Company and its public stockholders.
•If the estimates and assumptions we use to project the size, revenue or medical expense amounts of hospitals in our target geographies are inaccurate or the cost of providing services exceeds the amounts received by us, our future growth prospects may be impacted, and we may generate losses or fail to attain financial performance targets.
•We primarily depend on reimbursement by third-party payors, as well as payments by individuals, which could lead to delays and uncertainties in the timing and process of reimbursement, including any changes or reductions in Medicare reimbursement rates or rules.
•Our business and growth strategy depend on our ability to maintain and expand facilities staffed with qualified physicians. If we are unable to do so, future growth would be limited and our business, operating results and financial condition would be harmed.
•If any of our physician partners lose their regulatory licenses, permits and/or accreditation status, or become ineligible to receive reimbursement under Medicare or Medicaid or from other third-party payors, there may be a material adverse effect on our business, financial condition, cash flows, or results of operations.
•We are dependent on our physicians and other healthcare professionals to effectively manage the quality and cost of care.
•We operate in a competitive industry, and if we are not able to compete effectively, our business, financial condition and results of operations will be harmed.
•Developments affecting spending by the healthcare industry could adversely affect our business.
•We and our physician partners and other healthcare professionals may become subject to medical liability claims, which could cause us to incur significant expenses and may require us to pay significant damages if the claims are not covered by insurance.
•If we or our partner physicians or other healthcare providers fail to comply with applicable data interoperability and information blocking rules, our consolidated results of operations could be adversely affected.
•Our business and operations could suffer in the event of material information technology system failures, security breaches, or other deficiencies in cybersecurity.
•Actual or perceived failures to comply with applicable data protection, privacy and security laws, regulations, standards and other requirements, including contractual obligations, could adversely affect our business, financial condition and results of operations.
•Changes in U.S. tax laws, and the adoption of tax reform policies could adversely affect our operating results and financial condition.
•Our quarterly results may fluctuate significantly, which could adversely impact the value of our Common Stock.
•Obligations under the term loans of our hospitals, and our related loan and leases guarantees could restrict our operations, particularly our ability to respond to changes in our business or to take specified actions. An event of default under the term loans could harm our business, and creditors having security interests over the hospital assets as well as the leased real estate would be able to foreclose on such assets.
•The arrangements we have with our VIEs are not as secure as direct ownership of such entities.
•Any failure by our affiliated entities or their owners to perform their obligations under their agreements with us would have a material adverse effect on our business, results of operations and financial condition.
•If there is a change in accounting principles or the interpretation thereof affecting consolidation of VIEs, it could impact our consolidation of total revenues derived from our affiliated physician groups.
Risk Related to our Population Health Management Division
•New physicians and other providers must be properly enrolled in governmental healthcare programs before we can receive reimbursement for their services, and there may be delays in the enrollment process.
15
•We may have difficulty collecting payments from third-party payors in a timely manner.
•Decreases in payor rates could adversely affect us.
•Federal and state laws may limit our ability to collect monies owed by patients.
•We have established reserves for our potential medical claim losses, which are subject to inherent uncertainties, and a deficiency in the established reserves may lead to a reduction in our assets or net incomes.
•We do not have a Knox-Keene license.
•If our affiliated physician group is not able to satisfy California financial solvency regulations, they could become subject to sanctions and their ability to do business in California could be limited or terminated.
•Primary care physicians may seek to affiliate with our and our competitors’ IPAs at the same time.
•If we inadvertently employ or contract with an excluded person, we may face government sanctions.
•New California privacy regulations require Automated Decision-Making Technology (“ADMT”) transparency and future cybersecurity audits.
•Heightened scrutiny of Medicare Advantage risk-adjustment practices may increase audit and repayment risk.
Risks Related to Our Legal and Regulatory Environment
•We conduct business in a heavily regulated industry and if we fail to adhere to all of the complex government laws and regulations that apply to our business, we could incur fines or penalties or be required to make changes to our operations or experience adverse publicity, any or all of which could have a material adverse effect on our business, results of operations, financial condition, cash flows, and reputation.
•If any of our hospitals lose their regulatory licenses, permits and/or registrations, as applicable, or become ineligible to receive reimbursement from third-party payors, there may be a material adverse effect on our business, financial condition, cash flows, or results of operations.
•If our arrangements with our partner physicians and other physician partners are found to constitute the improper rendering of medical services or fee splitting under applicable state laws, our business, financial condition and our ability to operate in those states could be adversely impacted.
•We face inspections, reviews, audits and investigations under federal and state government programs and contracts. These audits could have adverse findings that may negatively affect our business, including our results of operations, liquidity, financial condition and reputation.
•Recent healthcare regulations, and other changes in the healthcare industry and in healthcare spending may adversely affect our business, financial condition and results of operations.
•Changes to Stark Law DHS codes and exception thresholds may increase compliance risk.
•HIPAA rule changes may require operational and documentation updates and raise enforcement exposure.
•Escalating cyber threats and regulatory expectations may increase costs and disruption risk.
Risks Related to Our Common Stock
•Anti-takeover provisions under Delaware law could make an acquisition of the Company, which may be beneficial to the stockholders of the Company, more difficult and may prevent attempts by the stockholders to replace or remove management.
•Because we have no current plans to pay cash dividends on our Common Stock for the foreseeable future, you may not receive any return on investment unless you sell your Common Stock for a price in excess of the purchase price.
•The market price and trading volume of our Common Stock may be volatile and could decline significantly.
If securities or industry analysts do not publish research or publish inaccurate or unfavorable research about our business, the price and trading volume of our securities could decline.
Risks Related to Nutex Health Inc.
Regulatory and litigation uncertainty under the No Surprises Act may reduce our cash collections and increase dispute costs.
Any significant changes to the federal arbitration process may result in a substantial decrease in the claim amounts we will be able to recover in the future. In light of pending litigation before the Fifth Circuit referred to as TMA III, federal agencies have, in guidance issued on July 30, 2025, extended enforcement relief for services furnished before February 1, 2026 (additional enforcement relief may be provided until August 1, 2026), allowing insurers to continue to calculate in good faith the Qualified Payment Amount (QPA) relying on the previous methodologies set forth in the rules and guidance
16
issued in 2021 and 2023, which can result in low QPAs and thus can affect reimbursements we receive for out‑of‑network services and the outcome of IDR disputes. In addition, updates to the Federal IDR portal (e.g., service‑code modifier fields, duplicate‑dispute validation, and resubmission rules) have increased submission complexity and may delay dispute resolutions or require re‑filings, raising administrative costs.
Further, the Fifth Circuit has held that the NSA explicitly bars judicial review of arbitration awards. The NSA does allow HHS to assess penalties against insurers for failure to comply with the NSA, including timely payment of CIDRE awards. As a result, we may be limited to HHS administrative recourse if a provider fails to pay arbitration awards, which could adversely impact our ability to collect payments due under successful award determinations.
The Company is unable to predict the outcome of pending litigation, future legislative or regulatory changes, evolving arbitration practices, payor responses to ongoing enforcement of the NSA, and insurers’ payment discipline, all of which may have an adverse impact on the Company’s ability to recover on its claims and its financial condition and results of operation.
Our third party provider in the federal and state arbitration process, HaloMD, has been, and may in the future be, subject to lawsuits filed by health insurance providers, which may have an adverse impact on our revenues, reputation, financial condition and the trading price of our common stock.
Since May 2024, HaloMD has handled, on an exclusive basis, all out-of-network claims made by Nutex that are eligible for arbitration under federal and state “no surprise” laws. During the year ended December 31, 2025, HaloMD submitted approximately 50-60% of the Company’s medical claims through the IDR process. Pending or future litigation against HaloMD could materially adversely impact the revenues we expect to receive from the medical claims submitted on our behalf by HaloMD.
Nutex has no contractual right to access or audit HaloMD’s proprietary benchmarking data or documents prepared and submitted by HaloMD to the IDREs on behalf of the Company, such as petitions, position statements, methodology formulas, payment demand letters and arbitration briefs.
On July 22, 2025, a short seller published a report making various negative assertions about the Company, which were largely extrapolated from allegations made in lawsuits against HaloMD and certain providers filed in the spring of 2025 by affiliates of Anthem/Blue Cross Blue Shield. The insurers allege that HaloMD submitted many claims that were ineligible for federal arbitration and otherwise abused the IDR process. HaloMD’s motions to dismiss are pending. While we are not party to these or similar lawsuits, the short seller attack had an adverse impact on the trading price of our common stock. We cannot predict whether additional lawsuits may be brought, the outcome of the existing lawsuits against HaloMD or the resulting impact on our revenues, reputation, financial condition or the trading price of our common stock.
Sales of a substantial amount of our Common Stock by our stockholders, or the perception that such sales could occur, could cause the price of our Common Stock to fall.
As of March 2, 2026, there were 6,968,350 shares of Common Stock outstanding, including 2,251,295 shares of Common Stock held by our affiliates, including our Chairman and Chief Executive Officer. Our affiliates, including Dr. Vo, may sell shares into the market in accordance with Rule 144, including its manner of sale and volume limitations.
Sales of substantial amounts of our Common Stock in the public market, or the perception that such sales will occur, could adversely affect the market price of our Common Stock and make it difficult for us to raise funds through securities offerings in the future.
Our obligation to issue additional shares of our common stock to former doctor owners of under construction hospitals may cause significant dilution of the voting power of our current stockholders.
We may be required to issue additional shares of our common stock to former doctor owners of hospitals that were under construction and non-operational prior to our April 1, 2022 merger. Such former owners, including Dr. Vo, transferred their hospital interests to Nutex Health Holdco LLC in connection with the merger. The aggregate number of additional shares we may be required to issue could significantly dilute the voting power of our existing stockholders. Any such additional shares, including the shares issued to Dr. Vo, will be subject to a 100% lock up for six months, with 66 2/3% of these shares locked up for one year, and, with respect to the remaining 33 1/3%, the lock up expiring 18 months after issuance, which may be waived or amended at the discretion of the Company.
17
As approved by the stockholders on April 1, 2022, the number of additional shares issuable is equal to (a)(i) the trailing twelve months of earnings before interest, taxes, depreciation and amortization, as determined at the end of each such hospital’s initial 24-month operation period multiplied by (ii) 10; minus (iii) the aggregate amount of the former doctor owners’ capital contribution; minus (iv) such former doctor owners’ pro rata share of the aggregate debt, with the resulting value divided by (b) the greater of (i) the price of the common stock at the end of the operational period or (ii) $420.00 (representing $2.80 as adjusted for the 2024 Reverse Stock Splits, and subject to further adjustment for future stock dividends, combinations, splits, recapitalizations and the like).
With respect to seven hospitals, the initial 24-month operational periods expired on or prior to December 31, 2025. Based on the formula described above, and assuming an aggregate 1,361,861 shares issued, the earn out shares will represent approximately 19.2% of outstanding shares as of December 31, 2025.
With respect to three additional hospitals with an initial 24-month operational period expiring on or prior to December 31, 2026, we estimate, based on current expectations, to issue approximately 88,500 additional shares, or 1.2% of our outstanding shares as of December 31, 2025. See Note 12 - Stock-based Compensation for additional information. This estimated number of shares is calculated on a pro forma basis based on December 31, 2025 operating results and trading price. Since we cannot predict future operating results and trading prices, the actual number of additional shares issued may differ significantly from our estimate.
Former owners of certain under construction hospitals have disputed the number of additional shares issuable to them in accordance with the formula agreed upon at the time of the merger (as described above) and assert, among other things, that the number of shares in the calculation should not be adjusted for the 2024 Reverse Stock Splits. We disagree with these allegations but cannot predict the outcome of these disputes.
Short sellers of our stock may be manipulative and may drive down the market price of our common stock.
Short selling is the practice of selling securities that the seller does not own but rather has borrowed or intends to borrow from a third party with the intention of buying identical securities at a later date to return to the lender. A short seller hopes to profit from a decline in the value of the securities between the sale of the borrowed securities and the purchase of the replacement shares, as the short seller expects to pay less in that purchase than it received in the sale. Since it is in the short seller’s interest for the price of the stock to decline, some short sellers publish, or arrange for the publication of, opinions or characterizations regarding the relevant issuer, its business prospects and similar matters calculated to or which may create negative market momentum, which may permit them to obtain profits for themselves as a result of selling the stock short. Issuers whose securities have historically had limited trading volumes or have been susceptible to relatively high volatility levels can be particularly vulnerable to such publications, sometimes known as “short seller attacks.”
On July 22, 2025, a short seller report that contained various allegations against the Company was published, that had an adverse impact on the market price of our common stock. This report disclosed the writer had a short position with respect to our common stock. On July 23, 2025, the closing price of our common stock was $92.90, representing a decrease of $18.29 or 16.4% compared to the closing price of our common stock on July 21, 2025, prior to the publication of the report. On November 25, 2025, another short seller report that contained various allegations against the Company was published. The sole purpose of this attack appears to have been to create market confusion and to profit from the decline in trading price caused as a result. We cannot assure you that others will not publish similar misleading reports in the future. The publication of any such commentary regarding us may bring about a temporary, or long term, decline in the market price of our common stock. Similar declines in the market price of our common stock may occur in the future, in connection with such commentary by short sellers or otherwise.
In addition, following the publication of short seller reports, companies targeted by these short seller publications have sometimes faced securities class action litigation against the company as a result. Additionally, allegations made by short sellers, whether substantiated or not, could result in investigations by regulators, including the Securities and Exchange Commission. If we were subject to such investigations as a result of such allegations, we could incur substantial costs defending the Company from the lawsuit or such investigation. These could also divert the time and attention of our management from our business and result in negative publicity, which could significantly harm our profitability and reputation.
We may be subject to risks of litigation and disputes.
18
From time to time, we have been and may become involved in disputes and litigation with former doctor owners, stockholders, government and regulatory agencies or other parties. Such actions could result in the imposition of various remedies such as injunctions or monetary damages, which if awarded could materially and adversely harm our business, subject us to substantial defense costs and expenses, and divert resources and the attention of management from our business. For example, on August 22, 2025, the Company and certain current and former officers and directors were named in a putative class action lawsuit filed in the United States District Court for the Southern District of Texas. The complaint alleges violations of federal securities laws arising out of alleged misstatements or omissions by the defendants during the alleged class period and seeks, among other things, damages and attorneys’ fees and costs on behalf of the putative class. Following the putative class action lawsuit, in September 2025, the Company and certain of its directors and officers were named in two derivative action lawsuits filed in the United States District Court for the Southern District of Texas. Each of the derivative actions was brought on behalf of the Company by a putative stockholder alleging, among other things, breaches of fiduciary duties and violations of federal securities laws. The complaints seek, among other things, damages and attorneys’ fees and costs. In addition, from time to time, we are, and may become, the subject of inquiries, requests for information, investigations, or other actions by government and regulatory agencies or other third parties regarding our business. Any such matters, regardless of their merit or resolution, could be costly and divert the efforts and attention of our management, damage our reputation, or otherwise adversely affect our business.
If we are unable to maintain an effective system of disclosure controls and procedures and internal controls over financial reporting, we may not be able to accurately or timely report our financial condition or results of operations, which may adversely affect our results of operations, our stock price and investor confidence in our company.
A material weakness is a deficiency, or a combination of deficiencies, in internal control over financial reporting, such that there is a reasonable possibility that a material misstatement of the annual or interim financial statements will not be prevented or detected on a timely basis.
For the year ended December 31, 2024, we identified material weaknesses in our internal control over financial reporting. These material weaknesses that were previously disclosed as of December 31, 2024 were remediated as of December 31, 2025.
While our previous material weaknesses have been remediated, if we identify any new material weaknesses in the future, any such newly identified material weakness could limit our ability to prevent or detect a misstatement of our accounts or disclosures that could result in a material misstatement of our annual or interim financial statements. In such case, we may be unable to maintain compliance with securities law requirements regarding timely filing of periodic reports in addition to applicable stock exchange listing requirements, investors may lose confidence in our financial reporting and our stock price may decline as a result. We cannot assure you that the measures we have taken to date, or any measures we may take in the future, will be sufficient to avoid potential future material weaknesses.
We may be required to take write-downs or write-offs, restructuring and impairment or other charges that could have a significant negative effect on our financial condition, results of operations and stock price, which could cause you to lose some or all of your investment.
We may be forced to write down or write off assets, restructure operations, or incur impairment or other charges that could result in losses. Even though these charges may be non-cash items and not have an immediate impact on liquidity, any report of charges of this nature could contribute to negative market perceptions about us or our securities. In addition, charges such as write-downs or impairments may make future financing difficult to obtain on favorable terms or at all. From time to time, our intangible assets are subject to impairment testing. Under current accounting standards, our goodwill, including acquired goodwill, is tested for impairment on an annual basis and may be subject to impairment losses as circumstances change (e.g., after an acquisition).
The Company may have to record impairments in the future, which could materially adversely affect its reported financial results and negatively impact the trading value of its Common Stock.
Our current business plans require a significant amount of capital. If we are unable to generate sufficient cash from operations, borrow money on commercially reasonable terms, or sell equity at reasonable values, we may not be able to
19
execute our business plans and our prospects, financial condition and results of operations could be materially adversely affected.
We experienced operating losses in 2023 and could incur operating losses in the future as we implement our business plans. We anticipate making significant capital expenditures for the foreseeable future as we expand our business, including the development of new hospital facilities and acquisition of additional IPAs.
If we are unable to generate sufficient cash from operating activities, borrow money on commercially reasonable terms, or sell equity at reasonable values, we may be forced to curtail or discontinue our operations and our business, financial condition and results of operation could be materially adversely affected.
We may decide to close underperforming hospitals which may result in a temporary decrease in overall revenues.
In the ordinary course of business, we continuously review the individual performance of each of our hospital facilities. As previously disclosed, we have historically closed underperforming facilities. Our commitment to providing high-quality healthcare services demands that we continually assess the performance of our hospitals. In some instances, we may find it necessary to make the difficult decision to close underperforming facilities. This could be due to various factors such as declining patient admissions, increasing operational costs, or changes in healthcare regulations. The closure of any hospital within our portfolio carries inherent risks, including a potential negative impact on our overall revenues. The closure process may involve staff reallocation or severance, and asset dispositions, all of which can be complex and costly. Additionally, the closure of a hospital may temporarily disrupt patient referrals and relationships with healthcare providers in the affected region.
While we believe that such strategic decisions are essential for the long-term sustainability of our organization and the continued provision of high-quality care, there is a risk that the closure of underperforming hospitals could lead to a short-term decrease in our overall revenues. This revenue decline may occur due to the time it takes to execute the closure process as well as potential legal or regulatory challenges associated with hospital closures.
The closure of underperforming hospitals is part of our ongoing effort to optimize our operations and improve financial performance. While we intend to carefully plan and execute our closure strategies, there can be no assurance that such strategies will successfully offset the temporary revenue decrease resulting from hospital closures.
We may experience difficulties in managing our growth and expanding our operations.
We are targeting significant growth in the scope of our operations. Our ability to manage our operations and future growth will require us to continue to improve our operational, financial and management controls, compliance programs and reporting systems. We may not be able to implement improvements in an efficient or timely manner and may discover deficiencies in existing controls, programs, systems and procedures, which could have an adverse effect on our business, reputation and financial results. Additionally, rapid growth in our business may place a strain on our human and capital resources.
Risks Related to Our Business and Industry
Reimbursement methodology and timing for our medical services is subject to change, and the reimbursement amount that we receive for emergency services could be subject to a significant and sustained decline.
We do not have extensive relationships with large commercial payors and are generally out-of-network. Although some licensed hospital facilities are in-network with payors, the Company’s general payor contracting/government enrollment strategy to date has been to remain out of network. Since we have few contractual arrangements with insurance companies, we cannot predict the timing and amount of the payments we ultimately receive for our services and estimates and assumptions, which are based on historical insurance payment amounts and timing.
In addition, as a result of the NSA becoming effective on January 1, 2022, we initially experienced a significant decline in collections of patient claims for emergency services and for a significant period only had limited success at achieving collections at or higher than the established qualifying payment amount, which is the median in-network contracted rate for the same insurance market.
20
The federal regulations promulgated under the NSA, including those establishing the IDR process, have been and continue to be subject to legal challenges. Most importantly, as of March 2, 2026, the United States Court of Appeals for the Fifth Circuit has not ruled whether the QPA calculation made by providers may include so called “ghost rates,” which are rates included in contracts with no expectation that providers will actually provide such services, resulting in rates as low as $0 being included in QPA calculations. As a result, pending material litigation and regulatory uncertainty may delay claims resolution and negatively impact our ability to receive fair and appropriate payment for the services our hospitals provide. Any decrease in the collections we receive for our emergency services could have a material adverse effect on our operations and financial performance and may negatively affect the trading value of our Common Stock.
The estimates and assumptions we are required to make in connection with the preparation of our financial statements may prove to be inaccurate.
The preparation of financial statements in conformity with GAAP requires management to make estimates and assumptions that affect the reported amount of assets and liabilities and disclosure of contingent assets and liabilities at the date of the financial statements and the reported amounts of revenues and expenses during the reporting period.
We apply Financial Accounting Standards Board ("FASB") Accounting Standards Codification ("ASC") 606 – Revenue from Contracts with Customers in making estimates of its earned revenue and accounts receivable at each reporting date. This estimation process for variable consideration is highly subjective. The Company regularly conducts a comparative analysis of its actual results to its previously estimated results in order to evaluate whether changes to its estimation process are required. The estimation of variable consideration is particularly complex within the healthcare industry generally because of the broad range of services provided, the range of reimbursements by patient insurance companies and collectability of patient responsible amounts. In addition, our hospital division generally operates as an out-of-network provider and, as such, does not have negotiated reimbursement rates with insurance companies, adding to the complexity and potential uncertainty of the estimation process.
Our estimates with respect to the claims processing by insurance companies and our resulting cash collections may differ from previous estimated results, and we may be required to make periodic adjustments to our estimation process for new facts or circumstances.
Additionally, our estimates with respect to arbitration wins and our resulting cash collections from arbitration may differ due to significant administrative time built into the federal arbitration process and delays in collections.
Ultimate amounts collected may differ from anticipated collections, and, as a result, may impact our ability to generate revenue at expected levels.
Public health emergencies could negatively affect our operations, business and financial condition, and our ability to generate revenue could be negatively impacted if the U.S. economy remains unstable for a significant amount of time.
As a front-line provider of health care services, we have been and will be affected by the health and economic effects of public health emergencies such as COVID-19.
As a result of public health emergencies, we experienced, and in the future could experience, supply chain disruptions, including shortages and delays, and could experience significant price increases, in equipment and medical supplies, particularly personal protective equipment or PPE. Staffing, equipment, and medical supplies shortages may also impact our ability to serve patients at our centers.
In addition, our results and financial condition may be adversely affected by future federal or state laws, regulations, orders, or other governmental or regulatory actions addressing public health emergencies such as a COVID-19 or the U.S. health care system, which, if adopted, could result in direct or indirect restrictions to its business, financial condition, results of operations and cash flow.
We rely on our management team and key employees and our business, financial condition, cash flows and results of operations could be harmed if we are unable to retain qualified personnel.
Our success depends largely upon the continued services of key members of senior management, including our chief executive officer. We also rely on our leadership team in the areas of operations and general and administrative functions. From time to time, there may be changes in our management team resulting from the hiring or departure of executives,
21
which could disrupt our business. The replacement of one or more of our executive officers or other key employees would likely involve significant time and costs and may significantly delay or prevent the achievement of our business objectives. Our business would also be adversely affected if we fail to adequately plan for succession of our executives and senior management; or if we fail to effectively recruit, integrate, retain and develop key talent and/or align our talent with our business needs, in light of the current rapidly changing environment. While we have succession plans in place and we have employment arrangements with our key executives, these do not guarantee that the services of these or suitable successor executives will continue to be available to us.
Competition for qualified personnel in our field is intense due to the limited number of individuals who possess the skills and experience required by our industry. As a result, as we enter new geographies, it may be difficult for us to hire additional qualified personnel with the necessary skills to work in such geographies. If our hiring efforts in new or existing geographies are not successful, our business will be harmed. In addition, we have experienced employee turnover and expect to continue to experience employee turnover in the future. New hires require significant training and, in most cases, take significant time before they achieve full productivity. New employees may not become as productive as we expect, and we may be unable to hire or retain sufficient numbers of qualified individuals. If our retention efforts are not successful or our employee turnover rate increases in the future, our business, financial condition, cash flows and results of operations will be harmed.
In addition, in making employment decisions, job candidates often consider the value of the stock options or other equity instruments they are to receive in connection with their employment. Volatility in the price of our stock may, therefore, adversely affect our ability to attract or retain highly skilled personnel. Further, the requirement to expense stock options and other equity instruments may discourage us from granting the size or type of stock option or equity awards that job candidates require to join our company. Failure to attract new personnel or failure to retain and motivate our current personnel, could have a material adverse effect on our business, financial condition and results of operations.
Our growth depends in part on our ability to identify and develop successful hospitals in new geographies, physician partners and patients. If we are not able to successfully execute upon our growth strategies, there may be a material adverse effect on our business, financial condition, cash flows and results of operations.
Our business depends on our ability to identify and develop successful hospitals in new geographies and relationships with physician partners and healthcare professionals, and to successfully execute upon our growth initiatives to increase the profitability of our physician partners and healthcare professionals. In order to pursue our strategy successfully, we must effectively implement our partnership model, including identifying suitable candidates and successfully building relationships with and managing integration of new physician partners. We contract with a limited number of physician partners and rely on such physicians within each geography. Our growth initiatives in our existing geographies depend, in part, on our physician partners’ ability to increase their capacity and to effectively meet increased patient demand. We may encounter difficulties in recruiting additional physicians to work at our hospitals due to many factors, including significant competition in their respective geographies. Accordingly, the loss or dissatisfaction of any physician partners, our inability to recruit, or the failure of our hospitals to recruit additional physicians or manage and scale capacity to timely meet patient demand, could substantially harm our reputation, impact our competitiveness, and impair our ability to attract new physician partners and maintain existing physician partnerships, both in new geographies and in geographies in which we currently operate, which could have a material adverse effect on our business, financial condition, cash flows and results of operations.
Further, our growth strategy depends, in part, on securing and integrating new high-caliber physician partners and expanding into new geographies in which we have little or no operating experience. Integration and other risks can be more pronounced for larger and more complicated relationships or relationships outside of our core business space, or if we pursue multiple relationships simultaneously. New geographies, into which we seek to expand, may have laws and regulations that differ from those applicable to our current operations. As a rapidly growing company, we may be unfamiliar with the regulatory requirements in each geography that we enter, and we may be forced to incur significant expenditures to ensure compliance with regulatory requirements to which we are subject. If we are unable or unwilling to incur such costs, our growth in new geographies may be less successful than in our current geographies.
Our growth to date has significantly increased the demands on our management, operational and financial systems, infrastructure and other resources. We must continue to improve our existing systems for operational and financial management, including our reporting systems, procedures and controls. These improvements could require significant capital expenditure and place increasing demands on our management. We may not be successful in managing or expanding our operations or in maintaining adequate financial and operating systems and controls. If we do not
22
successfully manage these processes, our business, financial condition, cash flow and results of operations could be harmed.
In his capacity as the co-owner of the real estate entities that lease the land and buildings to our hospital facilities, Dr. Vo, our Chairman, CEO and major stockholder, may have conflicts of interest with the Company and its public stockholders.
The majority of our hospital facilities have contractual relationships with separately owned real estate entities (the “Real Estate Entities”) and each hospital has contractual relationships with separately owned professional entities (the “Physician LLCs”).
The Physician LLCs are owned by the doctors providing services to the corresponding hospital, provide physician and provider services to the hospitals, and employ the doctors and other providers.
The Real Estate Entities, also partially owned by the doctors providing services to the corresponding hospital, own the land and/or buildings that are leased to our hospitals. The Real Estate Entities incur debt to purchase or construct the hospital facility. Lease payments received from our hospitals are used by the Real Estate Entities to make payments on their debt. Each hospital facility’s lease payments are guaranteed by the Company.
In addition to its respective doctor owners, each Real Estate Entity is partially owned or controlled by Dr. Vo, our Chairman, CEO and major stockholder. As a result, the interests of Dr. Vo, in his capacity as part owner of the Real Estate Entities, may differ from the interests of the Company and its public shareholders, both in the re-negotiation of existing contractual relationships between the Company-owned hospital facilities and the Real Estate Entities and in the establishment of new hospital entities and their respective Real Estate Entities.
If the estimates and assumptions we use to project the size, revenue or medical expense amounts of hospitals in our target geographies are inaccurate or the cost of providing services exceeds the amounts received by us, our future growth prospects may be impacted, and we may generate losses or fail to attain financial performance targets.
We often do not have access to reliable historical data regarding the size, revenue or medical expense levels of hospitals in our target geographies or potential physician partners. As a result, our market opportunity estimates and financial forecasts developed as we enter into a new geography, are subject to significant uncertainty, and are based on assumptions and estimates that may not prove to be accurate. The estimates and forecasts in this prospectus relating to the size and expected growth of the market for our services, and the estimates of our market opportunity may prove to be inaccurate.
Changes in our anticipated ratio of medical expenses to revenue can negatively impact our financial results. Accordingly, the failure to adequately predict and control medical costs and expenses could have a material adverse effect on our business, results of operations, financial condition and cash flows. Additionally, the medical expenses of patients may be outside of our physician partners’ control in the event patients take certain actions that increase such expenses, such as unnecessary hospital visits. If we underestimate or do not correctly predict the cost of the care our partner physicians furnish to patients, we might be underpaid for the care that must be provided to patients, which could have a negative impact on our results of operations and financial condition.
We primarily depend on reimbursement by third-party payors, as well as payments by individuals, which could lead to delays and uncertainties in the timing and process of reimbursement, including any changes or reductions in Medicare reimbursement rates or rules.
The reimbursement and associated arbitration process is complex and can involve lengthy delays. Although we recognize revenue when we provide services to patients, we may from time-to-time experience delays in receiving reimbursement for the service provided, in particular as a result of the federally mandated independent dispute resolution process. Third-party payors may disallow, in whole or in part, requests for reimbursement based on determinations that the patient is not eligible for coverage, certain amounts are not reimbursable under plan coverage, were for services provided that were not medically necessary, or additional supporting documentation is necessary. Retroactive adjustments may change amounts realized from third-party payors. As described below, we are subject to audits by such payors, including governmental audits of our Medicare claims, and may be required to repay these payors if a finding is made that we were incorrectly reimbursed. Delays and uncertainties in the reimbursement process may adversely affect accounts receivable, increase the overall costs of collection and cause us to incur additional borrowing costs. Third-party payors are also increasingly focused on
23
controlling healthcare costs, and such efforts, including any revisions to reimbursement policies, may further reduce, complicate or delay our reimbursement claims.
In addition, certain of our patients are covered under health plans that require the patient to cover a portion of their own healthcare expenses through the payment of copayments or deductibles. We may not be able to collect the full amounts due with respect to these payments that are the patient’s financial responsibility, or in those instances where physicians provide services to uninsured individuals. To the extent permitted by law, amounts not covered by third-party payors are the obligations of individual patients for which we may not receive whole or partial payment. Any increase in cost shifting from third-party payors to individual patients, including as a result of high deductible plans for patients, increases our collection costs and reduces overall collections, which we may not be able to offset with sufficient revenue.
Our business and growth strategy depend on our ability to maintain and expand facilities staffed with qualified physicians. If we are unable to do so, future growth would be limited and our business, operating results and financial condition would be harmed.
Our success is dependent upon a continued ability to maintain an adequate staff of qualified providers to staff the facilities. If we are unable to recruit and retain physicians and other healthcare professionals, it would have a material adverse effect on our business and ability to grow and would adversely affect the results of operations. In any particular market, providers could demand higher payments or take other actions that could result in higher medical costs, less attractive service for our customers or difficulty meeting applicable regulatory or accreditation requirements. Our ability to develop and maintain satisfactory relationships with providers also may be negatively impacted by other factors not associated with us, such as changes in reimbursement levels and consolidation activity among hospitals, physician groups and healthcare providers, the continued private equity investment in physician practice management platforms and other market and operating pressures on healthcare providers. The failure to maintain or to secure new cost-effective provider contracts may result in a loss of or inability to staff existing or new facilities, higher costs, less attractive service for patients and/or difficulty in meeting applicable regulatory requirements, any of which could have a material adverse effect on our business, financial condition and results of operations.
If any of our physician partners lose their regulatory licenses, permits and/or accreditation status, or become ineligible to receive reimbursement under Medicare or Medicaid or from other third-party payors, there may be a material adverse effect on our business, financial condition, cash flows, or results of operations.
The operations of our hospitals through our physician partners are subject to extensive federal, state and local regulation relating to, among other things, the adequacy of medical care, equipment, personnel, operating policies and procedures, fire prevention, rate-setting and compliance with building codes and environmental protection. Our hospitals and their affiliated professional entities are also subject to extensive laws and regulation relating to facility and professional licensure, conduct of operations, including financial relationships among healthcare providers, Medicare and Medicaid fraud and abuse and physician self-referrals, and maintaining updates to the hospital’s affiliated professional entities’ enrollment in the Medicare and Medicaid programs, including the addition of new clinic locations, providers and other enrollment information. Our hospitals and their affiliated professional entities are subject to periodic inspection by licensing authorities and accreditation organizations to ensure their continued compliance with these various standards. There can be no assurance that these regulatory authorities will determine that all applicable requirements are fully met at any given time. Should any of our hospitals or their affiliated professional entities be found to be noncompliant with these requirements, we could be assessed fines and penalties, could be required to refund reimbursement amounts or could lose our licensure or Medicare and/or Medicaid certification or accreditation so that we or our hospitals are unable to receive reimbursement from third-party payors, which could materially adversely affect our business, financial condition, cash flows or results of operations.
We are dependent on our physicians and other healthcare professionals to effectively manage the quality and cost of care.
Our success depends upon our continued ability to collaborate with and expand the number of highly qualified physicians and other healthcare professionals, which are key drivers of our profitability.
24
We operate in a competitive industry, and if we are not able to compete effectively, our business, financial condition and results of operations will be harmed.
Our industry is competitive, and we expect it to attract increased competition. We currently face competition in various aspects of our business, including from a range of companies that provide similar services, including hospitals, managed service organizations and provider networks and data analysis consultants.
Our primary competitors include numerous local provider networks, hospitals and health systems. We may face a more competitive environment and increased challenges to grow at the rates we have projected. We expect that competition will continue to increase as a result of consolidation in the healthcare industry and increased demand for its services.
Some of our competitors may have greater name recognition, particularly in local geographies, longer operating histories, superior products or services and significantly greater resources than we do. Further, our current or potential competitors may be acquired by or partner with third parties with greater resources than we have. As a result, our competitors may be able to respond more quickly and effectively than we can to new or changing opportunities, technologies, standards or customer requirements and may have the ability to initiate or withstand premium competition. In addition, current and potential competitors have established, and may in the future establish, cooperative relationships with providers of complementary services, technologies or services to increase the attractiveness of their services.
Accordingly, new competitors or alliances may emerge which could put us at a competitive disadvantage. If we are unable to successfully compete, our business, financial condition, cash flows and results of operations could be materially adversely affected.
Developments affecting spending by the healthcare industry could adversely affect our business.
The U.S. healthcare industry has changed significantly in recent years, and we expect that significant changes will continue to occur. General reductions in expenditures by healthcare industry participants could result from, among other things:
•regulatory uncertainty regarding the implementation of and reimbursement processes under the NSA;
•government regulations or private initiatives that affect the manner in which healthcare providers interact with patients, payors or other healthcare industry participants, including changes in pricing or means of delivery of healthcare products and services;
•consolidation of healthcare industry participants;
•reductions in government funding for healthcare; and
•adverse changes in business or economic conditions affecting healthcare payors or providers or other healthcare industry participants.
Any of these changes in healthcare spending could adversely affect our revenue. Even if general expenditures by industry participants remain the same or increase, developments in the healthcare industry may result in reduced spending in some or all of the specific market segments that we serve now or in the future. However, the timing and impact of developments in the healthcare industry are difficult to predict. Demand for our services may not continue at current levels and we may not have adequate technical, financial, and marketing resources to react to changes in the healthcare industry.
We and our physician partners and other healthcare professionals may become subject to medical liability claims, which could cause us to incur significant expenses and may require us to pay significant damages if the claims are not covered by insurance.
Our overall business entails the risk of medical liability claims. Although we, and our partner professionals carry insurance covering medical malpractice claims in amounts that we believe are appropriate in light of the risks attendant to the services rendered, successful medical liability claims could result in substantial damage awards that exceed the limits of our and those partner professionals’ insurance coverage. We carry or will carry professional liability insurance for us and each of our healthcare professionals. Professional liability insurance is expensive, and insurance premiums may increase significantly in the future, particularly as we expand our services. As a result, adequate professional liability insurance may not be available to us and our partner professionals in the future at acceptable costs or at all, which may negatively impact our and our partner professionals’ ability to provide services to our hospitals, and thereby adversely affect our overall business and operations.
25
Any claims made against us or our partner professionals that are not fully covered by insurance could be costly to defend against, result in substantial damage awards, and divert the attention of our management and our partner professional entities from our operations, which could have a material adverse effect on our business, financial condition and results of operations. In addition, any claims may adversely affect our business or reputation.
If we or our partner physicians or other healthcare providers fail to comply with applicable data interoperability and information blocking rules, our consolidated results of operations could be adversely affected.
The 21st Century Cures Act, or the Cures Act, which was passed and signed into law in December 2016, includes provisions related to data interoperability, information blocking and patient access. In March 2020, the U.S. Department of Health and Human Services, or HHS, Office of the National Coordinator for Health Information Technology, or ONC, and CMS finalized and issued complementary rules that are intended to clarify provisions of the Cures Act regarding interoperability and information blocking, and include, among other things, requirements surrounding information blocking, changes to ONC’s health IT certification program and requirements that CMS regulated payors make relevant claims/care data and provider directory information available through standardized patient access and provider directory application programming interfaces that connect to provider electronic health record systems. The companion rules will transform the way in which healthcare providers, health IT developers, health information exchanges/health information networks, or HIEs/HINs, and health plans share patient information, and create significant new requirements for healthcare industry participants. Heightened information blocking enforcement may result in penalties and reimbursement disincentives. HHS has directed OIG and ONC to actively enforce information-blocking regulations. Civil monetary penalties up to $1 million per violation apply to certain entities; provider disincentives (including negative MIPS adjustments and MSSP impacts) became effective during 2024–2025. Investigations or adverse findings could lead to financial penalties, reputational harm, and operational remediation costs.
Our business and operations could suffer in the event of material information technology system failures, security breaches, or other deficiencies in cybersecurity.
Our information technology systems facilitate our ability to conduct our business. While we have disaster recovery systems and business continuity plans in place, any disruptions in our disaster recovery systems or the failure of these systems to operate as expected could, depending on the magnitude of the problem, adversely affect our operating results by limiting our capacity to effectively monitor and control our operations. Despite our implementation of a variety of reasonable security measures, our information technology systems could be subject to physical or electronic break-ins, and similar disruptions from unauthorized tampering or any weather-related disruptions where our headquarters is located. In addition, in the event that a significant number of our management personnel were unavailable in the event of a disaster, our ability to effectively conduct business could be adversely affected.
In the ordinary course of our business, we, our partner physicians or other physician partners collect and store sensitive data, including personally identifiable information, protected health information, intellectual property and proprietary business information owned or controlled by us or our employees, members and other parties. We manage and maintain our applications and data utilizing a combination of on-site systems and cloud-based data centers. We utilize external security and infrastructure vendors to provide and manage parts of our information technology systems, including our data centers. These applications and data encompass a wide variety of business-critical information, including research and development information, customer information, commercial information and business and financial information. We face a number of risks with respect to the protection of this information, including loss of access, inappropriate use or disclosure, unauthorized access, inappropriate modification and the risk of being unable to adequately monitor and audit and modify our controls over our critical information. This risk extends to the third-party vendors and subcontractors we use to manage this sensitive data or otherwise process it on our behalf. A breach or failure of our or our third-party vendors’ or subcontractors’ network, hosted service providers or vendor systems could result from a variety of circumstances and events, including third-party action, employee negligence or error, malfeasance, computer viruses, cyber-attacks by computer hackers such as denial-of-service and phishing attacks, failures during the process of upgrading or replacing software and databases, power outages, hardware failures, telecommunication failures, user errors, or catastrophic events. If these third-party vendors or subcontractors fail to protect their information technology systems and our confidential and proprietary information, we may be vulnerable to disruptions in service and unauthorized access to our confidential or proprietary information and we could incur liability and reputational damage.
The secure processing, storage, maintenance and transmission of information is vital to our operations and business strategy, and we devote significant resources to protecting such information. Although we take reasonable measures to protect sensitive data from unauthorized access, use or disclosure, our information technology and infrastructure may still
26
be vulnerable to, and we have in the past experienced, low-threat attacks by hackers or breaches due to employee error, malfeasance or other malicious or inadvertent disruptions. Further, attacks upon information technology systems are increasing in their frequency, levels of persistence, sophistication and intensity, particularly in the healthcare industry in which we operate where there is an increased reliance on internet technology and remote employees. Furthermore, because the techniques used to obtain unauthorized access to, or to sabotage, systems change frequently and often are not recognized until launched against a target, we may be unable to anticipate these techniques or implement adequate preventative measures, which could result in an incident that compromises the security of our networks or information and is undetected for an extended period. Our information systems must also be continually updated, patched and upgraded to protect against known vulnerabilities and the sheer volume and criticality of these patches has increased markedly. Each time a new vulnerability is identified we are at risk that cyber-attackers exploit such known vulnerability before we have been able to address it.
Any unauthorized access, breach, or loss of personal information could result in the disruption of our operations, legal claims or proceedings, and liability under federal or state laws that protect the privacy of personal information, and corresponding regulatory penalties. In addition, we could face criminal liability, damages for contract breach, reputational harm that could impact our ability to compete, and incur significant costs for remedial measures to prevent future occurrences and mitigate past violations. Notice of breaches may be required to be made to affected individuals or other state or federal regulators, and for extensive breaches, notice may need to be made to the media or State Attorneys General. Such a notice could harm our reputation and our ability to compete. Although we maintain insurance covering certain security and privacy damages and claim expenses, we may not carry insurance or maintain coverage sufficient to compensate for all liability and in any event, insurance coverage would not address the reputational damage that could result from a security incident. Despite our implementation of security measures reasonably designed to prevent unauthorized access, there is no guarantee we can protect our data from breach.
Actual or perceived failures to comply with applicable data protection, privacy and security laws, regulations, standards and other requirements, including contractual obligations, could adversely affect our business, financial condition and results of operations.
Numerous state and federal laws, regulations, standards and other legal obligations, including consumer protection laws and regulations, which govern the collection, dissemination, use, access to, confidentiality, security and processing of personal information, including health-related information, could apply to our operations or the operations of our partners.
These privacy and security laws and regulations (including our contractual obligations) are constantly evolving, may conflict with each other, and can result in investigations, procedures, or actions that lead to significant civil and criminal penalties and operational restrictions.
Any failure or perceived failure by us or our employees, representatives, contractors, consultants, collaborators, or other third parties to comply with such requirements or adequately address privacy and security concerns, even if unfounded, could result in additional cost and liability to us, damage our reputation, and adversely affect our business and results of operations.
Changes in U.S. tax laws, and the adoption of tax reform policies could adversely affect our operating results and financial condition.
We are subject to federal and state income and non-income taxes in the United States. Tax laws, regulations, and administrative practices in various jurisdictions may be subject to significant change, with or without notice, due to economic, political, and other conditions, and significant judgment is required in evaluating and estimating these taxes. Our effective tax rates could be affected by numerous factors, such as entry into new businesses and geographies, changes to our existing business and operations, acquisitions and investments and how they are financed, changes in our stock price, changes in our deferred tax assets and liabilities and their valuation, and changes in the relevant tax, accounting, and other laws, regulations, administrative practices, principles and interpretations. We are required to take positions regarding the interpretation of complex statutory and regulatory tax rules and on valuation matters that are subject to uncertainty, and tax authorities may challenge the positions that we take.
Our quarterly results may fluctuate significantly, which could adversely impact the value of our Common Stock.
Our quarterly results of operations, including our revenue, net loss and cash flows, have varied and may vary significantly in the future, and period-to-period comparisons of our results of operations may not be meaningful. Accordingly, our
27
quarterly results should not be relied upon as an indication of future performance. Our quarterly financial results may fluctuate as a result of a variety of factors, many of which are outside of our control, including, without limitation, the following:
•the timing of recognition of revenue, including possible delays in the recognition of revenue due to sometimes unpredictable implementation timelines;
•the amount and timing of operating expenses related to the maintenance and expansion of our business, operations and infrastructure;
•our ability to respond to competitive developments;
•security or data privacy breaches and associated remediation costs; and
•the timing of expenses related to the development or acquisition of additional hospitals or businesses.
Any fluctuation in our quarterly results may not accurately reflect the underlying performance of our business and could cause a decline in the trading price of our Common Stock.
Obligations under the term loans of our hospitals, and our related loan and leases guarantees could restrict our operations, particularly our ability to respond to changes in our business or to take specified actions. An event of default under the term loans could harm our business, and creditors having security interests over the hospital assets as well as the leased real estate would be able to foreclose on such assets.
Each of our hospitals is a party to term loans and lines of credit guaranteed by Nutex Holdco to finance hospital equipment and related assets, for aggregate borrowings of approximately $36.7 million as of December 31, 2025.
In addition, Nutex Holdco subsequently entered into guarantees of finance lease obligations of each of our hospitals and mortgage debt of Real Estate Entities affiliated with Dr. Vo, the Company’s Chairman and Chief Executive Officer.
The term loans and lease and mortgage loan guarantees require us to comply with a number of financial and other obligations, which include maintaining debt service coverage and leverage ratios and maintaining insurance coverage, and may impose significant operating and financial restrictions on us, including restrictions on our ability to take actions that may be in our interests. These obligations may limit our flexibility in our operations, and breaches of these obligations could result in defaults under the term loans or guarantees, even if we had satisfied our payment obligations. Moreover, if we defaulted on these obligations, creditors having security interests over the hospital assets or real estate assets could exercise various remedies, including foreclosing on and selling our assets or the real estate assets underlying our hospitals. Unless waived by creditors, for which no assurance can be given, defaulting on these obligations could result in a material adverse effect on our financial condition and ability to continue our operations.
The arrangements we have with our VIEs are not as secure as direct ownership of such entities.
Because of corporate practice of medicine laws, we entered into contractual arrangements to manage certain affiliated physician practice groups or independent physician associations, which allow us to consolidate those groups for financial reporting purposes. We do not have direct ownership interests in any of our VIEs and are not able to exercise rights as an equity holder to directly change the members of the board of directors of these entities so as to affect changes at the management and operational level. Under our arrangements with our VIEs, we must rely on their equity holders to exercise our control over the entities. If our affiliated entities or their equity holders fail to perform as expected, we may have to incur substantial costs and expend additional resources to enforce such arrangements.
Any failure by our affiliated entities or their owners to perform their obligations under their agreements with us would have a material adverse effect on our business, results of operations and financial condition.
The Physician LLCs are owned by individual physicians who could die, become incapacitated, or become no longer affiliated with us. Although the Management Services Agreements (MSAs) of our hospitals with these affiliates provide that they will be binding on successors of current owners, as the successors are not parties to the MSAs, it is uncertain in case of the death, bankruptcy, or divorce of a current owner whether their successors would be subject to such MSAs.
28
If there is a change in accounting principles or the interpretation thereof affecting consolidation of VIEs, it could impact our consolidation of total revenues derived from our affiliated physician groups.
Our financial statements are consolidated and include the accounts of our majority-wholly owned subsidiary AHP Health Management Services Inc., non-owned affiliated physician groups and real estate entities that each is a VIE, which consolidation is effectuated in accordance with applicable accounting rules promulgated by the FASB. Such accounting rules require that, under some circumstances, the VIE consolidation model be applied when a reporting enterprise holds a variable interest (e.g., equity interests, debt obligations, certain management, and service contracts) in a legal entity. Under this model, an enterprise must assess the entity in which it holds a variable interest to determine whether it meets the criteria to be consolidated as a VIE. If the entity is a VIE, the consolidation framework next identifies the party, if one exists, that possesses a controlling financial interest in the VIE, and then requires that party to consolidate as the primary beneficiary. An enterprise’s determination of whether it has a controlling financial interest in a VIE requires that a qualitative determination be made and is not solely based on voting rights. If an enterprise determines the entity in which it holds a variable interest is not subject to the VIE consolidation model, the enterprise should apply the traditional voting control model which focuses on voting rights.
In our case, the VIE consolidation model applies to our controlled, but not owned, physician-affiliated entities including our IPA and PLLCs. Our determination regarding the consolidation of our affiliates, however, could be challenged, which could have a material adverse effect on our operations. In addition, in the event of a change in accounting rules or FASB’s interpretations thereof, or if there were an adverse determination by a regulatory agency or a court or a change in state or federal law relating to the ability to maintain present agreements or arrangements with our affiliated physician group, we may not be permitted to continue to consolidate the revenues of our VIE.
Risk Related to our Population Health Management Division
New physicians and other providers must be properly enrolled in governmental healthcare programs before we can receive reimbursement for their services, and there may be delays in the enrollment process.
Each time a new physician joins us or our affiliated IPA groups, we must enroll the physician under our applicable group identification number for Medicare and Medicaid programs and for certain managed care and private insurance programs before we can receive reimbursement for services the physician renders to beneficiaries of those programs. The estimated time to receive approval for the enrollment is sometimes difficult to predict and, in recent years, the Medicare program carriers often have not issued these numbers to our affiliated physicians in a timely manner. These practices result in delayed reimbursement that may adversely affect our cash flows.
We may have difficulty collecting payments from third-party payors in a timely manner.
We derive significant revenue from third-party payors, and delays in payment or refunds to payors may adversely impact our net revenue. We assume the financial risks relating to uncollectible and delayed payments. In particular, we rely on some key governmental payors. Governmental payors typically pay on a more extended payment cycle, which could require us to incur substantial expenses prior to receiving corresponding payments. In the current healthcare environment, as payors continue to control expenditures for healthcare services, including through revising their coverage and reimbursement policies, we may continue to experience difficulties in collecting payments from payors that may seek to reduce or delay such payments. If we are not timely paid in full or if we need to refund some payments, our revenues, cash flows, and financial condition could be adversely affected.
Decreases in payor rates could adversely affect us.
Decreases in payor rates, either prospectively or retroactively, could have a significant adverse effect on our revenues, cash flow, and results of operations.
Federal and state laws may limit our ability to collect monies owed by patients.
We use third-party collection agencies whom we do not control to collect from patients any co-payments and other payments for services that our physicians provide. The federal Fair Debt Collection Practices Act of 1977 (the “FDCPA”) restricts the methods that third-party collection companies may use to contact and seek payment from consumer debtors regarding past due accounts. State laws vary with respect to debt collection practices, although most state requirements are similar to those under the FDCPA. Therefore, such agencies may not be successful in collecting payments owed to us and
29
our affiliated physician groups. If practices of collection agencies utilized by us are inconsistent with these standards, we may be subject to actual damages and penalties. These factors and events could have a material adverse effect on our business, results of operations, and financial condition.
We have established reserves for our potential medical claim losses, which are subject to inherent uncertainties, and a deficiency in the established reserves may lead to a reduction in our assets or net incomes.
We establish reserves for estimated Insured but Not Reported ("IBNR") claims. IBNR estimates are developed using actuarial methods and are based on many variables, including the utilization of healthcare services, historical payment patterns, cost trends, product mix, seasonality, changes in membership, and other factors. The estimation methods and the resulting reserves are periodically reviewed and updated.
Many of our contracts are complex in nature and may be subject to differing interpretations regarding amounts due for the provision of various services. Such interpretations may not come to light until a substantial period of time has passed. The inherent difficulty in interpreting contracts and estimating necessary reserves could result in significant fluctuations in our estimates from period to period. Our actual losses and related expenses therefore may differ, even substantially, from the reserve estimates reflected in our financial statements. If actual claims exceed our estimated reserves, we may be required to increase reserves, which would lead to a reduction in our assets or net income.
We do not have a Knox-Keene license.
The Knox-Keene Health Care Service Plan Act of 1975 was passed by the California State Legislature to regulate California managed care plans and is currently administered by the California Department of Managed Healthcare (DMHC). A Knox-Keene Act license is required to operate a healthcare service plan, e.g., an HMO, or an organization that accepts global risk, i.e., accepts full risk for a patient population, including risk related to institutional services, e.g., hospital, and professional services. Applying for and obtaining such a license is a time consuming and detail-oriented undertaking. We currently do not hold any Knox-Keene license. If the DMHC were to determine that we have been inappropriately taking risk for institutional and professional services as a result of our various hospital and physician arrangements without having any Knox-Keene license or applicable regulatory exemption, we may be required to obtain a Knox-Keene license and could be subject to civil and criminal liability, any of which could have a material adverse effect on our business, results of operations, and financial condition.
A Knox-Keene Act license or exemption from licensure, where applicable, is required to operate a healthcare service plan, e.g., an HMO, or an organization that accepts global risk, i.e., accepts full risk for a patient population, including risk related to institutional services, e.g., hospital, and professional services.
If our affiliated physician group is not able to satisfy California financial solvency regulations, they could become subject to sanctions and their ability to do business in California could be limited or terminated.
The DMHC has instituted financial solvency regulations. The regulations are intended to provide a formal mechanism for monitoring the financial solvency of a RBO in California, including capitated physician groups. Under current DMHC regulations, our affiliated physician groups, as applicable, are required to, among other things:
•Maintain, at all times, a minimum “cash-to-claims ratio” (which means the organization’s cash, marketable securities, and certain qualified receivables, divided by the organization’s total unpaid claims liability) of 0.75; and
•Submit periodic reports to the DMHC containing various data and attestations regarding their performance and financial solvency, including IBNR calculations and documentation and attestations as to whether or not the organization (i) was in compliance with the “Knox-Keene Act” requirements related to claims payment timeliness, (ii) had maintained positive tangible net equity (“TNE”), and (iii) had maintained positive working capital.
In the event that a physician group is not in compliance with any of the above criteria, it would be required to describe in a report submitted to the DMHC the reasons for non-compliance and actions to be taken to bring it into compliance. Under such regulations, the DMHC can also make some of the information contained in the reports, public, including, but not limited to, whether or not a particular physician organization met each of the criteria. In the event any of our affiliated physician groups are not able to meet certain of the financial solvency requirements, and fail to meet subsequent corrective action plans, it could be subject to sanctions, or limitations on, or removal of, its ability to do business in California. There can be no assurance that our affiliated physician group, such as our IPA, will remain in compliance with DMHC
30
requirements or be able to timely and adequately rectify non-compliance. To the extent that we need to provide additional capital to our affiliated physician group in the future in order to comply with DMHC regulations, we would have less cash available for other parts of our operations.
Primary care physicians may seek to affiliate with our and our competitors’ IPAs at the same time.
It is common in the medical services industry for primary care physicians to be affiliated with multiple IPAs. Our affiliated IPA therefore may enter into agreements with physicians who are also affiliated with our competitors. However, some of our competitors at times have agreements with physicians that require the physician to provide exclusive services. Our affiliated IPA often has no knowledge, and no way of knowing, whether a physician is subject to an exclusivity agreement without being informed by the physician. Competitors could initiate lawsuits against us alleging in part interference with such exclusivity arrangements. An adverse outcome from any such lawsuit could adversely affect our business, cash flows and financial condition.
If we inadvertently employ or contract with an excluded person, we may face government sanctions.
Individuals and entities can be excluded from participating in the Medicare and Medicaid programs for violating certain laws and regulations, or for other reasons such as the loss of a license in any state, even if the person retains other licensure. This means that the excluded person and others are prohibited from receiving payments for such person’s services rendered to Medicare or Medicaid beneficiaries, and if the excluded person is a physician, all services ordered (not just provided) by such physician are also non-covered and non-payable. Entities that employ or contract with excluded individuals are prohibited from billing the Medicare or Medicaid programs for the excluded individual’s services and are subject to civil penalties if it does. The U.S. Department of Health and Human Services Office of the Inspector General maintains a list of excluded persons. Although we have instituted policies and procedures to minimize such risks, there can be no assurance that we will not inadvertently hire or contract with an excluded person, or that our employees or contracts will not become excluded in the future without our knowledge. If this occurs, we may be subject to substantial repayments and civil penalties which could adversely affect our business, cash flows, and financial condition.
New California privacy regulations require Automated Decision-Making Technology (“ADMT”) transparency and future cybersecurity audits.
Effective January 1, 2026, businesses using ADMT for significant decisions must provide pre-use notices, consumer access/appeal rights, and certain opt-outs, with opt-in for sensitive data. Starting in 2028, businesses meeting specified revenue/data thresholds must complete annual independent cybersecurity audits and risk assessments. These rules can increase operational complexity and costs and may limit certain analytics or automation use cases.
Heightened scrutiny of Medicare Advantage risk-adjustment practices may increase audit and repayment risk.
DOJ has pursued FCA actions alleging improper risk-adjustment submissions; any adverse findings could result in repayments, penalties, and increased compliance costs for entities engaged in MA coding or analytics.
Risks Related to Our Legal and Regulatory Environment
We conduct business in a heavily regulated industry and if we fail to adhere to all of the complex government laws and regulations that apply to our business, we could incur fines or penalties or be required to make changes to our operations or experience adverse publicity, any or all of which could have a material adverse effect on our business, results of operations, financial condition, cash flows, and reputation.
The U.S. healthcare industry is heavily regulated and closely scrutinized by federal, state and local governments. Comprehensive statutes and regulations govern the manner in which we provide and bill for services and collect reimbursement from governmental programs and private payors, our contractual relationships and arrangements with healthcare providers and vendors, our marketing activities and other aspects of our operations. Of particular importance are:
•the federal Anti-Kickback Statute, or the AKS, which prohibits the knowing and willful offer, payment, solicitation or receipt of any bribe, kickback, rebate or other remuneration for referring an individual, in return for ordering, leasing, purchasing or recommending or arranging for or to induce the referral of an individual or the ordering, purchasing or leasing of items or services covered, in whole or in part, by any federal healthcare
31
program, such as Medicare and Medicaid. Although there are several statutory exceptions and regulatory safe harbors protecting certain common activities from prosecution, the exceptions and safe harbors are drawn narrowly. By way of example, the AKS safe harbor for value-based arrangements requires, among other things, that the arrangement does not induce a person or entity to reduce or limit medically necessary items or services furnished to any patient. Failure to meet the requirements of a safe harbor, however, does not render an arrangement illegal, although such arrangements may be subject to greater scrutiny by government authorities. Further, a person or entity does not need to have actual knowledge of the statute or specific intent to violate it to have committed a violation;
•the federal physician self-referral law, or the Stark Law, which, subject to limited exceptions, prohibits physicians from referring Medicare or Medicaid patients to an entity for the provision of certain designated health services, or DHS, if the physician or a member of such physician’s immediate family has a direct or indirect financial relationship (including an ownership interest or a compensation arrangement) with the entity, and prohibits the entity from billing Medicare or Medicaid for such DHS;
•the federal False Claims Act, or the FCA, which imposes civil and criminal liability on individuals or entities that knowingly submit false or fraudulent claims for payment to the government or knowingly make, or cause to be made, a false statement in order to have a false claim paid, including qui tam or whistleblower suits. There are many potential bases for liability under the FCA. The government has used the FCA to prosecute Medicare and other government healthcare program fraud such as coding errors, billing for services not provided, and providing care that is not medically necessary or that is substandard in quality. In addition, we could be held liable under the FCA if we are deemed to “cause” the submission of false or fraudulent claims by, for example, providing inaccurate billing, coding or risk adjustment information to our physician partners through Provider Portal and Analytic Management Tools, respectively. The 2025 NDAA revitalized the AFCA, enabling agencies to pursue administrative penalties and double-damage assessments for smaller cases, complementing DOJ’s traditional FCA actions. DOJ reported significant recoveries in 2025 and signaled broader enforcement priorities. Our billing, coding, and reimbursement practices could face heightened scrutiny, increasing the risk of audits, investigations, penalties, and defense costs. The government may also assert that a claim including items or services resulting from a violation of the AKS or Stark Law constitutes a false or fraudulent claim for purposes of the FCA;
•the Civil Monetary Penalties Statute, which prohibits, among other things, an individual or entity from offering remuneration to a federal healthcare program beneficiary that the individual or entity knows or should know is likely to influence the beneficiary to order or receive healthcare items or services from a particular provider;
•the criminal healthcare fraud provisions of HIPAA and related rules that prohibit knowingly and willfully executing a scheme or artifice to defraud any healthcare benefit program or falsifying, concealing or covering up a material fact or making any material false, fictitious or fraudulent statement in connection with the delivery of or payment for healthcare benefits, items or services. Similar to the AKS, a person or entity does not need to have actual knowledge of the statute or specific intent to violate it to have committed a violation;
•reassignment of payment rules that prohibit certain types of billing and collection practices in connection with claims payable by the Medicare or Medicaid programs;
•similar state law provisions pertaining to anti-kickback, self-referral and false claims issues, some of which may apply to items or services reimbursed by any payor, including patients and commercial insurers;
•laws that regulate debt collection practices;
•a provision of the Social Security Act that imposes criminal penalties on healthcare providers who fail to disclose, or refund known overpayments;
•federal and state laws that prohibit providers from billing and receiving payment from Medicare and Medicaid for services unless the services are medically necessary, adequately and accurately documented, and billed using codes that accurately reflect the type and level of services rendered; and
•federal and state laws pertaining to the provision of services by nurse practitioners and physician assistants in certain settings, physician supervision of those services, and reimbursement requirements that depend on the types of services provided and documented and relationships between physician supervisors and nurse practitioners and physician assistants.
The laws and regulations in these areas are complex, changing and often subject to varying interpretations. As a result, there is no guarantee that a government authority will find that we or our partner physicians or other healthcare professionals are in compliance with all such laws and regulations that apply to our business. Further, because of the breadth of these laws and the narrowness of the statutory exceptions and safe harbors available, it is possible that some of the business activities undertaken by us or our partner physicians or other healthcare professionals could be subject to challenge under one or more of these laws, including, without limitation, our patient assistance programs that waive or reduce the patient’s obligation to pay copayments, coinsurance or deductible amounts owed for the services we provide to them if they meet certain financial need criteria. If our operations are found to be in violation of any of such laws or any
32
other governmental regulations that apply, we may be subject to significant penalties, including, without limitation, administrative, civil and criminal penalties, damages, fines, disgorgement, the curtailment or restructuring of operations, integrity oversight and reporting obligations, exclusion from participation in federal and state healthcare programs and imprisonment. In addition, any action against us or our partner physicians or other physician partners for violation of these laws or regulations, even if we successfully defend against it, could cause us to incur significant legal expenses, divert our management’s attention from the operation of our business and result in adverse publicity, or otherwise experience a material adverse impact on our business, results of operations, financial condition, cash flows, reputation as a result.
If any of our hospitals lose their regulatory licenses, permits and/or registrations, as applicable, or become ineligible to receive reimbursement from third-party payors, there may be a material adverse effect on our business, financial condition, cash flows, or results of operations.
The operations of our hospitals through partner physicians and other healthcare professionals are subject to extensive federal, state and local regulation relating to, among other things, the adequacy of medical care, equipment, personnel, operating policies and procedures and proof of financial ability to operate. Our hospitals and partner physicians and other healthcare professionals are also subject to extensive laws and regulation relating to facility and professional licensure, conduct of operations, including financial relationships among healthcare providers, Medicare, Medicaid and state fraud and abuse and physician self-referrals, and maintaining updates to our and our partner physicians’ and other healthcare professionals’ enrollment in the Medicare and Medicaid programs, including addition of new hospital locations, providers and other enrollment information. Our hospitals are subject to periodic inspection by licensing authorities to assure their continued compliance with these various standards. There can be no assurance that these regulatory authorities will determine that all applicable requirements are fully met at any given time. Should any of our hospitals be found to be noncompliant with these requirements, we could be assessed fines and penalties, could be required to refund reimbursement amounts or could lose our licensure or Medicare and/or Medicaid certification so that we or our partner physicians and other healthcare professionals are unable to receive reimbursement from such programs and possibly from other third-party payors, any of which could materially adversely affect our business, financial condition, cash flows or results of operations.
If our arrangements with our partner physicians and other physician partners are found to constitute the improper rendering of medical services or fee splitting under applicable state laws, our business, financial condition and our ability to operate in those states could be adversely impacted.
Our contractual relationships with our partner physicians may implicate certain state laws that generally prohibit non-professional entities from providing licensed medical services or exercising control over licensed physicians or other healthcare professionals (such activities generally referred to as the “corporate practice of medicine”) or engaging in certain practices such as fee-splitting with such licensed professionals. The interpretation and enforcement of these laws vary significantly from state to state. There can be no assurance that these laws will be interpreted in a manner consistent with our practices or that other laws or regulations will not be enacted in the future that could have a material and adverse effect on our business, financial condition and results of operations. Regulatory authorities, state boards of medicine, state attorneys general and other parties may assert that, despite the agreements through which we operate, we are engaged in the provision of medical services and/or that our arrangements with our physician partners constitute unlawful fee-splitting. If a jurisdiction’s prohibition on the corporate practice of medicine or fee-splitting is interpreted in a manner that is inconsistent with our practices, we would be required to restructure or terminate our arrangements with our physician partners to bring our activities into compliance with such laws. A determination of non-compliance, or the termination of or failure to successfully restructure these relationships could result in disciplinary action, penalties, damages, fines, and/or a loss of revenue, any of which could have a material and adverse effect on our business, financial condition and results of operations. State corporate practice and fee-splitting prohibitions also often impose penalties on healthcare professionals for aiding in the improper rendering of professional services, which could discourage physicians and other healthcare professionals from providing clinical services to our hospitals.
We face inspections, reviews, audits and investigations under federal and state government programs and contracts. These audits could have adverse findings that may negatively affect our business, including our results of operations, liquidity, financial condition and reputation.
As a result of our participation in the Medicare and Medicaid programs, we are subject to various governmental inspections, reviews, audits and investigations to verify our compliance with these programs and applicable laws and
33
regulations. Other third-party payors may also reserve the right to conduct audits. We also periodically conduct internal audits and reviews of our regulatory compliance. An adverse inspection, review, audit or investigation could result in:
•refunding amounts we have been paid pursuant to the Medicare or Medicaid programs or from payors;
•state or federal agencies imposing fines, penalties and other sanctions on us;
•temporary suspension of payment for new patients to the facility or agency;
•decertification or exclusion from participation in the Medicare or Medicaid programs or one or more payor networks;
•self-disclosure of violations to applicable regulatory authorities;
•damage to our reputation;
•the revocation of a facility’s or agency’s license;
•criminal penalties;
•a corporate integrity agreement with HHS’ Office of Inspector General; and
•loss of certain rights under, or termination of, our contracts with payors.
If adverse inspections, reviews, audits or investigations occur and any of the results noted above occur, it could have a material adverse effect on our business and operating results. Furthermore, the legal, document production and other costs associated with complying with these inspections, reviews, audits or investigations could be significant.
Recent healthcare regulations, and other changes in the healthcare industry and in healthcare spending may adversely affect our business, financial condition and results of operations.
The impact on us of healthcare reform legislation and other changes in the healthcare industry and in healthcare spending is uncertain, but may adversely affect our business, financial condition and results of operations. Our revenue is dependent on the healthcare industry and could be affected by changes in healthcare spending, reimbursement and policy. The healthcare industry is subject to changing political, regulatory and other influences. Additionally, the potential impact of new policies that may be implemented as a result of the new administration is currently uncertain.
On January 1, 2022, the NSA became effective. As a result, we experienced a significant decline in collections of patient claims for emergency services. There are numerous continuing legal challenges to the federal regulations promulgated under the NSA, in particular those mandating the methodology of calculating the qualifying payment amount and implementing the independent dispute resolution process, creating significant uncertainty in the claims recovery process. Any resulting decrease in the collections we receive for our emergency services could have a material adverse effect on our operations and financial performance and may negatively affect the trading value of our Common Stock.
Changes to Stark Law DHS codes and exception thresholds may increase compliance risk.
CMS updated the DHS code list for CY 2026, which may expand or contract services subject to Stark restrictions. In addition, the non‑cash compensation exception increased to $535 per physician for 2026, and the “limited remuneration” exception cap increased to $6,237 per physician. Failure to monitor and align provider arrangements to these updated limits could result in noncompliance, repayment, penalties, and contract change
HIPAA rule changes may require operational and documentation updates and raise enforcement exposure.
Following a June 2025 court decision that partially vacated elements of the reproductive health privacy rule, remaining Notice of Privacy Practices (NPP) modifications still require compliance by February 16, 2026. Separately, HHS/OCR has proposed modernization of the HIPAA Security Rule emphasizing robust controls (e.g., asset inventories, multi-factor authentication, vulnerability and incident management). Failure to implement and evidence these measures could increase breach risk and enforcement exposure.
Escalating cyber threats and regulatory expectations may increase costs and disruption risk.
HHS reports large healthcare breaches and individuals affected have surged over recent years, heightening the likelihood of incidents and enforcement. Significant events could cause system outages, deferred patient services, regulatory penalties, contract claims, increased insurance premiums or gaps, and costly remediation.
34
Risks Related to Our Common Stock
Anti-takeover provisions under Delaware law could make an acquisition of the Company, which may be beneficial to the stockholders of the Company, more difficult and may prevent attempts by the stockholders to replace or remove management.
We are subject to the anti-takeover provisions of the Delaware General Corporation Law (“DGCL”), including Section 203. Under these provisions, if anyone becomes an “interested stockholder,” the Company may not enter into a “business combination” with that person for three years without special approval, which could discourage a third party from making a takeover offer and could delay or prevent a change of control. For purposes of Section 203 of the DGCL, “interested stockholder” means, generally, someone owning 15% or more of the Company’s outstanding voting stock or an affiliate of the Company that owned 15% or more of the Company’s outstanding voting stock during the past three years, subject to certain exceptions as described in Section 203 of the DGCL. As such, Section 203 of the DGCL could prohibit or delay mergers or a change in control and may discourage attempts by other companies to acquire the Company.
Additionally, certain provisions in our Charter, such as advance notice provisions for matters to be included in the proxy statement for annual meetings, could make it more difficult for a third party to acquire control of us, even if such change in control would be beneficial to our stockholders.
Because we have no current plans to pay cash dividends on our Common Stock for the foreseeable future, you may not receive any return on investment unless you sell your Common Stock for a price in excess of the purchase price.
We may retain future earnings, if any, for future operations, expansion and debt repayment and have no current plans to pay any cash dividends for the foreseeable future. Any decision to declare and pay dividends will be made at the discretion of our board of directors and will depend on, among other things, our results of operations, financial condition, cash requirements, contractual restrictions and other factors that our board of directors may deem relevant. In addition, our ability to declare dividends may be limited by restrictive covenants contained in any existing or future indebtedness. As a result, you may not receive any return on an investment in our Common Stock unless you sell your Common Stock for a price greater than that which you paid for it.
The market price and trading volume of our Common Stock may be volatile and could decline significantly.
Securities markets worldwide experience significant price and volume fluctuations. This market volatility, as well as general economic, market, or political conditions, could reduce the market price of our Common Stock in spite of our operating performance, which may limit or prevent investors from readily selling their Common Stock and may otherwise negatively affect the liquidity of the Common Stock. There can be no assurance that the market price of Common Stock will not fluctuate widely or decline significantly in the future in response to a number of factors, including, among others, the following:
•actual or anticipated fluctuations in our quarterly financial results or the quarterly financial results of companies perceived to be similar to us;
•changes in the market’s expectations about our operating results;
•success of competitors;
•our operating results failing to meet the expectation of securities analysts or investors in a particular period;
•changes in financial estimates and recommendations by securities analysts concerning us or the health population management industry in general;
•operating and stock price performance of other companies that investors deem comparable to us;
•our ability to market new and enhanced products on a timely basis;
•changes in laws and regulations affecting our business;
•our ability to meet compliance requirements;
•commencement of, or involvement in, litigation involving us;
•changes in our capital structure, such as future issuances of securities or the incurrence of additional debt;
•the volume of shares of our Common Stock available for public sale;
•any major change in our board of directors or management;
•sales of substantial amounts of Common Stock by our directors, executive officers or significant stockholders or the perception that such sales could occur; and
•general economic and political conditions such as recessions, interest rates, fuel prices, international currency fluctuations and acts of war or terrorism.
35
The stock market in general, and Nasdaq in particular, have experienced price and volume fluctuations that have often been unrelated or disproportionate to the operating performance of the particular companies affected. The trading prices and valuations of these stocks, and of our securities, may not be predictable. A loss of investor confidence in the market for retail stocks or the stocks of other companies which investors perceive to be similar to us could depress our stock price regardless of our business, prospects, financial condition or results of operations. A decline in the market price of our securities also could adversely affect our ability to issue additional securities and our ability to obtain additional financing in the future.
If securities or industry analysts do not publish research or publish inaccurate or unfavorable research about our business, the price and trading volume of our securities could decline.
The trading market for our securities depends in part on the research and reports that securities or industry analysts publish about us or our business. We will not control these analysts, and the analysts who publish information about us may have relatively little experience with us or our industry, which could affect their ability to accurately forecast our results and could make it more likely that we fail to meet their estimates. If few or no securities or industry analysts cover us, the trading price for our securities would be negatively impacted. If one or more of the analysts who covers us downgrades our securities, publishes incorrect or unfavorable research about us, ceases coverage of us, or fails to publish reports on us regularly, demand for and visibility of our securities could decrease, which could cause the price or trading volumes of our securities to decline.
Item 1B. Unresolved Staff Comments
None.
Item 1C. Cybersecurity
Nutex manages cybersecurity and data protection through a continuously evolving framework. The framework allows us to identify, assess and mitigate the risks we face , and assists us in establishing policies and safeguards to protect our systems and the information of those we serve.
Our cybersecurity program is managed by our Director of Information Technology and Chief Operating Officer The Audit Committee of the Board of Directors has oversight of our cybersecurity program and is responsible for reviewing and assessing the Company’s cybersecurity and data protection policies, procedures and resource commitment, including key risk areas and mitigation strategies. As part of this process, the Audit Committee receives regular updates from the Director of Information Technology and Chief Operating Officer on critical issues related to our information security risks, cybersecurity strategy, supplier risk and business continuity capabilities .
The Company’s framework includes an incident management and response program that continuously monitors the Company’s information systems for vulnerabilities, threats and incidents; manages and takes action to contain incidents that occur; remediates vulnerabilities; and communicates the details of threats and incidents to management, including the Director of Information Technology and Chief Operating Officer, as deemed necessary or appropriate. Pursuant to the Company’s incident response plan, incidents are reported to the Audit Committee, appropriate government agencies and other authorities, as deemed necessary or appropriate, considering the actual or potential impact, significance and scope.
To ensure that our program is designed and operating effectively, our infrastructure and information systems are audited periodically by internal and external auditors. We will perform regular vulnerability assessments and penetration tests to improve system security and address emerging security threats. Our internal audit team independently assesses security controls against our enterprise policies to evaluate compliance and leverages a combination of auditing and security frameworks to evaluate how leading practices are applied throughout our enterprise. Audit results and remediation progress are reported to and monitored by senior management and the Audit Committee.
36
We complete an enterprise information risk assessment as part of our overall enterprise information security risk management assessment, which is overseen by our Director of Information Technology and Chief Operating Officer. This risk assessment is a review of internal and external threats that evaluates changes to the information risk landscape to inform the investments and program enhancements to be made in the future to rapidly respond and recover from potential attacks, including rebuild and recovery protocols for key systems. We evaluate our enterprise information security risk to ensure we address any unexpected or unforeseen changes in the risk environment or our systems and the resulting impacts are communicated to the Company’s overall enterprise risk management program.
We believe our Director of Information Technology and Chief Operating Officer have the appropriate knowledge and expertise to effectively manage our cybersecurity program. The Director of Information Technology had more than 25 years of information technology experience across the healthcare industry before joining Nutex. The Chief Operating Officer had more than 20 years of in-depth knowledge of business operations prior to joining Nutex, and we believe will be helpful in integrating our cybersecurity program into our overall business operations.
As of December 31, 2025, the Company has not identified any risks from cybersecurity threats that have materially affected or are reasonably likely to materially affect the Company , including our business strategy, results of operations or financial condition, but there can be no assurance that any such risk will not materially affect the Company in the future. For further information about the cybersecurity risks we face, and potential impacts, see Part I, Item 1A, “Risk Factors.”
Item 2. Properties
Our principal executive office is located at 1776 Yorktown Street, Suite 700, Houston, Texas, which we own. We also maintain corporate offices located at 2455 East Sunrise Blvd., Suite 1204, Fort Lauderdale, Florida, which are leased. As of December 31, 2025, our hospital division operated 26 micro-hospitals, specialty hospitals and HOPDs in 12 states in the U.S. We lease 25 locations. The one hospital division micro-hospital building we own is located at 7904 Cabela Dr, Hammond, Indiana. Our population health management division manages three IPAs and two MSOs, which operate from leased locations in two states. We believe that our current facilities are in good condition and adequate to meet our operating needs for the present and immediately foreseeable future.
Item 3. Legal Proceedings
The Company, its consolidated subsidiaries or VIEs are involved in a number of lawsuits and other proceedings arising from the normal course of business. Given the indeterminate amounts sought and the inherent unpredictability of litigation, it is possible that an adverse outcome in certain of these matters could have a material adverse effect on the Company’s financial condition or results of operations in future periods. Based upon counsel and management’s opinion, except for the items listed below, the outcome of such matters is currently not expected to have a material adverse effect on the audited consolidated financial statements.
On April 14, 2025, VLS Emergency Medicine, LLC, Astra Assets, LLC, Right on Hereford, LLC, and Nexus Group Two LLC (collectively, the “ABQ Plaintiffs”) filed an Original Petition against Nutex Health Holdco LLC (“Nutex Holdco”) and Thomas Vo, MD in the District Court of Harris County, Texas, Case No. 2025-26239. The ABQ Plaintiffs allege that the May 16, 2024 Amendment to the Contribution Agreement, dated November 23, 2021, was wrongfully executed by Nutex Holdco and Dr. Vo, in his capacity as the authorized “Owner Representative” (as defined in the Contribution Agreement). The Amendment clarifies that the Parent Stock Price Floor, as defined in the Contribution Agreement, is adjusted for the 2024 Reverse Stock Splits. The Parent Stock Price Floor is used in the determination of the number of shares to be issued to the ABQ Plaintiffs. Rejecting the reverse-stock-split adjustment, the ABQ Plaintiffs demand the issuance of a higher number of shares, which would force the Company to grant the ABQ Plaintiffs a higher percentage ownership in the Company, to the detriment of the Company’s other stockholders.
Nutex Holdco and Dr. Vo have filed their answers and counterclaims, addressing the allegations set forth and presenting their own claims against the ABQ Plaintiffs. The parties are engaged in written discovery and are in the process of taking key witness depositions. At this time, no dispositive motions have been filed. Trial is currently set for September 21, 2026. Nutex Health disputes the allegation that the Amendment was wrongfully executed and intends to defend against the ABQ Plaintiffs’ demands. The Company cannot guarantee that the ABQ Plaintiffs will not prevail in their demands, which would have a materially adverse effect on the Company and its stockholders. Please see Item 1A. Risk Factors - Our obligation to issue additional shares of our common stock to former owners of under construction hospitals may cause additional dilution of our current stockholders.
37
In addition, on May 30, 2025, JBS Fort Smith Hospital Investors, LP, Copper Oaks Emergency Physicians, LLC, KG4JB 5578, PLLC, Mark R. Rucker, PLLC, Premier Macy Management Holdings, LLC, Nicut EMS, LLC, and Tribbey Emergency Services, LLC (collectively the “Former Ft. Smith Owners”) submitted a Notice of Claim and Draft Complaint (“Notice”) to Nutex Holdco. In the Notice, the Former Ft. Smith Owners demand that the pre-reverse split Parent Stock Price Floor shall be used in the calculation of the number of shares to be issued. The parties are currently engaged in settlement discussions. The Company is unable to predict the outcome of these discussions or determine whether any resolution of the demands made in the Notice will have a materially adverse effect on the Company and its stockholders.
Securities Action
On August 22, 2025, a putative securities class action complaint was filed in the United States District Court for the Southern District of Texas, currently captioned In re Nutex Health Inc. Securities Litigation, Case No. 4:25-cv-03999. The complaint, as amended, is on behalf of two plaintiffs and all other persons (other than defendants) who purchased Nutex Health Inc.’s stock between February 5, 2025 and August 14, 2025. The complaint names Nutex Health Inc., its Chairman of the Board and Chief Executive Officer, its Chief Financial Officer and its President and Director as defendants and asserts claims under Sections 10(b) and 20(a) of the Securities Exchange Act of 1934 (the “Exchange Act”) and Rule 10b-5 promulgated thereunder.
The plaintiffs allege that the defendants made material misstatements and omissions in the Company’s public filings relating to the alleged conduct of a third-party vendor who assisted the Company in pursuing claims against health plans under the independent dispute resolution process of the No Surprises Act. The plaintiffs also allege that the defendants made material misstatements and omissions related to the Company’s internal controls over financial reporting and its accounting treatment of certain non-cash stock-based compensation obligations. The plaintiffs seek unspecified damages, fees, and interest on behalf of themselves and the putative class.
The Company has not yet responded to the complaint but expects to file a motion to dismiss on or about April 3, 2026. The Company is unable to predict the outcome of the litigation or estimate the potential financial impact, but an adverse ruling could have a material adverse effect on the Company’s financial position or results of operations.
Derivative Actions
On September 8, 2025, a purported stockholder filed a derivative action on behalf of Nutex Health Inc. in the United States District Court for the Southern District of Texas, captioned Juan Camilo Jimenez, derivatively on behalf of Nutex Health Inc., Case No. 4:25-cv-04253, naming as defendants the Company’s Chief Executive Officer, its Chief Financial Officer and its President, along with the current members of its Board of Directors (other than Frank E. Jaumot) and a director who recently retired from the Board of Directors, alleging, among other things, violations of Section 14(a) of the Exchange Act, breaches of fiduciary duties, unjust enrichment, abuse of control, gross mismanagement, and waste of corporate assets. In addition, on September 11, 2025, a second purported stockholder filed a derivative action on behalf of Nutex Health Inc. in the United States District Court for the Southern District of Texas, captioned Michael Minckler, derivatively on behalf of Nutex Health Inc., nominal defendant v. Thomas T. Vo, et al; Case no. 4:25-cv-4330 containing nearly identical allegations. The derivative actions arise from the same operative facts as alleged in the securities class action, and they seek orders permitting the plaintiff to maintain the action derivatively on behalf of the Company, awarding unspecified damages allegedly sustained by the Company, awarding restitution from the individual defendants and requiring the Company to make certain reforms to its corporate governance and internal procedures.
On November 25, 2025, the court consolidated the two derivative actions under the caption In re Nutex Health Inc. Derivative Litigation, Case No. 4:25-cv-04253. On December 11, 2025, the court stayed the litigation until resolution of the forthcoming motion to dismiss the securities action described earlier. The Company is unable to predict the outcome of the litigation or estimate the potential financial impact, if any.
Item 4. Mine Safety Disclosures
Not applicable.
38
PART II
Item 5. Market for Registrant’s Common Equity and Related Shareholder Matters.
Our common stock is quoted on NASDAQ Capital Market under the symbol “NUTX.”
Stockholders
As of December 31, 2025, there are approximately 834 stockholders of record of our common stock based upon our transfer agent’s report. Because many of our shares of common stock are held by brokers and other nominees on behalf of stockholders, including in trust, we are unable to estimate the total number of stockholders represented by these record holders.
Dividends
We have not declared or paid any cash dividends on our common stock. To date we have utilized all available cash to finance our operations. Payment of cash dividends in the future will be at the discretion of our Board of Directors and will depend upon our earnings levels, capital requirements, any restrictive loan covenants and other factors the Board considers relevant.
Warrants
At December 31, 2025, there were 144,620 warrants outstanding for the purchase of Company common stock. Refer to Note 13 - Equity to the consolidated financial statements included in this Annual Report for additional information relating to outstanding warrants.
Equity Compensation Plans
In 2023, the stockholders of the Company approved the Amended and Restated Nutex Health Inc. 2023 Equity Incentive Plan (the “2023 Plan”), providing a total of 73,426 shares of Common Stock (11,013,943 prior to the 2024 Reverse Stock Splits) for issuance. Awards granted under the 2023 Plan may be incentive stock options, non-statutory stock options, restricted stock, restricted stock units, stock appreciation rights, performance units or performance shares. The awards are granted at an exercise price equal to the fair market value on the date of grant. The 2023 Plan is subject to annual increases on January 1st of each calendar year through January 1, 2033 of up to 1% of the issued and outstanding shares of the Company’s Common Stock on the final day of the preceding calendar year, at the discretion of the Compensation Committee of our Board of Directors. During the second quarter of 2024, the number of shares to be issued under the 2023 Plan increased to 118,563 shares, most of which were issued as restricted stock units in June 2024.
On July 14, 2025, stockholders of the Company approved an amendment to the 2023 Plan to increase the number of shares available for issuance under the Plan by 1,100,000 over the 10 year term of the Plan and to allow the number of shares available to automatically increase on January 1st of each calendar year through January 1, 2033 in an amount equal to 5% of the number of outstanding shares at December 31 of the previous fiscal year, provided that the Board may decide that there shall be no or lesser increase. Shares available for issuance as of December 31, 2025, were 1,108,911.
At December 31, 2025, there were 17,183 options outstanding for the purchase of Common Stock. Refer to Note 12 - Stock-based Compensation to the consolidated financial statements included in this Annual Report for additional information relating to outstanding options.
Recent Sales of Unregistered Securities
On March 26, 2024, the Company and the holders of the Unsecured Convertible Term Notes agreed to amend the conversion price and the exercise price of the related Warrants to $30.00 each ($0.20 prior to the 2024 Reverse Stock Splits), resulting in the Unsecured Convertible Term Notes being convertible into 179,500 shares of common stock (26,925,000 prior to the 2024 Reverse Stock Splits), the Warrants exercisable for 89,750 shares of common stock (13,462,500 prior to the 2024 Reverse Stock Splits) and the placement agent Warrants exercisable for 53,850 shares of common stock (8,077,500 prior to the 2024 Reverse Stock Splits). These warrants were issued in a private placement in reliance on section 4(a)(2) of the Securities Act.
39
Issuer Purchases of Equity Securities
On August 14, 2025, the Board authorized a stock repurchase program (the "Repurchase Program") of up to $25.0 million of the Company’s common stock over the subsequent six months. Pursuant to the Repurchase Program, the Company may repurchase, from time to time, up to an aggregate of $25.0 million of its outstanding shares of common stock, exclusive of any fees, commissions or other expenses related to such repurchases. The Repurchase Program permits the Company to repurchase shares of common stock at any time or from time to time at management’s discretion in open market transactions made in accordance with the provisions of Rule 10b-18 and/or Rule 10b5-1 under the Securities Exchange Act of 1934, as amended, privately negotiated transactions or by other means in accordance with applicable securities laws.
The Repurchase Program authorization does not obligate the Company to acquire any shares of its common stock and may be amended, suspended or discontinued at any time. Any share repurchases made under the Repurchase Program may be subject to a U.S. federal excise tax. Subject to certain exceptions and adjustments, the amount of the excise tax is generally 1% of the aggregate fair market values of the shares of stock repurchased by the corporation during a taxable year, net of the aggregate fair market value of certain new stock issuances by the repurchasing corporation during the same taxable year.
The following table provides information with respect to shares of our common stock we repurchased under the Repurchase Program during the three months ended December 31, 2025:
| Period | Total number of shares purchased | Average price paid per share | Total number of shares purchased as part of publicly announced plans or programs | Approximate $ value of shares that may yet be purchased under the plans or programs (in '000s) | ||||||||||
| 10/1/25 - 10/31/25 | — | $ | — | — | $ | 25,000 | ||||||||
| 11/1/25 - 11/30/25 | — | $ | — | — | $ | 25,000 | ||||||||
| 12/1/25 - 12/31/25 | 27,870 | $ | 177.70 | 27,870 | $ | 20,047 | ||||||||
| 27,870 | 27,870 | |||||||||||||
Future share repurchases under our Repurchase Program are at the discretion of management, taking into consideration our historical and projected results of operations, financial condition, cash flows, capital requirements, covenant compliance, current economic environment and other factors considered relevant. At December 31, 2025, we had approximately $20.0 million available under the Repurchase Program.
In January 2026, subsequent to year end, the Company repurchased the remaining shares available under the Repurchase Program for an aggregate purchase price of $20.0 million, thereby completing the Repurchase Program.
On March 4, 2026, subsequent to year end, the Company announced that the Board authorized a second stock repurchase program of up to $25.0 million of the Company's common stock. Pursuant to the stock repurchase program the Company may repurchase, from time to time, up to an aggregate of $25.0 million of its outstanding shares of common stock, exclusive of any fees, commissions or other expenses related to such repurchases. The stock repurchase program permits the Company to repurchase shares of common stock at any time or from time to time at management’s discretion in open market transactions made in accordance with the provisions of Rule 10b-18 and/or Rule 10b5-1 under the Securities Exchange Act of 1934, as amended, privately negotiated transactions or by other means in accordance with applicable securities laws.
Stock Performance Graph
The graph set forth below compares the cumulative total stockholder return on our common stock between April 5, 2022 (the date of the first available closing price for Nutex Health Inc. on the NASDAQ following the merger of Nutex Health Holdco LLC and Clinigence Holdings, Inc. on April 1, 2022) and December 31, 2025, with the cumulative total return of (i) the NASDAQ-100 Index and (ii) NASDAQ Health Care Index, over the same period. This graph assumes the investment of $100 on April 5, 2022 at the closing sale price of our common stock, the NASDAQ-100 Index and the NASDAQ Health Care Index and assumes the quarterly reinvestment of dividends, if any, before consideration of income taxes.
40
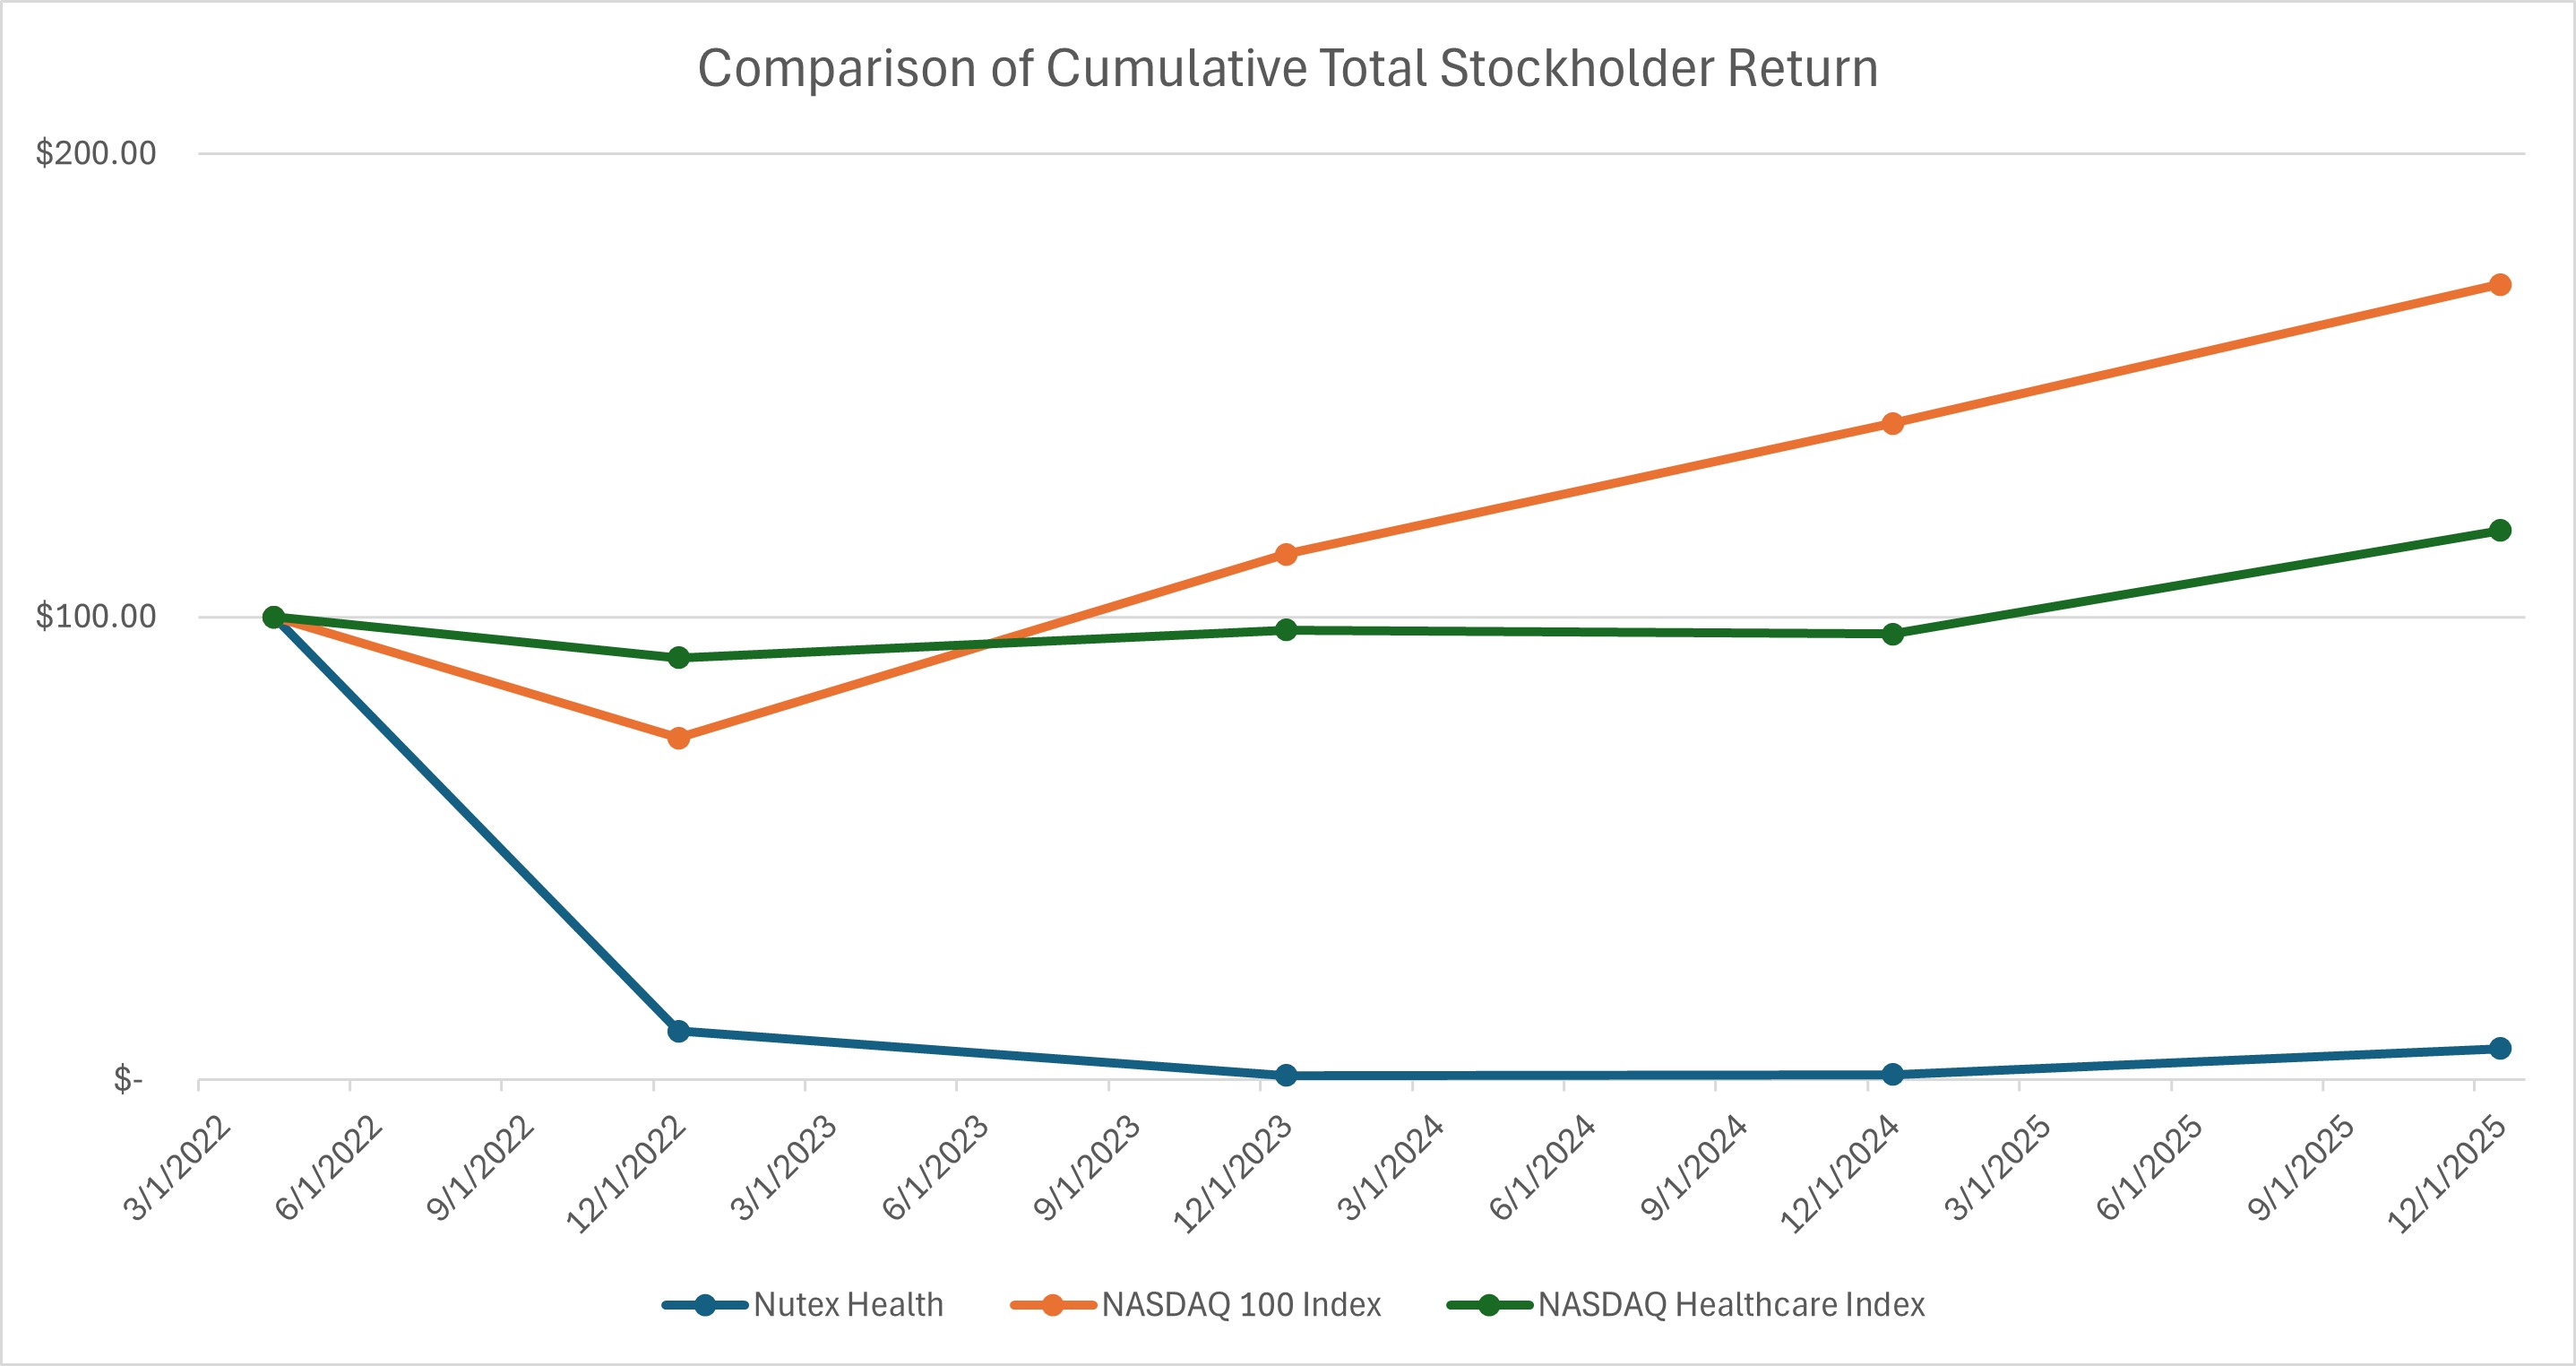
| 4/5/2022 | 12/31/2022 | 12/31/2023 | 12/31/2024 | 12/31/2025 | ||||||||||||||||||||||||||||
| Nutex Health | $ | 100.00 | $ | 10.61 | $ | 1.01 | $ | 1.18 | $ | 6.13 | ||||||||||||||||||||||
| NASDAQ 100 Index | $ | 100.00 | $ | 73.81 | $ | 113.53 | $ | 141.78 | $ | 170.37 | ||||||||||||||||||||||
| NASDAQ Healthcare Index | $ | 100.00 | $ | 91.21 | $ | 97.17 | $ | 96.34 | $ | 118.11 | ||||||||||||||||||||||
Except to the extent that we specifically incorporate this information by reference, the foregoing Stockholder Performance Graph shall not be deemed incorporated by reference by any general statement incorporating by reference this Annual Report on Form 10-K into any filing under the Securities Act of 1933, as amended, or under the Securities Exchange Act of 1934, as amended. This information shall not otherwise be deemed filed under such Acts.
Item 6. Reserved
Not applicable.
Item 7. Management’s Discussion and Analysis of Financial Condition and Results of Operations
The following discussion is intended to assist you in understanding our results of operations and our present financial condition and contains forward-looking statements that reflect our future plans, estimates, beliefs and expected performance. The forward-looking statements are dependent upon events, risks and uncertainties that may be outside our control. We caution you that our actual results could differ materially from those discussed in these forward-looking statements. Factors that could cause or contribute to such differences are discussed elsewhere in this Annual Report, particularly in the “Cautionary Note Regarding Forward-Looking Statements” and “Risk Factors,” all of which are difficult to predict. In light of these risks, uncertainties and assumptions, the forward-looking events discussed may not occur. We do not undertake any obligation to publicly update any forward-looking statements except as otherwise required by applicable law.
Overview
Nutex Health Inc. is a physician-led, healthcare services and operations company with 26 hospital facilities in 12 states (hospital division), and a primary care-centric, risk-bearing population health management division. Our hospital division implements and operates innovative health care models, including micro-hospitals, specialty hospitals and hospital outpatient departments (“HOPDs”). The population health management division owns and operates provider networks such as independent physician associations (“IPAs”) and offers a cloud-based proprietary technology platform to IPAs which aggregates clinical and claims data across multiple settings, information systems and sources to create a holistic view of patients and providers.
At December 31, 2025, we employed approximately 944 full-time employees, contracted more than 280 doctors at our facilities and partnered with over 3,600 physicians within our networks. Our corporate headquarters is based in Houston, Texas. We were incorporated on April 13, 2000 in the state of Delaware.
41
Our financial statements present the Company’s consolidated financial condition and results of operations including those of majority-owned subsidiaries and variable interest entities (“VIEs”) for which we are the primary beneficiary.
The hospital division includes our healthcare billing and collections organization and hospital entities. In addition, we have financial and operating relationships with multiple professional entities (the “Physician LLCs”) and real estate entities (the “Real Estate Entities”). The Physician LLCs employ the doctors who work in our hospitals. These Physician LLCs are consolidated by the Company as VIEs because they do not have sufficient equity at risk to finance their activities independently. The Company is considered the primary beneficiary of these entities because (i) it has the power to direct the activities that most significantly affect their economic performance through its contractual and operational oversight, and (ii) it has the obligation to absorb losses and the right to receive benefits that could be significant, as evidenced by the Company’s historical practice of providing financial support during periods of cash shortfall and receiving the benefit of services.
The Real Estate Entities own the land and hospital buildings which are leased to our hospital entities. The Real Estate Entities have mortgage loans payable to third parties which are collateralized by the land and buildings. We consolidate the Real Estate Entities as VIEs in instances where our hospital entities are guarantors or co-borrowers under their outstanding mortgage loans. As of December 31, 2025, two Real Estate Entities continue to be consolidated in our financial statements as VIEs.
The Company has no direct or indirect ownership interest in the Physician LLCs. The Company has no direct or indirect interests in the Real Estate Entities except for the two noted above and a 51% ownership in the May 2025 Acquiree (see Note 3 - Mergers, Acquisitions and Divestitures), so 100% of the equity for these entities is shown as noncontrolling interest in the consolidated balance sheets and statements of operations.
The population health management division includes our management services organizations. In addition, Atlas Healthcare Physicians (“Atlas”, formerly known as “Associated Hispanic Physicians of So. California”), a physician-affiliated entity that is not owned by us—is consolidated as a VIE of our wholly-owned subsidiary AHP since we are the primary beneficiary of their operations under AHP’s management services contracts with them.
Sources of revenue. Our hospital division recognizes net patient service revenue for contracts with patients and in most cases a third-party payor (commercial insurance, workers compensation insurance or, in limited cases, Medicare/Medicaid).
We receive payment for facility services rendered by us from federal agencies, private insurance carriers, and patients. The Physician LLCs receive payment for doctor services from these same sources. On average, greater than 99% of our net patient service revenue is paid by insurers, federal agencies, and other non-patient third parties. The remaining revenues are paid by our patients in the form of copays, deductibles, and self-payment. We generally operate as an out-of-network provider and, as such, do not have negotiated reimbursement rates with insurance companies.
The following tables present the allocation of the transaction price with the patient between the primary patient classification of insurance coverage:
| Year Ended December 31, | ||||||||||||||||||||
| 2025 | 2024 | 2023 | ||||||||||||||||||
| Insurance | 97 | % | 94 | % | 93 | % | ||||||||||||||
| Self pay | 1 | % | 3 | % | 4 | % | ||||||||||||||
| Workers compensation | 1 | % | 2 | % | 2 | % | ||||||||||||||
| Medicare/Medicaid | 1 | % | 1 | % | 1 | % | ||||||||||||||
| Total | 100 | % | 100 | % | 100 | % | ||||||||||||||
The population health management division recognizes revenue for capitation and management fees for services to IPAs monthly. Capitation revenue consists primarily of capitated fees for medical services provided by physician-owned entities we consolidate as VIEs. Capitated arrangements are made directly with various managed care providers including HMOs. Capitation revenues are typically paid to us monthly in the period services are provided based on the number of enrollees selecting us as their healthcare provider. Capitation is a fixed payment amount per patient per unit of time paid in advance
42
for the delivery of health care services, whereby the service providers are generally liable for excess medical costs. We receive management fees that are based on gross capitation revenues of the IPAs or physician groups we manage.
Our growth strategy. We plan to expand our operations by expanding our clinical services at our existing facilities, by entering new market areas either through development of new hospitals, formation of new IPAs or by making acquisitions. We expect to open three new hospital facilities by the end of 2026. These facilities are either under construction or in advanced planning stages. We anticipate launching one-to-three additional IPAs per year, principally in geographic areas around our existing micro-hospitals.
Industry Trends
The demand for healthcare services continues to be impacted by the following trends:
•Regulatory uncertainty;
•A growing focus on healthcare spending by consumers, employers and insurers, who are actively seeking lower-cost care solutions;
•A shift in patient volumes from inpatient to outpatient settings due to technological advancements and demand for care that is more convenient, affordable and accessible;
•The growing aged population, which requires greater chronic disease management and higher-acuity treatment; and
•Ongoing consolidation of providers and insurers across the healthcare industry.
The healthcare industry, particularly emergency care hospitals, continues to be subject to ongoing regulatory uncertainty. Changes in federal or state healthcare laws, regulations, funding policies or reimbursement practices, especially those involving reductions to government payment rates or limitations on what providers may charge, could significantly impact future revenue and operations. For example, the No Surprises Act prohibits providers from charging patients an amount beyond the in-network cost sharing amount for services rendered by out-of-network providers, subject to limited exceptions. For services for which balance billing is prohibited, the No Surprises Act includes provisions that may limit the amounts received by out-of-network providers from health plans. Any reduction in the rates that we can charge or amounts we can receive for our services will reduce our total revenue and our operating margins.
Results of Operations
We report the results of our operations as three segments in our consolidated financial statements: (i) the hospital division, (ii) the population health management division and (iii) the real estate division. Activity within our business segments is significantly impacted by the demand for healthcare services we provide, competition for these services in each of the market areas we serve, and the legislative changes discussed above.
43
Following is our results of operations for the periods shown (in thousands):
| Year ended December 31, | |||||||||||||||||
| 2025 | 2024 | 2023 | |||||||||||||||
| Revenue: | |||||||||||||||||
| Hospital division | $ | 844,162 | $ | 449,064 | $ | 218,070 | |||||||||||
| Population health management division | 31,095 | 30,885 | 29,576 | ||||||||||||||
| Total revenue | 875,257 | 479,949 | 247,646 | ||||||||||||||
| Segment operating income (loss): | |||||||||||||||||
| Hospital division | 444,027 | 195,539 | 36,336 | ||||||||||||||
| Population health management division | 690 | 1,380 | (1,559) | ||||||||||||||
| Real estate division | (436) | (658) | (3) | ||||||||||||||
| Total segment operating income | 444,281 | 196,261 | 34,774 | ||||||||||||||
| Corporate and other costs: | |||||||||||||||||
| Facilities closing costs | — | — | 217 | ||||||||||||||
| Acquisition costs | — | — | 44 | ||||||||||||||
| Stock-based compensation | 117,003 | 16,555 | 2,836 | ||||||||||||||
| Impairment of assets | — | 3,887 | 29,082 | ||||||||||||||
| Impairment of goodwill | — | 3,197 | 1,139 | ||||||||||||||
| General and administrative expenses | 51,653 | 41,924 | 33,230 | ||||||||||||||
| Total corporate and other costs | 168,656 | 65,563 | 66,548 | ||||||||||||||
| Interest expense | 22,226 | 19,932 | 16,318 | ||||||||||||||
| Loss on warrant liability | — | 1,609 | — | ||||||||||||||
| Other expense (income) | 8,618 | (669) | 399 | ||||||||||||||
| Income (loss) before taxes | 244,781 | 109,826 | (48,491) | ||||||||||||||
| Income tax expense (benefit) | 64,424 | 15,020 | (5,067) | ||||||||||||||
| Net income (loss) | 180,357 | 94,806 | (43,424) | ||||||||||||||
| Less: net income attributable to noncontrolling interests | 109,568 | 42,709 | 2,363 | ||||||||||||||
| Net income (loss) attributable to Nutex Health Inc. | $ | 70,789 | $ | 52,097 | $ | (45,787) | |||||||||||
| Adjusted EBITDA | $ | 259,565 | $ | 102,774 | $ | (5,830) | |||||||||||
Year Ended December 31, 2025 Compared to Year Ended December 31, 2024
We reported net income attributable to Nutex Health Inc. of $70.8 million, or earnings of $10.48 per share, for 2025 as compared with a net income attributable to Nutex Health Inc. of $52.1 million, or earnings of $9.69 per share, for 2024. Our 2025 results were principally affected by:
•Patient visits rose by 11.8% for the year ended December 31, 2025, compared to the same period in 2024. Mature hospitals experienced an average visit growth of 1.3% year-over-year, alongside the impact of two new hospital openings in 2025.
•Increased revenue per visit due to success in efforts to obtain higher rates through the Independent Dispute Resolution ("IDR") process and increased utilization of higher paid services such as increased observation and in-patient stays.
•Higher stock-based compensation in the form of one-time obligations of earn-out shares issuable to qualifying under construction and ramping hospitals of $117.0 million for 2025, an increase of $100.4 million compared to 2024.
•Higher income tax expense of $64.4 million for 2025, an increase of $49.3 million compared to 2024.
•Higher other expenses of $8.6 million for 2025 compared to income of $0.7 million for 2024. The increased expenses for 2025 related primarily to distributions to ramping hospitals' partners.
44
Adjusted EBITDA for 2025 was $259.6 million as compared to $102.8 million for 2024. Refer to Non-GAAP Financial Measures discussed below for a definition and reconciliation of Adjusted EBITDA.
A discussion of our segment results is included below.
Hospital Division. Our revenue for 2025 totaled $844.2 million as compared to $449.1 million for 2024, an increase of $395.1 million, or 88%. Our revenue for 2025 was positively affected by an increase in revenue per visit due to success in efforts to obtain higher rates through the IDR process, an increase in visits and increased utilization of higher paid services such as increased observation and in-patient stays. The following table shows the number of patient visits during the periods:
| Year ended December 31, | |||||||||||
| 2025 | 2024 | ||||||||||
| Patient visits: | |||||||||||
| Hospital | 188,279 | 168,388 | |||||||||
Effective May 1, 2024, we engaged HaloMD, a third-party IDR vendor, to further support our out of network claims appeals and determine which claims would be beneficial to arbitrate. The IDR process can take up to three to five months to receive payments relative to the start of a claim’s open negotiation process. In order to facilitate the dispute arbitration process, the Company incurred fees to the Centers for Medicare and Medicaid Services (“CMS”), the organizations that arbitrate the payment amount between the plan and providers (“IDRE”), and commission and fees to the third-party IDR vendor. Total accrued arbitration expenses were $49.7 million and $47.7 million as of December 31, 2025 and 2024, respectively.
For these reasons, in 2024 we refined our estimates of variable consideration and revenue recognition timing, particularly to claims subject to arbitration. The new methodology incorporates historical arbitration outcomes, payment history, and expected resolution timing in determining the expected transaction price for applicable claims. The result of this change in estimate increased our estimate of the ultimate amounts of accounts receivable we will collect for the current and prior periods. This change in estimate increased revenue and net income before tax for the year ended December 31, 2024 by approximately $169.7 million and $112.0 million, respectively.
The hospital division’s operating income was $444.0 million during 2025, increase of 127% as compared to $195.5 million in the same period of 2024. Our operating income for 2025 was positively affected by an increase in net revenue as noted above. Our contract services expense increased by $89.6 million primarily due to the cost associated with the IDR process. Our payroll expense increased by $40.6 million due to the opening of two facilities in 2025 as well as due to the accrual of bonus payable in 2026.
Population Health Management Division. We completed our reverse business combination with Clinigence in April 2022. Legacy Clinigence’s operations are reported as the population health management division. Our total revenue for 2025 for this division was $31.1 million consisting of capitation revenue of $28.1 million and management fees of $3.0 million. Capitation revenue is recognized by our consolidated VIE, Atlas. We do not have an equity interest in this VIE but consolidate it since we are the primary beneficiary of its operations under our management services contract with them. We also earn management fees under our management services contracts with other IPAs and MSOs which are reported as revenue.
The population health management division had $0.7 million of operating income for 2025 driven by significant membership growth and the higher claims experience associated with newly enrolled members.
Real Estate Division. This division reports on the operations of consolidated Real Estate Entities where we provide guarantees of their indebtedness or are co-borrowers. During 2023, we deconsolidated one Real Estate Entity after the third-party lenders released our guarantees of associated mortgage loans. As of December 31, 2025, we provided guarantees to the indebtedness of two Real Estate Entities.
Revenue and operating expenses of consolidated Real Estate Entities are not significant since the extent of these entities’ operations is to own facilities leased to our hospital division entities which are financed by a combination of contributed equity by related parties and third-party mortgage indebtedness. Such leases are typically on a triple net basis where our hospital division is responsible for all operating costs, repairs and taxes on the facilities. Finance lease income is
45
recognized outside of segment operating income as other income by the Real Estate Entities. However, these amounts are largely eliminated in the consolidation of these entities into our financial statements.
On May 2, 2025, the Company acquired a 51% membership interest in an Indiana-based limited liability company (“May 2025 Acquiree”) for $2.3 million in cash. Due to the assumption of the note payable, interest expense was $0.2 million for the year ended December 31, 2025.
On December 17, 2025, the Company acquired land and an office building, together with related contractual rights, including existing tenant lease agreements and certain service contracts pursuant to an asset purchase agreement, for $2.2 million in cash. The Company recognized rental income of $0.1 million, which is included in the hospital division revenue line item in the consolidated statements of operations, and $0.2 million in operating expenses for the year ended December 31, 2025.
Corporate and other costs. Corporate and other costs in 2025 included general and administrative expenses totaling $51.7 million and stock-based compensation of $117.0 million. Our stock-based compensation expense in the form of one-time obligations paid in common stock to qualifying under construction and ramping hospitals increased by $100.4 million. Our corporate costs for 2024 included general and administrative costs of $41.9 million, a non-cash impairment charge of $7.1 million and stock-based compensation of $16.6 million. General and administrative costs increased $9.7 million attributed to increases in accrued bonus expense and payroll of $4.5 million, audit and audit-related fees associated with the restatement of our 2024 financial statements of $2.3 million, recruiting fees of $1.4 million, and other professional and IT expenses of $1.4 million.
Nonoperating items
Interest expense. Interest expense totaled $22.2 million in 2025 as compared with $19.9 million for 2024. The increase in interest expense is primarily due to leases entered into throughout 2024 that are fully operating in 2025, and due to leases entered into in 2025 for the opening of two facilities throughout the year.
Income tax expense. As of December 31, 2025 the Company fully utilized its federal and state net operating losses. As of December 31, 2025 and 2024, the Company had a capital loss carryforward of $0.2 million and $4.5 million, respectively. Due to the uncertainty about the Company's ability to utilize the capital loss prior to the expiration date, the Company maintained a valuation allowance against that deferred tax asset as of December 31, 2024. The expired capital loss was written off and the corresponding valuation allowance was reversed as of December 31, 2025.
Year Ended December 31, 2024 Compared to Year Ended December 31, 2023
We reported a net income attributable to Nutex Health Inc. of $52.1 million, or earnings of $9.69 per share, for 2024 as compared with a net loss attributable to Nutex Health Inc. of $45.8 million, or a loss of $10.39 per share, for 2023. Our 2024 results were principally affected by:
•Revenue growth of approximately $169.7 million was primarily driven by successful participation in arbitration through the IDR process under the No Surprises Act ("NSA").
•Increased revenue was also attributed to higher utilization of more complex clinical services, including increased observation and in-patient stays.
•Patient visits rose by 16.9% for the year ended December 31, 2024, compared to the same period in 2023. Mature hospitals experienced an average visit growth of 6.5% year-over-year, alongside the impact of four new hospital openings in 2024.
•Our operating expenses increased primarily due the revenue generated from the IDR process in addition to the opening of new facilities and volume growth.
Adjusted EBITDA for 2024 was $102.8 million as compared to $(5.8) million for 2023. Refer to Non-GAAP Financial Measures discussed below for a definition and reconciliation of Adjusted EBITDA.
A discussion of our segment results is included below.
Hospital Division. Our revenue for 2024 totaled $449.1 million as compared to $218.1 million for 2023, an increase of 106% caused by successful participation in arbitration through the IDR process under the NSA and by an increase in the
46
number of patient visits associated with higher utilization of premium services. The following table shows the number of patient visits during the periods:
| Year ended December 31, | |||||||||||
| 2024 | 2023 | ||||||||||
| Patient visits: | |||||||||||
| Hospital | 168,388 | 144,058 | |||||||||
Total revenue increased $231.0 million in 2024 from 2023 primarily due to successful participation in arbitration through the IDR process, contributing $169.7 million to the increase, and by an increase in the number of patient visits and the number of visits associated with higher utilization of more complex clinical services.
Effective May 1, 2024, we engaged with a third-party IDR vendor to further support our out of network claims appeals and determine which claims would be beneficial to arbitrate. The IDR process can take up to three to five months to receive payments relative to the start of a claim’s open negotiation process. In order to facilitate the dispute arbitration process, the Company incurred fees to the Centers for Medicare and Medicaid Services (“CMS”), the organizations that arbitrate the payment amount between the plan and providers (“IDRE”), and commission and fees to the third-party IDR vendor. Total accrued arbitration expenses are $47.7 million as of December 31, 2024.
For these reasons, we refined our estimates of variable consideration and revenue recognition timing, particularly to claims subject to arbitration. Our methodology now incorporates historical arbitration outcomes, payment history, and expected resolution timing in determining the expected transaction price for applicable claims. The result of this change in estimate increased our estimate of the ultimate amounts of accounts receivable we will collect for the current and prior periods. This change in estimate increased revenue and net income before tax for the year ended December 31, 2024 by approximately $169.7 million and $112.0 million, respectively.
The hospital division’s operating income was $195.5 million during 2024, up 438.1% as compared $36.3 million in the same period of 2023. Our operating income for 2024 was positively affected by an increase in net revenue as noted above. Our contract services expense increased $57.6 million due to the cost associated with the IDR process. Our payroll expense increased due to the opening of four facilities in 2024 as well as due to the accrual of bonus payable in 2025. Our operating income was adversely impacted by $8.4 million from the opening of four new hospital locations in 2024. Start-up and operating expenses at new facilities often exceed our revenue at these facilities until they achieve stabilized volumes of patient visits.
Population Health Management Division. We completed our reverse business combination with Clinigence in April 2022. Legacy Clinigence’s operations are reported as the population health management division. Our total revenue for 2024 for this division was $30.9 million consisting of capitation revenue of $27.8 million, management fees of $2.1 million and SaaS revenue of $1.0 million. The increase in revenue is attributed to increases in capitation revenue in 2024. Capitation revenue is recognized by our consolidated VIE, Atlas. We do not have an equity interest in this VIE but consolidate it since we are the primary beneficiary of its operations under our management services contract with them. We also earn management fees under our management services contracts with other IPAs and MSOs which are reported as revenue.
The population health management division had $1.4 million of operating income for 2024 driven by our divestiture of Procare and Clinigence Health Inc. entities. These two entities were negatively impacting the population health management division’s operating performance. This strategic move contributed to improved gross margins from 2024 onward, reinforcing the organization's long-term profitability.
Real Estate Division. This division reports the operations of consolidated Real Estate Entities where we provide guarantees of their indebtedness or are co-borrowers. During 2023, we deconsolidated one Real Estate Entity after the third-party lenders released our guarantees of associated mortgage loans. As of December 31, 2024, we provided guarantees to the indebtedness of two Real Estate Entities.
Revenue and operating expenses of consolidated Real Estate Entities are not significant since the extent of these entities’ operations is to own facilities leased to our hospital division entities which are financed by a combination of contributed equity by related parties and third-party mortgage indebtedness. Such leases are typically on a triple net basis where our hospital division is responsible for all operating costs, repairs and taxes on the facilities. Finance lease income is
47
recognized outside of segment operating income as other income by the Real Estate Entities. However, these amounts are largely eliminated in the consolidation of these entities into our financial statements.
Corporate and other costs. Corporate and other costs in 2024 included general and administrative expenses totaling $41.9 million, impairment losses of assets and goodwill of $7.1 million due to facility closures and stock-based compensation of $16.6 million. Our corporate costs for included general and administrative costs of $33.2 million, a non-cash impairment charge of $30.2 million and stock-based compensation of $2.8 million. General and administrative costs increased $8.6 million attributed to increases in accrued bonus expense ($2.7 million), professional services ($2.3 million), insurance expense ($2.3 million) and in other ($1.3 million).
Nonoperating items
Interest expense. Interest expense totaled $19.9 million in 2024 as compared with $16.3 million for 2023. The increase in interest expense is primarily due to leases entered into in 2024 for the opening of four facilities throughout the year.
Income tax expense.
As of December 31, 2023, a valuation allowance was established against the net deferred tax asset because the Company determined it was more likely than not that future earnings will not be sufficient to realize the corresponding tax benefits. In determining the appropriate valuation allowance, the Company considered the projected realization of tax benefits based on expected levels of future taxable income, available tax planning strategies and reversals of existing taxable temporary differences.
As of December 31, 2024, we recorded a non-cash benefit of $6.5 million to income tax expense to remove the majority of the valuation allowance after we concluded that the associated deferred tax assets would be realizable. In determining the appropriate valuation allowance, the Company considered its net cumulative earnings (adjusted for permanent items) for the last three years, along with the change to its business related to the higher revenue estimates without impacting its existing cost structure. $1.0 million valuation allowance remains to offset the deferred tax asset related to capital loss carryforwards that the company does not expect to realize.
Each of the discrete items above, as well as the non-deductible goodwill impairment expense recognized in 2024 and 2023 are one-time, non-cash items.
Liquidity and Capital Resources
As of December 31, 2025, we had $185.6 million of cash and equivalents, compared to $40.6 million of cash and equivalents at December 31, 2024.
Significant sources and uses of cash during 2025.
Sources of cash:
•Cash from operating activities was $248.1 million.
•Cash related to restricted short-term investment was $1.6 million.
•Cash capital contributions by noncontrolling members of $0.8 million.
•Proceeds from borrowings under lines of credit were $5.0 million.
Uses of cash:
•Acquisitions of property and equipment were $2.5 million.
•We made distributions to noncontrolling interest owners totaling $74.3 million.
•Net repayment of notes payable totaled $11.4 million.
•Cash related to stock repurchases and retirements was $5.0 million.
•Repayments of lines of credit totaled $7.9 million.
•Payments for asset acquisitions of $4.3 million.
•Repayments of finance leases totaled $5.2 million.
48
Future sources and uses of cash. Our operating activities are financed with cash on hand which is generated from revenues. Most of our hospital facilities are leased from various lessors including related parties. These leases are presented in our consolidated balance sheets unless the lease is from a consolidated Real Estate Entity. Our growth plans include the development of new hospital locations. We expect that in many of these locations we will lease facilities from newly established entities partially owned by related parties.
We routinely enter into equipment lease agreements to procure new or replacement equipment and may also finance these purchases with term debt. We have smaller lines of credits available for working capital purposes and are presently working to supplement or replace these with larger financing commitments. These larger financing commitments are subject to market conditions and we may not be able to obtain such larger financing commitments at favorable economic terms or at all.
Indebtedness. The Company’s indebtedness at December 31, 2025 is presented in Note 8 – Debt and our lease obligations are presented in Note 9 – Leases.
We have entered into private debt arrangements with banking institutions for the purchase of equipment and to provide working capital and liquidity through cash and lines of credit. Unless otherwise delineated above, these debt arrangements are obligations of Nutex and/or its wholly-owned subsidiaries. Consolidated Real Estate Entities have entered into private debt arrangements with banking institutions for purposes of purchasing land, constructing new emergency room facilities and building out leasehold improvements which are leased to our hospital entities. Nutex is a guarantor or, in limited cases, a co-borrower on the debt arrangements of the Real Estate Entities for the periods shown.
Certain outstanding debt arrangements require minimum debt service coverage ratios and other financial covenants. At December 31, 2025, we were in compliance with these debt arrangements; we had remaining availability of an aggregate of $5.3 million under outstanding lines of credit.
Pre-Paid Advance Agreement with Yorkville. On February 15, 2024, the parties terminated the Pre-Paid Advance Agreement (the “PPA”) dated April 11, 2023 between the Company and YA II PN, Ltd. (“Yorkville”) pursuant to which the Company requested an advance of $15.0 million from Yorkville a “Pre-Paid Advance”) purchased by Yorkville at 90% of the face amount. Interest accrued on the outstanding balance of the Pre-Paid Advance at an annual rate equal to 0% subject to an increase to 15% upon events of default described in the PPA. The Pre-Paid Advance had a maturity date of 12 months from the Pre-Paid Advance Date. As a result of the Pre-Paid Advance, the Company (i) issued, on April 11, 2023, 0.2 million shares of common stock to Yorkville (23.1 million prior to the 2024 Reverse Stock Splits), reducing the principal of initial Pre-Paid Advance to $7.3 million, (ii) made Optional Prepayments of $8.2 million in accordance with the PPA, consisting of $7.7 million of principal and $1.0 million attributed to the Payment Premium offset by $0.5 million in debt discount amortization, and (iii) paid off in full the remaining outstanding balance of the PPA on January 30, 2024.
Unsecured Convertible Term Notes and Warrants with Accredited Investors. From September 2023 to December 2023, the Company conducted a private offering of convertible notes (“Unsecured Convertible Term Notes”) and six-year warrants (“Warrants”) to accredited investors (the “Holders”) as defined in Rule 501 under the 1933 Act and issued Unsecured Convertible Term Notes convertible into an aggregate of 89,751 shares (13,462,500 prior to the 2024 Reverse Stock Splits) of common stock at a conversion price of $60.00 per share ($0.40 prior to the 2024 Reverse Stock Splits) and Warrants to purchase an aggregate of 44,875 shares of common stock (6,731,250 prior to the 2024 Reverse Stock Splits) at an exercise price of $60.00 per share ($0.40 prior to the 2024 Reverse Stock Splits). We also issued Warrants for the purchase of 26,925 shares (4,038,750 prior to the 2024 Reverse Stock Splits) to the placement agent. On March 26, 2024, the Company and the Holders agreed to amend the conversion price of the Unsecured Convertible Term Notes and exercise price of the Warrants to $30.00 each ($0.20 prior to the 2024 Reverse Stock Splits), resulting in the Unsecured Convertible Term Notes being convertible into 179,500 shares of common stock (26,925,000 prior to the 2024 Reverse Stock Splits), the Warrants exercisable for 89,750 shares of common stock (13,462,500 prior to the 2024 Reverse Stock Splits) and the placement agent Warrants exercisable for 53,850 shares of common stock (8,077,500 prior to the 2024 Reverse Stock Splits). The Unsecured Convertible Term Notes matured on October 31, 2025 and the Warrants expire on December 31, 2029.
As of October 31, 2025, the remaining note holders of unsecured convertible term notes converted $4.9 million of principal and $0.1 million of interest to 165,030 shares of the Company's common stock, valued at $30.00 per share.
The Company appointed Emerson Equity LLC as placement agent for the September 2023 Private Offering. Per the Placement Agent Agreement, the Company agrees to pay (i) a cash commission equal to 10% of the gross proceeds and (ii)
49
warrants to purchase a number of Common Stock equal to 20% of the total number of shares issuable upon conversion or exercise of the Unsecured Convertible Term Notes and Warrants, as applicable.
On December 16, 2025, the Company entered into an amendment of the terms of the September 2023 Private Offering. The amendment permits the Holder to exercise the Warrant on a cashless basis in the event that there is no effective registration statement available for the resale of the underlying securities. The amendment did not change the exercise price of the Warrant, which remains $30.00 per share, nor did it modify the number of Warrants issued. On December 16, 2025, pursuant to the amended terms, a Holder completed a cashless exercise of a Warrant and the Company issued 40,387 shares of its common stock.
Off-Balance Sheet Arrangements
As of December 31, 2025, we had no material off-balance sheet arrangements.
Non-GAAP Financial Measures
Adjusted EBITDA. Adjusted EBITDA is used as a supplemental non-GAAP financial measure by management and external users of our financial statements, such as industry analysts, investors, lenders and rating agencies. We believe Adjusted EBITDA is useful because it allows us to more effectively evaluate our operating performance.
We define Adjusted EBITDA as net income (loss) attributable to Nutex Health Inc. plus net interest expense, income taxes, depreciation and amortization, further adjusted for stock-based compensation, certain defined items of expense, and any acquisition-related costs and impairments. Interest expense includes interest on lease liabilities, which is a component of total finance lease cost. A reconciliation of net income to Adjusted EBITDA is included below. Adjusted EBITDA is not intended to serve as an alternative to U.S. GAAP measures of performance and may not be comparable to similarly-titled measures presented by other companies.
Beginning if the first quarter of 2025, we have updated our presentation of Adjusted EBITDA to separately disclose finance lease payments related to leases under ASC 842. We believe this change provides greater transparency into our operating performance. The prior periods presented are adjusted to reflect this change in presentation. Adjusted EBITDA follows (in thousands):
| Year Ended December 31, | |||||||||||||||||
| 2025 | 2024 | 2023 | |||||||||||||||
| Reconciliation of net income (loss) attributable to Nutex Health Inc. to Adjusted EBITDA: | |||||||||||||||||
| Net income (loss) attributable to Nutex Health Inc. | $ | 70,789 | $ | 52,097 | $ | (45,786) | |||||||||||
| Depreciation and amortization | 20,530 | 18,972 | 17,592 | ||||||||||||||
| Interest expense, net | 22,226 | 19,932 | 16,318 | ||||||||||||||
| Income tax expense (benefit) | 64,424 | 15,020 | (5,067) | ||||||||||||||
| Allocation to noncontrolling interests | (9,385) | (7,176) | (5,546) | ||||||||||||||
| EBITDA | 168,584 | 98,845 | (22,489) | ||||||||||||||
| Facility closing costs | — | — | 217 | ||||||||||||||
| Acquisition costs | — | — | 43 | ||||||||||||||
| Loss on warrant liability | — | 1,609 | — | ||||||||||||||
| Stock-based compensation | 117,003 | 16,555 | 2,836 | ||||||||||||||
| Impairment of assets | — | 3,887 | 29,082 | ||||||||||||||
| Impairments of goodwill | — | 3,197 | 1,139 | ||||||||||||||
Finance lease payments(1) | (26,022) | (21,319) | (16,658) | ||||||||||||||
| Adjusted EBITDA | 259,565 | 102,774 | (5,830) | ||||||||||||||
50
| Three months ended December 31, 2025 | Three months ended December 31, 2024 | ||||||||||
| Unaudited | Unaudited | ||||||||||
| Reconciliation of net income (loss) attributable to Nutex Health Inc. to Adjusted EBITDA: | |||||||||||
| Net income (loss) attributable to Nutex Health Inc. | $ | 11,834 | $ | 61,612 | |||||||
| Depreciation and amortization | 5,187 | 5,280 | |||||||||
| Interest expense, net | 4,976 | 5,052 | |||||||||
| Income tax expense | 9,286 | 9,152 | |||||||||
| Allocation to noncontrolling interests | (5,570) | (2,195) | |||||||||
| EBITDA | 25,713 | 78,901 | |||||||||
| Loss on warrant liability | — | 536 | |||||||||
| Stock-based compensation | (2,603) | 14,603 | |||||||||
| Impairment of assets | — | (11) | |||||||||
Finance lease payments(1) | (6,510) | (7,363) | |||||||||
| Adjusted EBITDA | $ | 16,600 | $ | 86,666 | |||||||
1.Finance lease payments consist of cash payments for financing leases under ASC842, which should be deducted from EBITDA. We believe this change is useful to investors to evaluate the ongoing operating performance of our business.
Significant Accounting Policies
Revenue recognition.
Hospital division – Our hospital division recognizes patient service revenue for contracts with patients, and in most cases, patients with out of network benefits with a third-party payor, such as, commercial insurance, workers compensation insurance or, in limited cases, Medicare/Medicaid. The Company’s performance obligations are to provide emergency health care services primarily on an outpatient basis. Patient service revenues are recorded at the amount that reflects the consideration that the Company expects to be paid for providing patient care. These amounts are net of appropriate discounts giving recognition to differences between the Company’s charges and reimbursement rates from third party payors.
Hospital revenues earned by the Company are recognized at a point in time when the services are provided to patients, net of adjustments and discounts. Because all the Company’s performance obligations relate to contracts with patients with a duration of less than one-year, certain disclosures are limited.
We are considered “out-of-network” with commercial health plans. As there are no contractual rates established with insurance entities, revenues are estimated based on the “usual and customary” charges allowed by insurance payors using historical collection experience, historical trends of refunds and payor payment adjustments (retractions). Revenue from the Medicare program is based on reimbursement rates set by governmental authorities. For insured patients, the transaction price is determined based on gross charges for services provided, reduced by adjustments provided to third-party payors, discounts and implicit price concessions provided primarily to uninsured patients in accordance with the Company’s policy. For uninsured patients, the Company recognizes revenue based on established rates, subject to certain discounts and implicit price concessions. The Company is reimbursed from third party payors under various methodologies based on the level of care provided.
Patients who have health care insurance may also have discounts applied related to their copayment or deductible. Estimates of contractual adjustments and discounts are determined by major payor classes for outpatient revenues based on historical experience. The Company estimates implicit price concessions based on its historical collection experience with these classes of patients using a portfolio approach. The portfolios consist of major payor classes for outpatient revenue. Based on historical collection trends and other analyses, the Company concluded that revenue for a given portfolio would not be materially different than if accounting for revenue on a contract-by-contract basis.
51
Customer payments are due upon receipt of an explanation of benefits for insured patients or it is due upon receipt of the bill from the Company for uninsured payments. There is no financing component associated with payments due from insurers or patients.
Population health management division – The population health management division recognizes revenue for capitation and management fees for services to IPAs and physician groups and for the licensing, training, and consulting related to our cloud-based proprietary technology on a monthly basis.
Capitation revenue consists primarily of capitated fees for medical services provided by physician-owned entities we consolidate as VIEs. Capitated arrangements are made directly with various managed care providers including HMOs. Capitation revenues are typically paid to us monthly in the period services are provided based on the number of enrollees selecting us as their healthcare provider. Capitation is a fixed payment amount per patient per unit of time paid in advance for the delivery of health care services, whereby the service providers are generally liable for excess medical costs.
We receive management fees that are based on gross capitation revenues of the IPAs or physician groups we manage. Revenue is recognized and received monthly for our services. In addition, we provide consultant services that are charged as a flat fixed rate and recognized as revenue when the service is performed. Consultant services revenues represent a small portion of our total revenue.
Construction in Progress. The Company regularly is in the process of constructing new facilities. Generally, our hospital facilities are responsible for the leasehold build out and equipment while the associated Real Estate Entity procures the land, if any, and constructs a new or remodeled facility. Costs incurred to construct assets which will ultimately be classified as fixed assets are capitalized and classified in our financial statements as construction in progress until construction is completed and the asset is available for use. Once the asset is available for use, it is reclassified as another category of fixed assets and depreciated across its useful life.
Goodwill Impairment. We test goodwill for impairment at least annually by first performing a qualitative assessment to determine whether a quantitative goodwill test is necessary or by electing to forgo the qualitative assessment and perform the quantitative goodwill test. For the year ended December 31, 2025, the Company elected to perform a qualitative assessment of goodwill. Upon performing the qualitative assessment of goodwill, qualitative factors are assessed to determine whether it is more likely than not that the fair value is less than the carrying amount. For the years ended December 31, 2024 and 2023, we elected to perform a quantitative goodwill test which compares the estimated fair values of our reporting units to their respective carrying values. For the quantitative test, we use the income method to estimate the fair value of these assets, which is based on forecasts of the expected future cash flows attributable to the respective assets. Significant estimates and assumptions inherent in the valuations reflect a consideration of other marketplace participants, and include the amount and timing of future cash flows (including expected growth rates and profitability). Estimates utilized in the projected cash flows include consideration of macroeconomic conditions, overall category growth rates, competitive activities, Company business plans and the discount rate applied to the cash flows. Unanticipated market or macroeconomic events and circumstances may occur, which could affect the accuracy or validity of the estimates and assumptions.
Based on the results of the annual qualitative assessment of goodwill for the year ended December 31, 2025, we concluded it is not more likely than not that the fair value of the Population Health Management Division is less than the carrying amount and therefore, did not perform a quantitative goodwill test or record impairment.
On June 30, 2024, the impairment of goodwill of $3.2 million and the derecognition of goodwill of $0.5 million, both for the Population Health Management Division, relate to the sale of Procare Health, Inc., a wholly-owned subsidiary of Nutex. Procare was considered part of the Population Health Management Division. Prior to the sale of Procare, the Company recognized a goodwill impairment amount of $3.2 million. On the sale of Procare, the Company recognized the derecognition of goodwill of $0.5 million based on the remaining carrying amount of goodwill for the Procare business after impairment.
Due to the sale of Procare, the Company tested for impairment the remaining goodwill in the Population Health Management Division of $13.9 million. On June 30, 2024, we determined that the fair value of our Population Health Management Division was greater than its carrying value. Therefore, no goodwill impairment was recognized for the quarter ended June 30, 2024. No goodwill impairment was recognized for years ended December 31, 2025 and December 31, 2024.
52
On December 31, 2023, we recognized an impairment loss of $1.1 million in a reporting unit within our Hospital Division for the closure of a facility in January 2024.
We believe the estimates and assumptions utilized in our impairment testing are reasonable and are comparable to those that would be used by other marketplace participants. However, actual events and results could differ substantially from those used in our valuations. To the extent such factors result in a failure to achieve the level of projected cash flows used to estimate fair value for purposes of establishing or subsequently impairing the carrying amount of goodwill and intangible assets, we may need to record additional non-cash impairment charges in the future.
Selected Quarterly Financial Data
During 2025, the Company determined that its previously issued consolidated financial statements for the year ended December 31, 2024 required restatement. The restatement primarily related to the reclassification of non-cash stock-based compensation obligations associated with under-construction and ramping hospitals from equity to liabilities, based on the applicable classification criteria under ASC 718, Compensation—Stock Compensation, and ASC 480, Distinguishing Liabilities from Equity. In addition, the Company recorded certain immaterial adjustments, including the reclassification of related-party balances intended as capital contributions, the reclassification of restricted balances out of cash and cash equivalents, adjustments to income tax expense and related disclosures, and certain presentation refinements. As a result of these changes, the Company’s previously reported quarterly results for fiscal years 2024 and 2025 have been revised, including income (loss) and earnings per share, as reflected in the summarized quarterly financial information presented below:
| For the quarters ended | |||||||||||||||||||||||
| (In thousands, except per share amounts) | December 31, 2025 | September 30, 2025 | June 30, 2025 | March 31, 2025 | |||||||||||||||||||
| Total revenue | $ | 151,679 | $ | 267,804 | $ | 243,985 | $ | 211,789 | |||||||||||||||
| Total operating costs and expenses | 105,541 | 112,923 | 119,061 | 93,451 | |||||||||||||||||||
| Gross profit | 46,138 | 154,881 | 124,924 | 118,338 | |||||||||||||||||||
| Total corporate and other costs | 15,220 | 24,514 | 91,245 | 37,677 | |||||||||||||||||||
| Operating income (loss) | 30,918 | 130,367 | 33,679 | 80,661 | |||||||||||||||||||
| Income (loss) before taxes | 25,894 | 123,939 | 23,732 | 71,216 | |||||||||||||||||||
| Income tax expense (benefit) | 9,286 | 27,140 | 7,588 | 20,410 | |||||||||||||||||||
| Net income (loss) | 16,608 | 96,799 | 16,144 | 50,806 | |||||||||||||||||||
| Less: net income attributable to noncontrolling interests | 4,774 | 41,364 | 33,841 | 29,589 | |||||||||||||||||||
| Net income (loss) attributable to Nutex Health Inc. | 11,834 | 55,435 | (17,697) | 21,217 | |||||||||||||||||||
| Earnings (loss) per common share | |||||||||||||||||||||||
| Basic | 1.68 | 8.27 | (2.95) | 3.74 | |||||||||||||||||||
| Diluted | 1.62 | 7.76 | (2.95) | 3.33 | |||||||||||||||||||
53
| For the quarters ended | |||||||||||||||||||||||
| (In thousands, except per share amounts) | December 31, 2024 | September 30, 2024 | June 30, 2024 | March 31, 2024 | |||||||||||||||||||
| Total revenue | $ | 257,619 | $ | 78,795 | $ | 76,082 | $ | 67,453 | |||||||||||||||
| Total operating costs and expenses | 115,992 | 56,878 | 53,521 | 57,296 | |||||||||||||||||||
| Gross profit | 141,626 | 21,917 | 22,561 | 10,157 | |||||||||||||||||||
| Total corporate and other costs | 27,340 | 12,254 | 17,262 | 8,707 | |||||||||||||||||||
| Operating income (loss) | 114,286 | 9,663 | 5,299 | 1,450 | |||||||||||||||||||
| Income (loss) before taxes | 108,654 | (2,580) | 3,904 | (152) | |||||||||||||||||||
| Income tax expense (benefit) | 9,151 | 4,585 | 894 | 390 | |||||||||||||||||||
| Net income (loss) | 99,503 | (7,165) | 3,010 | (542) | |||||||||||||||||||
| Less: net income attributable to noncontrolling interests | 37,890 | 1,623 | 3,374 | (178) | |||||||||||||||||||
| Net income (loss) attributable to Nutex Health Inc. | 61,613 | (8,788) | (364) | (364) | |||||||||||||||||||
| Earnings (loss) per common share | |||||||||||||||||||||||
| Basic | 11.33 | (1.72) | (0.07) | (0.08) | |||||||||||||||||||
| Diluted | 9.88 | (1.72) | (0.07) | (0.08) | |||||||||||||||||||
Item 7A. Quantitative and Qualitative Disclosure About Market Risk
We are exposed to market risk related to changes in interest rates, primarily as a result of the line of credit facilities which bear interest based on floating rates.
To mitigate the impact of fluctuations in interest rates on our long-term debt, we generally target our debt portfolio to be maintained at fixed rates.
54
Item 8. Financial Statements and Supplementary Data
INDEX TO CONSOLIDATED FINANCIAL STATEMENTS
Reports of Independent Registered Public Accounting Firm (PCAOB ID Number | |||||
55
REPORT OF INDEPENDENT REGISTERED PUBLIC ACCOUNTING FIRM
Board of Directors and Shareholders
Nutex Health Inc.
Opinion on the financial statements
We have audited the accompanying consolidated balance sheets of Nutex Health Inc. (a Delaware corporation) and subsidiaries (the “Company”) as of December 31, 2025 and 2024, the related consolidated statements of operations, changes in equity, and cash flows for each of the two years in the period ended December 31, 2025, and the related notes (collectively referred to as the “consolidated financial statements”). In our opinion, the consolidated financial statements present fairly, in all material respects, the financial position of the Company as of December 31, 2025 and 2024, and the results of its operations and its cash flows for each of the two years in the period ended December 31, 2025, in conformity with accounting principles generally accepted in the United States of America.
We also have audited, in accordance with the standards of the Public Company Accounting Oversight Board (United States) (“PCAOB”), the Company’s internal control over financial reporting as of December 31, 2025, based on criteria established in the 2013 Internal Control—Integrated Framework issued by the Committee of Sponsoring Organizations of the Treadway Commission (“COSO”), and our report dated March 5, 2026 expressed an unqualified opinion.
Basis for opinion
These consolidated financial statements are the responsibility of the Company’s management. Our responsibility is to express an opinion on the Company’s consolidated financial statements based on our audits. We are a public accounting firm registered with the PCAOB and are required to be independent with respect to the Company in accordance with the U.S. federal securities laws and the applicable rules and regulations of the Securities and Exchange Commission and the PCAOB.
We conducted our audits in accordance with the standards of the PCAOB. Those standards require that we plan and perform the audit to obtain reasonable assurance about whether the financial statements are free of material misstatement, whether due to error or fraud. Our audits included performing procedures to assess the risks of material misstatement of the financial statements, whether due to error or fraud, and performing procedures that respond to those risks. Such procedures included examining, on a test basis, evidence regarding the amounts and disclosures in the financial statements. Our audit also included evaluating the accounting principles used and significant estimates made by management, as well as evaluating the overall presentation of the financial statements. We believe that our audits provide a reasonable basis for our opinion.
Critical audit matter
The critical audit matter communicated below is a matter arising from the current period audit of the financial statements that was communicated or required to be communicated to the audit committee and that: (1) relates to accounts or disclosures that are material to the financial statements and (2) involved our especially challenging, subjective, or complex judgements. The communication of critical audit matters does not alter in any way our opinion on the financial statements, taken as a whole, and we are not, by communicating the critical audit matter below, providing a separate opinion on the critical audit matter or on the accounts or disclosures to which it relates.
Estimate of variable consideration, including contractual allowances and estimate of claims subject to arbitration
As described further in notes 2 and 4 to the financial statements, revenues and related accounts receivable are recognized at a point in time when the services are provided to patients, net of adjustments and discounts. Patient service revenues are recorded at the amount that reflects the consideration the Company expects to be paid for providing patient care.
Estimating the amount of variable consideration can require significant judgement in developing the appropriate portfolio of data and can be subject to change based on continuous reevaluation of historical outcomes. We identified the estimate of variable consideration, including contractual allowances and estimate of claims subject to arbitration, as a critical audit matter.
56
The principal consideration for our determination that the estimate of variable consideration, including contractual allowances and estimate of claims subject to arbitration, is a critical audit matter is that the estimate requires a high degree of auditor subjectivity in evaluating management’s assumptions related to developing future collection patterns across the various outpatient locations and payor behavior.
Our audit procedures related to the Company’s estimate of variable consideration, including contractual allowances and estimate of claims subject to arbitration, included the following, among others.
•We evaluated the appropriateness of the overall methodology used by management to develop the estimates, including considering whether the methodology maximized the use of observable outputs.
•We tested the design and operating effectiveness of controls relating to billing and cash collections of patient service revenue and accounts receivable, including arbitration win amounts, that are used to develop the variable consideration estimates.
•For a sample of patient visits, we inspected and compared underlying documents for each transaction, which included gross billing charges and cash collected (net revenue).
•For a sample of patient visits, we traced gross billings and net revenue to each report used in determining and assessing the contractual adjustment calculation and if applicable, the arbitration estimate. We recalculated the contractual adjustment and arbitration estimate for a sample of patient visits to ensure they were consistent with the Company’s policy and traced the adjustment ratio for each payor to the Company's calculation based on historical collection experience.
•We compared cash collections to recorded net revenue for each quarter of 2025 and for the year ended December 31, 2025.
•We performed a lookback analysis to the December 31, 2024 accounts receivable by comparing collections made during the year ended December 31, 2025 to assess the reasonableness of management’s estimation process.
/s/ GRANT THORNTON LLP
We have served as the Company’s auditor since 2025.
March 5, 2026
57
Report of Independent Registered Public Accounting Firm
To the Shareholders and Board of Directors of
Nutex Health Inc.
Opinion on the Financial Statements
We have audited the accompanying consolidated balance sheet of Nutex Health Inc. (the “Company”) as of December 31, 2023, the related consolidated statements of operations, changes in equity and cash flows for the year ended December 31, 2023, and the related notes (collectively referred to as the “financial statements”). In our opinion, based on our audit, the financial statements present fairly, in all material respects, the financial position of the Company as of December 31, 2023, and the results of its operations and its cash flows for the year ended December 31, 2023, in conformity with accounting principles generally accepted in the United States of America.
Basis for Opinion
These financial statements are the responsibility of the Company's management. Our responsibility is to express an opinion on the Company's financial statements based on our audit. We are a public accounting firm registered with the Public Company Accounting Oversight Board (United States) ("PCAOB") and are required to be independent with respect to the Company in accordance with the U.S. federal securities laws and the applicable rules and regulations of the Securities and Exchange Commission and the PCAOB.
We conducted our audit in accordance with the standards of the PCAOB. Those standards require that we plan and perform the audit to obtain reasonable assurance about whether the financial statements are free of material misstatement, whether due to error or fraud. The Company is not required to have, nor were we engaged to perform, an audit of its internal control over financial reporting. As part of our audit we are required to obtain an understanding of internal control over financial reporting but not for the purpose of expressing an opinion on the effectiveness of the Company's internal control over financial reporting. Accordingly, we express no such opinion.
Our audit included performing procedures to assess the risks of material misstatement of the financial statements, whether due to error or fraud, and performing procedures that respond to those risks. Such procedures included examining, on a test basis, evidence regarding the amounts and disclosures in the financial statements. Our audit also included evaluating the accounting principles used and significant estimates made by management, as well as evaluating the overall presentation of the financial statements. We believe that our audit provides a reasonable basis for our opinion.
/s/ Marcum LLP
Marcum LLP
We served as the Company’s auditor from 2021 to 2025.
March 28, 2024
58
NUTEX HEALTH INC.
CONSOLIDATED BALANCE SHEETS
| December 31 | ||||||||||||||
| (In thousands, except share and per share amounts) | 2025 | 2024 | ||||||||||||
| Assets | ||||||||||||||
| Current assets: | ||||||||||||||
| Cash and cash equivalents | $ | $ | ||||||||||||
| Restricted cash | ||||||||||||||
| Restricted short-term investments | ||||||||||||||
| Accounts receivable | ||||||||||||||
| Accounts receivable - related parties | ||||||||||||||
| Inventories | ||||||||||||||
| Prepaid expenses and other current assets | ||||||||||||||
| Total current assets | ||||||||||||||
Property and equipment, net (accumulated depreciation of | ||||||||||||||
| Operating lease right-of-use assets | ||||||||||||||
| Financing lease right-of-use assets | ||||||||||||||
| Intangible assets, net | ||||||||||||||
| Goodwill, net | ||||||||||||||
| Deferred tax assets | ||||||||||||||
| Other assets | ||||||||||||||
| Total assets | $ | $ | ||||||||||||
| Liabilities and Equity | ||||||||||||||
| Current liabilities: | ||||||||||||||
| Accounts payable | $ | $ | ||||||||||||
| Accounts payable - related parties | ||||||||||||||
| Lines of credit | ||||||||||||||
| Current portion of long-term debt | ||||||||||||||
| Operating lease liabilities, current portion | ||||||||||||||
| Financing lease liabilities, current portion | ||||||||||||||
| Accrued arbitration expenses | ||||||||||||||
| Accrued income tax expense | ||||||||||||||
| Accrued stock-based compensation | ||||||||||||||
| Accrued expenses and other current liabilities | ||||||||||||||
| Total current liabilities | ||||||||||||||
| Long-term debt, net | ||||||||||||||
| Non-current operating lease liabilities, net | ||||||||||||||
| Non-current financing lease liabilities, net | ||||||||||||||
| Deferred tax liabilities | ||||||||||||||
| Total liabilities | ||||||||||||||
| Commitments and contingencies (Note 10) | ||||||||||||||
| Equity: | ||||||||||||||
Common stock, $ | ||||||||||||||
| Additional paid-in capital | ||||||||||||||
| Accumulated deficit | ( | ( | ||||||||||||
| Nutex Health Inc. equity | ||||||||||||||
| Noncontrolling interests | ||||||||||||||
| Total equity | ||||||||||||||
| Total liabilities and equity | $ | $ | ||||||||||||
See accompanying notes to the consolidated financial statements.
59
NUTEX HEALTH INC.
CONSOLIDATED STATEMENTS OF OPERATIONS
| Year ended December 31, | ||||||||||||||||||||
| (In thousands, except per share amounts) | 2025 | 2024 | 2023 | |||||||||||||||||
| Revenue: | ||||||||||||||||||||
| Hospital division | $ | $ | $ | |||||||||||||||||
| Population health management division | ||||||||||||||||||||
| Total revenue | ||||||||||||||||||||
| Operating costs and expenses: | ||||||||||||||||||||
| Payroll | ||||||||||||||||||||
| Contract services | ||||||||||||||||||||
| Medical supplies | ||||||||||||||||||||
| Depreciation and amortization | ||||||||||||||||||||
| Other | ||||||||||||||||||||
| Total operating costs and expenses | ||||||||||||||||||||
| Gross profit | ||||||||||||||||||||
| Corporate and other costs: | ||||||||||||||||||||
| Facilities closing costs | ||||||||||||||||||||
| Acquisition costs | ||||||||||||||||||||
| Stock-based compensation | ||||||||||||||||||||
| Impairment of assets | ||||||||||||||||||||
| Impairment of goodwill | ||||||||||||||||||||
| General and administrative expenses | ||||||||||||||||||||
| Total corporate and other costs | ||||||||||||||||||||
| Operating income (loss) | ( | |||||||||||||||||||
| Interest expense, net | ||||||||||||||||||||
| Loss on warrant liability | ||||||||||||||||||||
| Other (income) expense | ( | |||||||||||||||||||
| Income (loss) before taxes | ( | |||||||||||||||||||
| Income tax expense (benefit) | ( | |||||||||||||||||||
| Net income (loss) | ( | |||||||||||||||||||
| Less: net income attributable to noncontrolling interests | ||||||||||||||||||||
| Net income (loss) attributable to Nutex Health Inc. | $ | $ | $ | ( | ||||||||||||||||
| Earnings (loss) per common share | ||||||||||||||||||||
| Basic | $ | $ | $ | ( | ||||||||||||||||
| Diluted | $ | $ | $ | ( | ||||||||||||||||
See accompanying notes to the consolidated financial statements.
60
NUTEX HEALTH INC.
CONSOLIDATED STATEMENTS OF CHANGES IN EQUITY
| Common Stock | Additional Paid-in Capital | Retained Earnings (Accumulated Deficit) | Noncontrolling Interests | Total Equity | |||||||||||||||||||||||||||||||
| (In thousands, except share data) | Shares | Amount | |||||||||||||||||||||||||||||||||
| Balance at January 1, 2023 | $ | $ | $ | ( | $ | $ | |||||||||||||||||||||||||||||
| Deconsolidation of Real Estate Entities | — | — | — | — | ( | ( | |||||||||||||||||||||||||||||
| Common stock issued for exercise of warrants | — | — | — | — | — | ||||||||||||||||||||||||||||||
| Common stock issued to Apollo Medical Holding Inc. | — | — | — | ||||||||||||||||||||||||||||||||
| Common stock issued for Employee Stock Purchase Plan | — | — | — | ||||||||||||||||||||||||||||||||
| Common stock issued for acquisition | — | — | — | ||||||||||||||||||||||||||||||||
| Debt conversion to common stock | — | — | |||||||||||||||||||||||||||||||||
| Stock-based compensation | — | — | — | ||||||||||||||||||||||||||||||||
| Warrants issued with convertible debt | — | — | — | — | |||||||||||||||||||||||||||||||
| Contributions | — | — | — | — | |||||||||||||||||||||||||||||||
| Distributions | — | — | — | — | ( | ( | |||||||||||||||||||||||||||||
| Net income (loss) | — | — | — | ( | ( | ||||||||||||||||||||||||||||||
| Balance at December 31, 2023 | $ | $ | $ | ( | $ | $ | |||||||||||||||||||||||||||||
| Common stock issuance for Securities Purchase Agreement | — | — | — | ||||||||||||||||||||||||||||||||
| Warrant exercises | — | — | |||||||||||||||||||||||||||||||||
| Common stock received in sale of business | ( | — | ( | — | — | ( | |||||||||||||||||||||||||||||
| Common stock issued for Employee Stock Purchase Plan | — | — | — | ||||||||||||||||||||||||||||||||
| Common stock issued for acquisition | — | — | — | ||||||||||||||||||||||||||||||||
| Debt conversion to common stock | — | — | — | ||||||||||||||||||||||||||||||||
| Vesting of Restricted Stock Units | — | — | — | — | — | ||||||||||||||||||||||||||||||
| Reverse stock split adjustment | — | — | — | — | — | ||||||||||||||||||||||||||||||
| Stock-based compensation | — | — | — | ||||||||||||||||||||||||||||||||
| Contributions | — | — | — | ||||||||||||||||||||||||||||||||
| Distributions | — | — | — | — | ( | ( | |||||||||||||||||||||||||||||
| Net income | — | — | — | ||||||||||||||||||||||||||||||||
| Balance at December 31,2024 | $ | $ | $ | ( | $ | $ | |||||||||||||||||||||||||||||
(Continued)
See accompanying notes to the consolidated financial statements.
61
NUTEX HEALTH INC.
CONSOLIDATED STATEMENTS OF CHANGES IN EQUITY
| Common Stock | Additional Paid-in Capital | Accumulated Deficit | Noncontrolling Interests | Total Equity | |||||||||||||||||||||||||||||||
| (In thousands, except share data) | Shares | Amount | |||||||||||||||||||||||||||||||||
| Balance at December 31, 2024 | $ | $ | $ | ( | $ | $ | |||||||||||||||||||||||||||||
| Warrant exercises | — | — | — | — | — | ||||||||||||||||||||||||||||||
| Common stock issued for Employee Stock Purchase Plan | — | — | — | ||||||||||||||||||||||||||||||||
| Common stock issued for acquisition | — | — | — | ||||||||||||||||||||||||||||||||
| Asset acquisition noncontrolling interest | — | — | — | — | |||||||||||||||||||||||||||||||
| Debt conversion to common stock | — | — | — | ||||||||||||||||||||||||||||||||
| Vesting of Restricted Stock Units | — | — | — | — | — | ||||||||||||||||||||||||||||||
| Stock-based compensation | — | — | |||||||||||||||||||||||||||||||||
| Stock repurchases and retirements | ( | — | ( | — | — | ( | |||||||||||||||||||||||||||||
| Contributions | — | — | — | ||||||||||||||||||||||||||||||||
| Distributions | — | — | — | — | ( | ( | |||||||||||||||||||||||||||||
| Net income | — | — | — | ||||||||||||||||||||||||||||||||
| Balance at December 31, 2025 | $ | $ | $ | ( | $ | $ | |||||||||||||||||||||||||||||
See accompanying notes to the consolidated financial statements.
62
NUTEX HEALTH INC.
CONSOLIDATED STATEMENTS OF CASH FLOWS
| Year Ended December 31, | ||||||||||||||||||||
| (In thousands) | 2025 | 2024 | 2023 | |||||||||||||||||
| Cash flows from operating activities: | ||||||||||||||||||||
| Net income (loss) | $ | $ | $ | ( | ||||||||||||||||
| Adjustment to reconcile net income (loss) to net cash from operating activities: | ||||||||||||||||||||
| Depreciation and amortization | ||||||||||||||||||||
| Impairment of assets | ||||||||||||||||||||
| Impairment of goodwill | ||||||||||||||||||||
| Derecognition of goodwill | ||||||||||||||||||||
| Loss on warrant liability | ||||||||||||||||||||
| Stock-based compensation expense | ||||||||||||||||||||
| Changes to deferred taxes | ( | ( | ||||||||||||||||||
| Debt accretion expense | ||||||||||||||||||||
| Loss on lease termination | ||||||||||||||||||||
| Changes in operating assets and liabilities: | ||||||||||||||||||||
| (Increase)/Decrease in Accounts receivable | ( | ( | ( | |||||||||||||||||
| (Increase)/Decrease in Accounts receivable - related party | ( | ( | ||||||||||||||||||
| (Increase)/Decrease in Inventories | ( | |||||||||||||||||||
| (Increase)/Decrease in Prepaid expenses and other current assets | ( | ( | ( | |||||||||||||||||
| (Increase)/Decrease in Operating right-of-use assets | ||||||||||||||||||||
| Increase/(Decrease) in Accounts payable | ( | ( | ||||||||||||||||||
| Increase/(Decrease) in Accounts payable - related party | ( | |||||||||||||||||||
| Increase/(Decrease) in Operating lease liabilities | ( | ( | ( | |||||||||||||||||
| Increase/(Decrease) in Accrued arbitration expenses | ||||||||||||||||||||
| Increase/(Decrease) in Accrued income tax expense | ( | |||||||||||||||||||
| Increase/(Decrease) in Accrued expenses and other current liabilities | ||||||||||||||||||||
| Net cash provided by operating activities | ||||||||||||||||||||
| Cash flows from investing activities: | ||||||||||||||||||||
| Acquisitions of property and equipment | ( | ( | ( | |||||||||||||||||
| Purchase of restricted short-term investment | ( | |||||||||||||||||||
| Cash related to sale of business | ( | |||||||||||||||||||
| Proceeds from restricted short-term investment | ||||||||||||||||||||
| Payments for acquisitions of businesses, net of cash acquired | ( | |||||||||||||||||||
| Cash related to asset acquisition | ( | |||||||||||||||||||
| Cash related to deconsolidation of Real Estate Entities | ( | |||||||||||||||||||
| Net cash used in investing activities | ( | ( | ( | |||||||||||||||||
| Cash flows from financing activities: | ||||||||||||||||||||
| Proceeds from lines of credit | ||||||||||||||||||||
| Proceeds from notes payable | ||||||||||||||||||||
| Proceeds from convertible notes | ||||||||||||||||||||
| Repayments of lines of credit | ( | ( | ( | |||||||||||||||||
| Repayments of notes payable | ( | ( | ( | |||||||||||||||||
| Repayments of finance leases | ( | ( | ( | |||||||||||||||||
| Proceeds from common stock issuance, net issuance costs | ||||||||||||||||||||
| Proceeds from exercise of warrants | ||||||||||||||||||||
| Cash related to stock repurchases and retirements | ( | |||||||||||||||||||
| Members' contributions | ||||||||||||||||||||
| Members' distributions | ( | ( | ( | |||||||||||||||||
| Net cash provided by (used in) financing activities | ( | ( | ||||||||||||||||||
| Net change in cash and cash equivalents | ( | |||||||||||||||||||
| Cash and cash equivalents - beginning of the period | ||||||||||||||||||||
| Restricted cash - beginning of period | ||||||||||||||||||||
| Cash and cash equivalents and restricted cash - beginning of period | ||||||||||||||||||||
| Cash and cash equivalents - end of period | ||||||||||||||||||||
| Restricted cash - end of period | ||||||||||||||||||||
| Cash and cash equivalents and restricted cash - end of period | $ | $ | ||||||||||||||||||
See accompanying notes to the consolidated financial statements.
63
NUTEX HEALTH INC.
NOTES TO CONSOLIDATED FINANCIAL STATEMENTS
Note 1 – Organization and Operations
Nutex Health Inc. (“Nutex Health” or the “Company”), is a physician-led, healthcare services and operations company with 26 hospital facilities (as of December 31, 2025) in 12 states (hospital division), and a primary care-centric, risk-bearing population health management division. Our hospital division implements and operates different innovative health care models, including micro-hospitals, specialty hospitals and hospital outpatient departments (“HOPDs”). The population health management division owns and operates provider networks such as independent physician associations (“IPAs”).
We employ 944 full-time employees, contract more than 280 doctors at our facilities and partner with over 3,600 physicians within our networks. Our corporate headquarters is based in Houston, Texas. We were incorporated on April 13, 2000 in the state of Delaware.
Merger of Nutex Health Holdco LLC and Clinigence Holdings, Inc. On April 1, 2022, the merger (the “Merger”) of Nutex Health Holdco LLC and Clinigence Holdings, Inc. (“Clinigence”) was completed pursuant to the Agreement and Plan of Merger (the “Merger Agreement”) entered on November 23, 2021 between Clinigence, Nutex Acquisition LLC, a Delaware limited liability company and wholly-owned subsidiary of Clinigence, Nutex, Micro Hospital Holding LLC (solely for the purposes of certain sections of the Merger Agreement), Nutex Health Holdco LLC and Thomas Vo, M.D., solely in his capacity as the representative of the equity holders of Nutex Health Holdco LLC.
In connection with the Merger Agreement, Nutex Health Holdco LLC entered into certain Contribution Agreements with holders of equity interests, including Dr. Vo, our Chairman and CEO (“Nutex Owners”), of subsidiaries and affiliates (the “Nutex Subsidiaries”) pursuant to which such Nutex Owners agreed to contribute certain equity interests in the Nutex Subsidiaries to Nutex Health Holdco LLC in exchange for specified equity interests in Nutex Health Holdco LLC (collectively, the “Contribution Transaction”). Nutex owners having ownership interests representing approximately 84 % of the agreed upon aggregate equity value of the Nutex Subsidiaries, agreed to contribute all or a portion of their equity interests, as applicable.
Pursuant to the Merger Agreement, each unit representing an equity interest in Nutex Health Holdco LLC issued and outstanding immediately prior to the effective time of the Merger but after the Contribution Transaction (collectively, the “Nutex Membership Interests”) was converted into the right to receive 3.571428575 shares of common stock of Clinigence, or an aggregate of 592,791,712 shares of common stock of Clinigence.
After completing the merger, Clinigence was renamed Nutex Health Inc.
2024 Reverse Stock Splits
1:15 Reverse stock split. The Company’s Board of Directors (the “Board”) determined to effect a reverse stock split of the common stock at a 1-for-15 ratio (the “1:15 Reverse Stock Split”) effective as of 11:59 pm Eastern time on April 9, 2024. The stockholders of the Company at its annual meeting on June 29, 2023 had approved a reverse stock split within a range of 1:2 and 1:15 to be effected within one year of approval at the discretion of the Board. The Company’s common stock began trading on The Nasdaq Capital Market on a post-1:15 Reverse Stock Split basis under the Company’s existing trading symbol “NUTX” at the open of the market on April 10, 2024. The 1:15 Reverse Stock Split was implemented for the purpose of regaining compliance with the minimum bid price requirement for continued listing of the Company’s common stock on The Nasdaq Capital Market.
1:10 Reverse stock split. In addition, the Board determined to effect a reverse stock split of the common stock at a 1-for-10 ratio (the “1:10 Reverse Stock Split”) effective as of 11:59 pm Eastern time on July 2, 2024. The Company’s stockholders, at the annual meeting on June 17, 2024, had approved a reverse stock split within a range of 1:2 and 1:16 to be effected within one year of approval at the discretion of the Board. This 1:10 Reverse Stock Split is in addition to the Company’s previous 1:15 Reverse Stock Split as discussed above. The Company’s common stock began trading on The Nasdaq Stock Market on a post-1:10 Reverse Stock Split basis under the Company’s existing trading symbol “NUTX” at the open of the market on July 3, 2024. The 1:10 Reverse Stock Split was also implemented for the purpose of regaining compliance with the minimum bid price requirement for continued listing of the Company’s common stock on The Nasdaq Capital Market.
64
As a result of both the 1:15 Reverse Stock Split and 1:10 Reverse Stock Split (collectively, the “2024 Reverse Stock Splits”) the number of shares of common stock outstanding was reduced to 5,511,452 950,000,000 .
Unless otherwise indicated, all authorized, issued, and outstanding stock and per share amounts contained in the accompanying consolidated financial statements have been adjusted to reflect the 2024 Reverse Stock Splits for all prior periods presented. Proportionate adjustments for the 2024 Reverse Stock Splits were made to the exercise prices and number of shares issuable under the Company’s equity incentive plans, and the number of shares underlying outstanding equity awards, as applicable.
The impacts of the 2024 Reverse Stock Splits were applied retroactively for all periods presented in accordance with applicable guidance. Therefore, prior period amounts are different than those previously reported. Certain amounts within the following tables may not foot due to rounding.
The following table illustrates changes in loss per share and weighted average shares outstanding, as previously reported prior to, and as adjusted subsequent to, the impact of the 2024 Reverse Stock Splits retroactively adjusted for the periods presented (in thousands, except share and per share data):
| Year Ended December 31, 2023 | |||||||||||||||||
| As Previously Reported | Impact of 2024 Reverse Stock Splits | As Revised | |||||||||||||||
| Loss attributable to common stockholders | $ | ( | $ | $ | ( | ||||||||||||
| Weighted average shares used to compute basic and diluted EPS | ( | ||||||||||||||||
| Loss per share - basic and diluted | $ | ( | $ | ( | $ | ( | |||||||||||
On July 24, 2024, Company received written notice (the “Compliance Notice”) from The Nasdaq Stock Market LLC (“Nasdaq”) informing the Company that it has regained compliance with Nasdaq Listing Rule 5550(a)(2), which requires that companies listed on the Nasdaq Stock Market maintain a minimum bid price of $1.00 per share. Nasdaq notified the Company in the Compliance Notice that, from July 3, 2024 to July 23, 2024, the closing bid price of the Company’s common stock had been $1.00 per share or greater and, accordingly, the Company had regained compliance with Nasdaq Listing Rule 5550(a)(2) and that the matter was now closed.
Note 2 - Summary of Significant Accounting Policies
Basis of presentation. The merger of Nutex Health Holdco LLC and Clinigence was accounted for as a reverse business combination with Nutex Health Holdco LLC as the accounting acquirer in accordance with ASC 805, Business Combinations, and Clinigence as the accounting acquiree.
The assets, including identified intangible assets, and liabilities of Clinigence were recorded at their fair values with the excess purchase price recorded as goodwill. The financial statements reflect the merger as the equivalent of the issuance of common stock for the net assets of Clinigence. The accounting for the merger did not affect the carrying values of the assets and liabilities of Nutex Health Holdco LLC.
Equity of the accounting acquirer, Nutex Health Holdco LLC, has been retroactively restated for the equivalent number of shares issued to the accounting acquirer. Similarly, shares outstanding and earnings per share have been also retroactively restated based on the equivalent number of shares issued to the accounting acquirer.
These financial statements present the Company’s consolidated financial condition and results of operations including those of majority-owned subsidiaries and variable interest entities (“VIEs”) for which we are the primary beneficiary.
The hospital division includes our healthcare billing and collections organization and hospital entities. In addition, we have financial and operating relationships with multiple professional entities (the “Physician LLCs”) and real estate entities (the “Real Estate Entities”). The Physician LLCs employ the physicians who provide services in our hospitals. These Physician LLCs are consolidated by the Company as VIEs because they do not have significant equity at risk to finance their activities independently. The Company is considered the primary beneficiary of these entities because (i) it has the power to direct the activities that most significantly affect their economic performance through its contractual and operational
65
oversight, and (ii) it has the obligation to absorb losses and the right to receive benefits that could be significant, as evidenced by the Company's historical practice of providing financial support during periods of cash shortfall and receiving the benefit of services provided.
The Real Estate Entities own the land and buildings used by the Company's hospital entities and lease these facilities to the Company. These entities have mortgage loans payable to third parties which are collateralized by the land and buildings. We consolidate certain Real Estate Entities as VIEs when our hospital entities are guarantors or co-borrowers under the related mortgage loans. In such cases, the Company is considered the primary beneficiary because it has the power to direct the entities' most significant activities and has the obligation to absorb losses and the right to receive benefits that could be significant to the Real Estate Entities.
While the Company holds no direct equity ownership in the consolidated Physician LLCs or certain Real Estate Entities, it is deemed to have an indirect economic interest through its contractual relationships with intermediary entities such as ER LLCs, which provide operational and functional support to the VIEs. As a result, 100 % of the equity in these VIEs is reflected as noncontrolling interests in the consolidated balance sheets and statements of operations. Certain of the Physician LLCs and Real Estate Entities are owned in part and, in some cases, controlled by related parties including members of our executive management team.
The population health management division includes our management services organizations. Additionally, Atlas Healthcare Physicians ("Atlas", formerly known as "Associated Hispanic Physicians of So. California"), an IPA entity that is not owned by us, is consolidated as a VIE of our wholly-owned subsidiary AHP Health Management Services (“AHP”). AHP is deemed the primary beneficiary of Atlas because it has the power to direct the significant activities of Atlas through a comprehensive management services agreement and has the right to receive substantially all of the economic benefits from its operations.
All significant intercompany balances and transactions have been eliminated in consolidation.
Use of estimates. The preparation of financial statements in conformity with GAAP requires management to make estimates and assumptions that affect the reported amount of assets and liabilities and disclosure of contingent assets and liabilities at the date of the financial statements and the reported amounts of revenues and expenses during the reporting period. Significant items subject to such estimates and assumptions include (i) estimates of net revenue and accounts receivable, (ii) fair value of acquired assets and liabilities in business combinations, (iii) impairment of long-lived assets and goodwill, (iv) estimate of valuation allowance against deferred taxes, (v) fair value of non-employee stock-based compensation and (vi) Black-Scholes option model to compute fair value of warrant liability. Actual results could differ from those estimates. During the year ended December 31, 2024, a change in estimate occurred for estimates of net revenue and accounts receivable. See Note 4 – Revenue regarding changes in estimate in the Company’s revenue recognition process. Accounts receivable as of December 31, 2023 was $58.6 million.
Revenue recognition.
Hospital division – Our hospital division recognizes patient service revenue for contracts with patients, and in most cases, patients with out of network benefits with a third-party payor, such as, commercial insurance, workers compensation insurance or, in limited cases, Medicare/Medicaid. The Company’s performance obligations are to provide emergency health care services primarily on an outpatient basis. Patient service revenues are recorded at the amount that reflects the consideration that the Company expects to be paid for providing patient care. These amounts are net of appropriate discounts giving recognition to differences between the Company’s charges and reimbursement rates from third party payors.
Hospital revenues earned by the Company are recognized at a point in time when the services are provided to patients, net of adjustments and discounts. Because all the Company’s performance obligations relate to contracts with patients with a duration of less than one-year, certain disclosures are limited.
We are considered “out-of-network” with commercial health plans. As there are no contractual rates established with insurance entities, revenues are estimated based on the “usual and customary” charges allowed by insurance payors using historical collection experience, historical trends of refunds and payor payment adjustments (retractions). Revenue from the Medicare program is based on reimbursement rates set by governmental authorities. For insured patients, the transaction price is determined based on gross charges for services provided, reduced by adjustments provided to third-party payors, discounts and implicit price concessions provided primarily to uninsured patients in accordance with the Company’s
66
policy. For uninsured patients, the Company recognizes revenue based on established rates, subject to certain discounts and implicit price concessions. The Company is reimbursed from third party payors under various methodologies based on the level of care provided.
Patients who have health care insurance may also have discounts applied related to their copayment or deductible. Estimates of contractual adjustments and discounts are determined by major payor classes for outpatient revenues based on historical experience. The Company estimates implicit price concessions based on its historical collection experience with these classes of patients using a portfolio approach. The portfolios consist of major payor classes for outpatient revenue. Based on historical collection trends and other analyses, the Company concluded that revenue for a given portfolio would not be materially different than if accounting for revenue on a contract-by-contract basis.
Customer payments are due upon receipt of an explanation of benefits for insured patients or it is due upon receipt of the bill from the Company for uninsured payments. There is no financing component associated with payments due from insurers or patients. The collection of outstanding receivables from Medicare, Medicaid, managed care payors, other third-party payors and patients is the Company’s primary source of cash and is critical to operating performance. The primary collection risks relate to uninsured patient accounts, including patient accounts for which the primary insurance carrier has paid amounts covered by the applicable agreement, but patient responsibility amounts (deductibles and copayments) remain outstanding. Accounts are written off when all reasonable collection efforts have been performed.
For the year ended December 31, 2024, a change in estimate occurred for estimates of net revenue and accounts receivable. See Note 4 – Revenue regarding changes in estimate in the Company’s revenue recognition process.
Population health management division – The population health management division recognizes revenue for capitation and management fees for services to IPAs and physician groups monthly.
Capitation revenue consists primarily of capitated fees for medical services provided by physician-owned entities we consolidate as VIEs. Capitated arrangements are made directly with various managed care providers including HMOs. Capitation revenues are typically paid to us monthly in the period services are provided based on the number of enrollees selecting us as their healthcare provider. Capitation is a fixed payment amount per patient per unit of time paid in advance for the delivery of health care services, whereby the service providers are generally liable for excess medical costs.
We receive management fees that are based on gross capitation revenues of the IPAs or physician groups we manage. Revenue is recognized and payments are received monthly for our services. In addition, we provide consultant services that are charged as a flat fixed rate and recognized as revenue when the service is performed. Consultant services revenues represent a small portion of our total revenue.
Cash and cash equivalents. The Company considers all highly liquid investments with an original maturity of three months or less to be cash and cash equivalents. The Company has cash amounts, that were at times material, held in covered banking institutions in excess of the insured amounts, but does not deem the risk of loss to be likely.
The following table provides a reconciliation of cash and cash equivalents and restricted cash reflected on the consolidated balance sheets to the total amounts shown within the consolidated statements of cash flows for each year (in thousands):
| December 31, 2025 | December 31, 2024 | |||||||||||||
| Cash and cash equivalents | $ | $ | ||||||||||||
| Restricted cash | ||||||||||||||
| Cash, cash equivalents and restricted cash | $ | $ | ||||||||||||
67
Inventories. Inventories are comprised of medical supplies and pharmaceuticals used at the Company’s facilities. Inventories are measured at lower of cost or net realizable value, which includes the weighted average cost of medical supplies and pharmaceuticals. The carrying amount is assessed for net realizable value.
Intangible assets. Intangible assets include acquired technology, relationships, contracts and trademark intangibles each having definite lives. Indefinite lived intangible assets, such as a Certificate of Need, are not amortized but instead are assessed for impairment at least annually, or when certain indicators of impairment exist on an interim basis. Definite lived intangible assets are amortized using the straight-line method over the estimated lives of the respective assets.
Goodwill. Goodwill represents the excess of the fair value of the consideration conveyed in the acquisition over the fair value of net assets acquired. Goodwill is not amortized but instead is evaluated for impairment at the same time every year and when an event occurs or circumstances change such that it is more likely than not that impairment may exist.
Goodwill is tested for impairment at least annually by first performing a qualitative assessment to determine whether a quantitative goodwill test is necessary or by electing to forgo the qualitative assessment and perform the quantitative goodwill test. For the year ended December 31, 2025, the Company elected to perform a qualitative assessment of goodwill. Upon performing the qualitative assessment of goodwill, qualitative factors are assessed to determine whether it is more likely than not that the fair value is less than the carrying amount. For the years ended December 31, 2024 and 2023, we elected to perform a quantitative goodwill test which compared the estimated fair values of our reporting units to their respective carrying values. For the quantitative test, we used the income method to estimate the fair value of these assets, which was based on forecasts of the expected future cash flows attributable to the respective assets. Significant estimates and assumptions inherent in the valuations reflect a consideration of other marketplace participants, and include the amount and timing of future cash flows (including expected growth rates and profitability). Estimates utilized in the projected cash flows include consideration of macroeconomic conditions, overall category growth rates, competitive activities, Company business plans and the discount rate applied to the cash flows. Unanticipated market or macroeconomic events and circumstances may occur, which could affect the accuracy or validity of the estimates and assumptions.
Based on the results of the annual qualitative assessment of goodwill for the year ended December 31, 2025, we concluded it is not more likely than not that the fair value of the Population Health Management Division is less than the carrying amount and therefore, did not perform a quantitative goodwill test or record impairment.
On June 30, 2024, we recognized an impairment of goodwill of $3.2 million and the derecognition of goodwill of $0.5 million, both for the Population Health Management Division, related to the sale of Procare Health, Inc. ("Procare"), a wholly-owned subsidiary of Nutex. Procare was considered part of the Population Health Management Division. Prior to the sale of Procare, the Company recognized a goodwill impairment amount of $3.2 million. On the sale of Procare, the Company recognized the derecognition of goodwill of $0.5 million based on the remaining carrying amount of goodwill for the Procare business after impairment.
Due to the sale of Procare, the Company tested for impairment the remaining goodwill in the Population Health Management Division of $13.9 million. On June 30, 2024, we determined that the fair value of our Population Health Management Division was greater than its carrying value. Therefore, no No goodwill impairment was recognized for year ended December 31, 2025.
On December 31, 2023, we recognized an impairment loss of $1.1 million in a reporting unit within our Hospital Division for the closure of a facility in January 2024.
We believe the estimates and assumptions utilized in our impairment testing are reasonable and are comparable to those that would be used by other marketplace participants. However, actual events and results could differ substantially from those used in our valuations. To the extent such factors result in a failure to achieve the level of projected cash flows used to estimate fair value for purposes of establishing or subsequently impairing the carrying amount of goodwill and intangible assets, we may need to record additional non-cash impairment charges in the future.
Long-lived assets. Fixed assets are stated at cost. The Company assesses the valuation of components of its property and equipment and other long-lived assets whenever events or circumstances indicate that the carrying value might not be recoverable. The Company bases its evaluation on indicators such as the nature of the assets, the future economic benefit of the assets, any historical or future profitability measurements and other external market conditions or factors that may be
68
Stock-based compensation. We account for employee and non-employee stock-based compensation using the fair value method. Non-employee stock-based compensation is based on contractual obligations under the terms of the Contribution Agreement; see Note 12 - Stock-based Compensation. Compensation cost for equity incentive awards is based on the fair value of the equity instrument generally on the date of grant and is recognized over the requisite service period. Forfeitures are recognized as they occur.
The Company uses the Black-Scholes option pricing model to estimate the fair value of its stock options and warrants. The Black-Scholes option pricing model requires the input of highly subjective assumptions including the expected stock price volatility of the Company’s common stock, the risk-free interest rate at the date of grant, the expected vesting term of the grant, expected dividends, and an assumption related to forfeitures of such grants. Changes in these subjective input assumptions can materially affect the fair value estimate of the Company’s stock options and warrants.
Leases. Leases are capitalized on the Company’s balance sheet through recognition of a liability for the discounted present value of future fixed lease payments and a corresponding right-of-use (“ROU”) asset. The ROU asset recorded at commencement of the lease represents the right to use the underlying asset over the lease term in exchange for the lease payments. When readily determinable, the Company uses the interest rate implicit in a lease to determine the present value of future lease payments. For leases where the implicit rate is not readily determinable, the Company’s incremental borrowing rate is utilized. The Company calculates its incremental borrowing rate upon commencement of a lease, using a model that uses the U.S. Department of Treasury daily treasury yield curve and a rate spread suitable for the Company to estimate the rate of interest the Company would have to pay to borrow an amount equal to the total lease payments on a collateralized basis over a term similar to the lease. Majority of leases include options to extend a lease and the Company recognizes these options as part of ROU assets and lease liabilities. The Company’s lease agreements do not contain any material residual value guarantees or material restrictive covenants.
Convertible instruments. The Company bifurcates conversion options from their host instruments and account for them as free-standing derivative financial instruments when (a) the economic characteristics and risks of the embedded derivative instrument are not clearly and closely related to the economic characteristics and risks of the host contract, (b) the hybrid instrument that embodies both the embedded derivative instrument and the host contract is not re-measured at fair value under other GAAP with changes in fair value reported in earnings as they occur and (c) a separate instrument with the same terms as the embedded derivative instrument would be considered a derivative instrument.
The Company accounts for the conversion of convertible debt when a conversion option has been bifurcated using the general extinguishment standards. The debt and equity linked derivatives are removed at their carrying amounts and the shares issued are measured at their then-current fair value, with any difference recorded as a gain or loss on extinguishment of the two separate accounting liabilities.
The Company accounts for convertible debt that does not meet the criteria for equity treatment as a liability at amortized cost using the effective interest method. The Company classifies convertible debt based on the re-payment terms and conditions. Any discounts on the convertible debt and costs incurred upon issuance of the convertible debt are amortized to interest expense over the terms of the related convertible debt.
Noncontrolling interests. Noncontrolling interests (“NCI”) represent the portion of net assets in consolidated entities that are not owned by the Company. NCI is presented as a component of total equity in the consolidated balance sheets and the share of net income or loss attributable to noncontrolling interests is shown as a component of net income in the consolidated statements of operations.
Fair value measurements. Fair value is defined as the price that would be received to sell an asset or paid to transfer a liability in an orderly transaction between market participants. We classify fair value balances based on the classification of
69
the inputs used to calculate the fair value of a transaction. The three levels related to fair value measurements are as follows:
Level 1 — Observable inputs such as quoted prices in active markets for identical assets or liabilities.
Level 2 — Observable inputs other than quoted prices included in Level 1, such as quoted prices for similar assets and liabilities in active markets; quoted prices for identical or similar assets and liabilities in markets that are not active or other inputs that are observable or can be corroborated by observable market data.
Level 3 — Unobservable inputs that are supported by little or no market activity and that are significant to the fair value of the assets or liabilities. This includes certain pricing models, discounted cash flow methodologies and similar techniques that use significant unobservable inputs.
The estimated fair value of accounts receivable, restricted short-term investments, accounts payable, accrued expenses and notes payable approximate the carrying amount due to the relatively short maturity or time to maturity of these instruments. Accounts receivable and payable with related parties may not be arms-length transactions and therefore, may not reflect fair value.
Except for the initial valuation of intangible assets in connection with business combinations and the impairments of goodwill discussed above, there were no assets or liabilities that were re-measured at fair value on a non-recurring basis during the periods presented.
Advertising and marketing expense. The Company advertising and marketing expense consists of expense associated with marketing its brand and services via media outlets such as social media, billboards and publications. These costs are expensed as incurred and recorded in other operating costs and expenses in the consolidated statements of operations. Advertising and marketing expense for the years ended December 31, 2025, 2024 and 2023 totaled $6.5 million, $5.6 million and $5.5 million, respectively.
Income taxes. We account for income taxes under the asset and liability method, in which deferred income tax assets and liabilities are recognized for the tax consequences of temporary differences by applying enacted statutory tax rates applicable to future years to differences between the financial statement carrying amounts and the tax bases of existing assets and liabilities. The effect on deferred taxes of a change in tax rates is recognized in the consolidated statements of operations during the period in which the tax rate change becomes law. A valuation allowance against deferred tax assets is established if it is more likely than not that the related tax benefits will not be realized. In determining the appropriate valuation allowance, we consider the projected realization of tax benefits based on expected levels of future taxable income, available tax planning strategies and reversals of existing taxable temporary differences.
Each of the VIEs and other entities that are not wholly-owned are pass-through entities treated as partnerships for U.S. federal income tax purposes. No provision for federal income taxes is provided in the consolidated statements of operations for the noncontrolling interests associated with these entities.
We file tax returns in the U.S. and various state jurisdictions. With few exceptions, our returns for periods prior to 2019 are no longer subject to examination by tax authorities in these jurisdictions. We recognize the financial statement benefit of a tax position only after determining that the relevant tax authority would more likely than not sustain the position following an audit. If a tax position meets the “more likely than not” recognition criteria, accounting guidance requires the tax position be measured at the largest amount of benefit greater than 50% likely of being realized upon ultimate settlement. We record income tax related interest and penalties, if any, as a component in the provision for income tax expense.
Earnings (loss) per share – Basic earnings (loss) per share amounts are calculated by dividing income available to common shareholders by the weighted average number of shares of common stock outstanding. Diluted earnings (loss) per share amounts are calculated by dividing net income by the weighted average number of shares of common stock and common stock equivalents outstanding. Common stock equivalents represent shares issuable upon the assumed conversion of outstanding convertible notes, the assumed exercise of common stock options and warrants outstanding, unvested restricted stock units, and the effect of contingently issuable shares.
Business combinations. The Company accounts for business combinations under the acquisition method of accounting. Under this method, identifiable assets acquired, the liabilities assumed, and any noncontrolling interest are recognized at their estimated fair values at the acquisition date. The excess of purchase price over the fair value amounts assigned to the
70
assets acquired and liabilities assumed represents the goodwill amount resulting from the acquisition. Transaction costs are expensed as incurred.
Segment reporting. A public company is required to report descriptive information about its reportable operating segments. Operating segments, as defined, are components of an enterprise about which separate financial information is available that is evaluated regularly by the chief operating decision maker in deciding how to allocate resources and in assessing performance. Aggregation of similar operating segments into a single reportable operating segment is permitted if the businesses have similar economic characteristics and meet established criteria. The Company operates three reportable segments – the hospital division, the population health management division and the real estate division. The real estate division is comprised of the Real Estate Entities. Refer to Note 17 – Segment Information to the consolidated financial statements for information on the Company’s segments.
Variable interest entities. On an ongoing basis, as circumstances indicate the need for reconsideration, the Company evaluates each legal entity that is not wholly-owned by the Company in accordance with the consolidation guidance. The evaluation considers all of the Company’s variable interests, including equity ownership, as well as management services agreements. A legal entity is determined to be a VIE if it (i) does not have sufficient equity to finance its activities without additional subordinated financial support; (ii) the entity is established with non-substantive voting rights; or (iii) the equity holders, as a group, lack the characteristics of a controlling financial interest. If an entity is determined to be a VIE, the Company evaluates whether the Company is the primary beneficiary.
The primary beneficiary analysis is a qualitative analysis based on power and economics. The Company consolidates a VIE if both power and benefits belong to the Company – that is, the Company (i) has the power to direct the activities of a VIE that most significantly influence the VIE’s economic performance (power), and (ii) has the obligation to absorb losses of, or the right to receive benefits from, the VIE that could potentially be significant to the VIE (benefits). The Company consolidates VIEs whenever it is determined that the Company is the primary beneficiary.
Refer to Note 19 – Variable Interest Entities to the consolidated financial statements for information on the Company’s consolidated VIEs. If there are variable interests in a VIE but the Company is not the primary beneficiary, the Company may account for the investment using the equity method of accounting.
Stock repurchases and retirements. Historically, the Company accounted for stock retirements in accordance with ASC 505-30-30-8, which permitted the excess of the repurchase price over par or stated value to be allocated between additional paid-in capital ("APIC") and retained earnings, or alternatively, charged entirely to retained earnings. The allocation to APIC was subject to specific limitations based on prior retirements, net gains on sales of treasury stock, and related capital transactions for the same issue. In the fourth quarter of 2025, the Company completed a stock retirement transaction that is subject to updated transition guidance. Under the new policy, effective with this transaction and for all future stock retirements, any excess of the repurchase price over par or stated value will be reflected entirely as a deduction from APIC, provided that APIC does not become negative as a result. This change aligns the Company’s accounting treatment with the latest authoritative guidance and will be applied prospectively to all subsequent stock retirement activities.
Reclassifications. Financial statements presented for prior periods include reclassifications that were made to conform to the current year presentation. During 2024, the Company reclassified a portion of insurance expenses that were previously included in insurance expense to payroll expenses and other operating expenses within operating costs and expenses to better reflect the nature of those costs. In addition, the Company’s reverse stock split during 2024 resulted in a reclassification between common stock and APIC, with no net impact on total stockholders’ equity. These reclassifications had no effect on the Company’s total operating expenses, net income (loss), or cash flows for any period presented.
Recent accounting pronouncements - issued, not yet adopted
In November 2024, the FASB issued Accounting Standards Update ("ASU") 2024-03 – Income Statement-Reporting Comprehensive Income-Expense Disaggregation Disclosures (Subtopic 220-40): Disaggregation of Income Statement Expenses, requiring public entities to disclose additional information about specific expense categories in the notes to the financial statements on an interim and annual basis. ASU 2024-03 is effective for fiscal years beginning after December 15, 2026, and for interim periods beginning after December 15, 2027. The Company is currently evaluating the impact of this update.
71
In May 2025, the FASB issued ASU 2025-03 – Business Combinations (Topic 805) and Consolidation (Topic 810) - Determining the Accounting Acquirer in the Acquisition of a Variable Interest Entity, which revises the current guidance for determining the accounting acquirer for a transaction effected primarily by exchanging equity interests in which the legal acquiree is a VIE that meets the definition of a business. The amendments require that an entity consider the same factors that are currently required for determining which entity is the accounting acquirer in other acquisition transactions. ASU 2025-03 is effective for annual reporting periods beginning after December 15, 2026, and interim reporting periods within those annual periods. The Company is currently evaluating the impact of this update.
In November 2025, the FASB issued ASU 2025-08 – Financial Instruments - Credit Losses (Topic 326) - Purchased Loans, which expand the population of acquired financial assets subject to the gross-up approach in Topic 326. The amendments require loans (excluding credit cards) acquired without credit deterioration and deemed “seasoned” are purchased seasoned loans and accounted for using the gross-up approach at acquisition. ASU 2025-08 is effective for annual reporting periods beginning after December 15, 2026, and interim reporting periods within those annual periods. The Company is currently evaluating the impact of this update.
Recent accounting pronouncements - adopted
In December 2023, the FASB issued ASU 2023-09 – Income Taxes (Topic 740): Improvements to Income Tax Disclosures, which requires public entities, on an annual basis, to provide disclosure of specific categories in the rate reconciliation, as well as disclosure of income taxes paid disaggregated by jurisdiction. The Company adopted ASU 2023-09 during the year ended December 31, 2025. See Note 14 - Income Taxes for further detail.
In December 2025, the FASB issued ASU 2025-12 - Codification Improvements, which addresses suggestions received from stakeholders on the Accounting Standards Codification and makes other incremental improvements to generally accepted accounting principles. The Company adopted issue 10 of ASU 2025-12 during the year ended December 31, 2025. See Note 13 - Equity for further detail.
Note 3 – Mergers, Acquisitions and Divestitures
May 2025 Acquisition of controlling interest and consolidation
On May 2, 2025, the Company acquired a 51 % membership interest in an Indiana-based limited liability company (“May 2025 Acquiree”) for $2.3 million in cash. The Company determined that the May 2025 Acquiree, a Real Estate Entity, does not meet the definition of a business under ASC 805-10-55-5A. Accordingly, the transaction was accounted for as an asset acquisition under ASC 805-50. The identifiable assets acquired and liabilities assumed were recognized based on their relative fair values.
The Company concluded that the May 2025 Acquiree is a voting interest entity and that the Company has a controlling financial interest based on its majority voting rights and operational control. As such, the Company consolidated the May 2025 Acquiree under the voting interest model in accordance with ASC 810-10 as of the acquisition date.
As part of the transaction, a noncontrolling interest representing 49 % ownership in May 2025 Acquiree was recognized and is accounted for at cost. The noncontrolling interest does not have substantive participating rights.
The following table summarizes the net amount of May 2025 Acquiree's identifiable assets acquired and liabilities assumed as of the acquisition date (in thousands):
| Cash and cash equivalents | $ | |||||||
| Building and improvements | ||||||||
| Land | ||||||||
| Note payable assumed | ( | |||||||
| Net identifiable assets acquired | $ | |||||||
The following is a summary of the total consideration paid and the noncontrolling interest at cost (in thousands):
72
| Cash consideration transferred | $ | |||||||
Noncontrolling interest ( | ||||||||
| Total consideration transferred | $ | |||||||
Prior to the acquisition, a wholly owned subsidiary of the Company was the lessee under a financing lease with May 2025 Acquiree. Upon acquisition, the lease arrangement became an intercompany transaction within the consolidated group. Accordingly, the right-of-use asset and corresponding lease liability previously recognized under ASC 842 were eliminated in consolidation. For purposes of consolidation and in accordance with ASC 842, the effect of elimination is adjusted against the acquired asset's carrying amount determined as follows (in thousands):
| Building and improvements | $ | |||||||
| Lease derecognition upon consolidation | ( | |||||||
| Adjusted carrying value of building and improvements | $ | |||||||
No goodwill was recognized in connection with the acquisition, consistent with the guidance in ASC 805. The operating results of May 2025 Acquiree have been included in the Company’s consolidated financial statements beginning on the acquisition date.
September 2025 Asset Acquisition
On September 19, 2025, the Company, through its consolidated subsidiary acquired certain assets and assumed specific liabilities of a non-operational hospital facility located in St. Louis, Missouri ("September 2025 Acquiree") pursuant to an asset purchase agreement.
The Company determined September 2025 Acquiree does not meet the definition of a business under ASC 805-10-55-5A. Accordingly, the transaction was accounted for as an asset acquisition under ASC 805-50. The identifiable assets acquired and liabilities assumed were recognized based on their relative fair values.
In exchange for the assets acquired, the Company agreed to: (i) $5.8 million of seller note, (ii) real property and equipment lease obligations, (iii) make a deferred payment of $1.0 million over 10 years, and (iv) issue a 15 % membership interest in the consolidated subsidiary over a two-year period. The equity interest vests based on operational milestones, and is accounted for as purchase consideration rather than compensation, as no continuing services are required of the seller.
The following table summarizes the net amount of September 2025 Acquiree's identifiable assets acquired and liabilities assumed as of the acquisition date (in thousands):
| Furniture and fixtures | $ | |||||||
| Intangible asset - Certificate of Need | ||||||||
| Total identifiable assets acquired | $ | |||||||
The following table summarizes the total consideration for the acquisition (in thousands):
| Seller note | $ | |||||||
| Deferred payment obligation | ||||||||
| Equity interest in September 2025 Acquiree issued to seller | ||||||||
| Total purchase consideration | $ | |||||||
As a result of the transaction, the consolidated subsidiary was determined to be a VIE under ASC 810 due to insufficient equity at risk and its reliance on guarantees and financial support from the Company. The Company is the primary beneficiary of the consolidated subsidiary and consolidates its financial results. See Note 19 - Variable interest entities for additional information.
73
December 2025 Asset Acquisition
On December 17, 2025, the Company acquired land and an office building, together with related contractual rights, including existing tenant lease agreements and certain service contracts ("December 2025 Acquiree") pursuant to an asset purchase agreement, for $2.2 million in cash. The Company determined December 2025 Acquiree does not meet the definition of a business under ASC 805-10-55-5A. Accordingly, the transaction was accounted for as an asset acquisition under ASC 805-50. The identifiable assets acquired and liabilities assumed were recognized based on their relative fair values.
The following table summarizes the net amount of December 2025 Acquiree's identifiable assets acquired and liabilities assumed as of the acquisition date (in thousands):
| Land | $ | ||||
| Building | |||||
| Note payable | ( | ||||
| Net identifiable assets acquired | $ | ||||
No goodwill was recognized in connection with the acquisition, consistent with the guidance in ASC 805. The operating results of December 2025 Acquiree have been included in the Company’s consolidated financial statements beginning on the acquisition date.
2024 Divestitures
Sale of Procare Health, Inc. On May 30, 2024, the Company completed the sale of Procare, a wholly-owned subsidiary of Nutex, to an individual buyer. As consideration for the transaction, the buyer paid the Company $0.6 million, has assumed liabilities of $0.2 million and remitted Company stock of $0.1 million, recognized as a debit to common stock and APIC in the second quarter of 2024. During the second quarter of 2024, the Company recognized an intangible impairment of $2.1 million and a $3.2 million goodwill impairment loss. Upon completion of the sale, the Company recognized an insignificant loss on sale of business. The calculation of the loss on sale of business includes the derecognition of goodwill of $0.5 million, which was offset by consideration and other assets transferred.
Total revenue for Procare for the year ended December 31, 2025 and 2024 was $0.0 million and $0.4 million, respectively. Net loss (before impairment) for Procare for the year ended December 31, 2025 and 2024 was $0.0 million and $0.6 million, respectively. The Company does not deem this transaction to be significant.
Sale of Clinigence Health, Inc. On August 31, 2024, the Company completed the sale of Clinigence Health, Inc. (“Clinigence Health”), a wholly-owned subsidiary of Nutex to a third-party limited liability company. As consideration for the transaction, the buyer paid the Company $1.4 million ((i) $0.5 million paid at Closing subject to Adjustments as set forth in the Equity Purchase Agreement (EPA), (ii) $0.2 million paid on October 31, 2024; (iii) $0.2 million paid on December 31, 2024; (iv) $0.3 million paid in 2025 in two equal payments of $125 thousand each at the end of the first and second calendar quarters; and (v) the balance of $0.2 million paid within thirty (30 ) days after the end of the Holdback Period as defined in the EPA, minus any Holdback Adjustment chargeable against the Holdback Amount as defined in the EPA.). During the second quarter of 2024, the Company reclassified all assets of Clinigence Health to assets held-for-sale, within “Prepaid expenses and other current assets” in the condensed consolidated balance sheets. The value of the assets held-for-sale of $1.4 million were based on the EPA with the buyer. This resulted in an impairment loss of $1.4 million.
Upon completion of the sale, the Company recognized additional impairment losses of $0.4 million. The Company has received $0.6 million (a portion is the $0.5 million to be paid less working capital adjustments of $0.3 million).
Total revenue for Clinigence Health for the year ended December 31, 2025 and 2024 was $0.0 million and $0.9 million, respectively. Net loss (before impairment) for Clinigence Health for the year ended December 31, 2025 and 2024 is $0.0 million and $0.8 million, respectively. The Company does not deem this transaction to be significant.
74
2023 Acquisitions
In the third quarter of 2023, the Company acquired two Florida based IPAs for $0.8 million in cash, $0.8 million in Company shares, $0.3 million due to earn-out in 2023, and additional consideration of up to $0.4 million in cash and $0.5 million in Company shares if the acquired IPAs meet Medicare Lives thresholds in 2024 and 2025. Substantially all of the total purchase consideration was allocated to goodwill and identified intangible assets. The acquired IPAs are reported within our Population Health Management division. Management considers these acquisitions to be immaterial.
Note 4 – Revenue
We disaggregate revenue from contracts with customers into types of services or products, consistent with our reportable segments, as follows (in thousands):
| Year Ended December 31, | |||||||||||||||||
| 2025 | 2024 | 2023 | |||||||||||||||
| Hospital division revenue | $ | $ | $ | ||||||||||||||
| Population health management division revenue | |||||||||||||||||
| Total revenue | $ | $ | $ | ||||||||||||||
Hospital division revenue. We receive payment for facility services rendered from federal agencies, private insurance carriers, and patients. The Physician LLCs receive payment for doctor services from these same sources. On average, greater than 99 % of our net patient service revenue is paid by insurers and other non-patient third parties. The remaining revenues are paid by our patients in the form of copays, deductibles, and self-payment. We generally operate as an out-of-network provider and, as such, do not have negotiated reimbursement rates with insurance companies.
The following tables present the allocation of the transaction price with the patient between the primary patient classification of insurance coverage:
| Year Ended December 31, | ||||||||||||||||||||
| 2025 | 2024 | 2023 | ||||||||||||||||||
| Insurance | % | % | % | |||||||||||||||||
| Self pay | % | % | % | |||||||||||||||||
| Workers compensation | % | % | % | |||||||||||||||||
| Medicare/Medicaid | % | % | % | |||||||||||||||||
| Total | % | % | % | |||||||||||||||||
Change in estimate. The No Surprises Act (“NSA”) is a federal law that took effect January 1, 2022, to protect consumers from most instances of “surprise” balance billing. With respect to the Company, the NSA limits the amount an insured patient will pay for emergency services furnished by an out-of-network provider. The NSA addresses the payment of these out-of-network providers by group health plans or health insurance issuers (collectively, “insurers”). In particular, the NSA requires insurers to reimburse out-of-network providers at a statutorily calculated “out-of-network rate.” In states without an all-payor model agreement or specified state law, the out-of-network rate is either the amount agreed to by the insurer and the out-of-network provider or an amount determined through an independent dispute resolution (“IDR”) process.
The “qualifying payment amount” (QPA) is generally the median of the contracted rates recognized by the plan or issuer under such plans or coverage, respectively, on January 31, 2019, for the same or a similar item or service that is provided by a provider in the same or similar specialty and provided in the geographic region in which the items or service is furnished, with annual increases based on the consumer price index.
Under the NSA, insurers must issue an initial payment or notice of denial of payment to a provider within thirty days after the provider submits a bill for an out-of-network service. If the provider disagrees with the insurer’s determination, the provider may initiate a thirty business-day period of open negotiation with the insurer over the claim. If the parties cannot resolve the dispute through negotiation, the parties may then proceed to the IDR process.
75
Effective May 1, 2024, we engaged with a third-party IDR vendor to further support all of our out of network claims and determine which claims would be beneficial to arbitrate. The IDR process can take up to to five months to receive payments. In order to facilitate the dispute arbitration process, the Company incurred fees to the Centers for Medicare and Medicaid Services (“CMS”), the organizations that arbitrate the payment amount between the plan and providers known as independent dispute resolution entities (“IDRE”), and commission and fees to the third-party IDR vendor. IDRE fee payments represent refundable payments if arbitrations are successful. Therefore, these payments are reported as prepaid and other current assets in the consolidated balance sheets. The unsuccessful portion of the IDRE fee payments is written-off to contract services expense in the consolidated statements of operations at the time it is deemed uncollectible. Prepaid expenses related to IDRE fees was $20.9 million and $7.5 million as of December 31, 2025 and December 31, 2024, respectively. The balance for amounts billed from the third-party IDR vendor in accounts payable was $37.7 million and $2.2 million as of December 31, 2025 and December 31, 2024, respectively. Total accrued arbitration expenses were $49.7 million and $47.7 million as of December 31, 2025 and December 31, 2024, respectively.
For these reasons, we refined our estimates of variable consideration and revenue recognition timing, particularly to claims subject to arbitration. Our methodology now incorporates historical arbitration outcomes, payment history, and expected resolution timing in determining the expected transaction price for applicable claims. The result of this change in estimate increased our estimate of the ultimate amounts of accounts receivable we will collect for the current and prior periods moving forward. This change in estimate increased revenue and net income before tax by approximately $169.7 million and $112.0 million for the year ended December 31, 2024, respectively. Based on the weighted-average number of shares outstanding, the change increased basic and diluted earnings per share by approximately $22.00 and $20.39 for the year ended December 31, 2024, respectively. This change was applied prospectively beginning December 2024, as it reflects an improvement in the Company’s ability to estimate revenue based on additional experience and regulatory guidance.
Population health management division revenue. We recognize revenue for capitation and management fees for services to IPAs and physician groups. Capitation revenue consists primarily of capitated fees for medical services provided by physician-owned entities we consolidate as VIEs. Capitated arrangements are made directly with various managed care providers including HMOs. Capitation revenues are typically paid to us monthly in the period services are provided based on the number of enrollees selecting us as their healthcare provider. Capitation is a fixed payment amount per patient per unit of time paid in advance for the delivery of health care services, whereby the service providers are generally liable for excess medical costs. We receive management fees that are based on gross capitation revenues of the IPAs or physician groups we manage. Revenue is recognized and payments are received monthly for our services.
Note 5 - Property and Equipment
The principal categories of property and equipment are summarized as follows (in thousands):
| Useful Life (years) | December 31, | December 31, | |||||||||||||||
| 2025 | 2024 | ||||||||||||||||
| Buildings and improvements | $ | $ | |||||||||||||||
| Land | — | ||||||||||||||||
| Leasehold improvements | |||||||||||||||||
| Construction in progress | — | ||||||||||||||||
| Medical equipment | |||||||||||||||||
| Office furniture and equipment | |||||||||||||||||
| Computer hardware and software | |||||||||||||||||
| Vehicles | |||||||||||||||||
| Signage | |||||||||||||||||
| Total cost | |||||||||||||||||
| Less: accumulated depreciation | ( | ( | |||||||||||||||
| Total property and equipment, net | $ | $ | |||||||||||||||
We consolidate two Real Estate Entities in the Company. We acquired one Real Estate Entity in the second quarter of 2025. Two of the three Real Estate Entities are VIEs. Refer to Note 19 – Variable Interest Entities.
76
Depreciation and amortization of property and equipment for the years ended December 31, 2025, 2024 and 2023 totaled $6.7 million, $6.6 million and $6.0 million, respectively.
Due to the closures of four facilities, we recorded an impairment loss of $3.8 million for the year ended December 31, 2023 as the carrying value of the fixed assets associated with the facilities exceeded the fixed assets’ fair value.
Note 6 – Intangible Assets
Intangible assets. The following tables provide detail of the Company’s intangible assets (dollars in thousands):
| As of December 31, 2025 | Weighted Average Useful Life (in years) | Gross Carrying Amount | Accumulated Amortization | Net Carrying Amount | ||||||||||||||||||||||
| Amortizing intangible assets: | ||||||||||||||||||||||||||
| Member relationships | $ | $ | ( | $ | ||||||||||||||||||||||
| Trademarks | ( | |||||||||||||||||||||||||
| Total amortizing intangible assets | ( | |||||||||||||||||||||||||
| Indefinite-lived intangible asset - Certificate of Need | — | |||||||||||||||||||||||||
| Total intangible assets | $ | $ | ( | $ | ||||||||||||||||||||||
| As of December 31, 2024 | ||||||||||||||||||||||||||
| Amortizing intangible assets: | ||||||||||||||||||||||||||
| Member relationships | $ | $ | ( | $ | ||||||||||||||||||||||
| Trademarks | $ | ( | ||||||||||||||||||||||||
| Total | $ | $ | ( | $ | ||||||||||||||||||||||
Member relationships and trademarks are associated with existing entities in the population health management division.
During the third quarter of 2025, the Company acquired an indefinite-lived asset consisting of a state-issued Certificate of Need ("CON") associated with the operation of one of its hospital facilities. The Company determined that the CON has an indefinite useful life because it is renewable at minimal cost and is expected to contribute to cash flows indefinitely. Accordingly, the asset is not amortized, but is tested for impairment annually, or more frequently if events or changes in circumstances indicate that it is more likely than not that the asset is impaired. As of December 31, 2025, the carrying amount of the indefinite-lived intangible asset was $7.0 million.
Amortization of intangible assets for the years ended December 31, 2025, 2024 and 2023 totaled $1.3 million, $1.5 million and $1.6 million, respectively.
Certain intangible assets were impaired upon the sale of Procare and sale of Clinigence Health, totaling $3.9 million for the year ended December 31, 2024. See Note 3 - Mergers, Acquisitions and Divestitures for discussion over the sale of Procare and sale of Clinigence.
77
Due to the closure of a facility, we recorded an impairment loss of $0.7 million for the year ended December 31, 2023 as the carrying value of the facility’s license was greater than the license’s fair value. The following is the estimated aggregated amortization expense for each of the five succeeding fiscal years:
| Year ended December 31, | Amount | |||||||
| 2026 | $ | |||||||
| 2027 | ||||||||
| 2028 | ||||||||
| 2029 | ||||||||
| 2030 | ||||||||
| Thereafter | ||||||||
| Total amortizing intangible assets | $ | |||||||
Goodwill. The carrying amount of goodwill, by operating segment is as follows:
| Hospital Division | Population Health Management Division | Total | |||||||||||||||
| Balance as of December 31, 2023 | |||||||||||||||||
| Goodwill | $ | $ | $ | ||||||||||||||
| Accumulated impairment losses | ( | ( | ( | ||||||||||||||
| Goodwill, net, as of December 31, 2023 | |||||||||||||||||
| Purchase accounting adjustments | |||||||||||||||||
| Impairment of goodwill | ( | ( | |||||||||||||||
| Derecognition of goodwill | ( | ( | |||||||||||||||
| Goodwill, net, as of December 31, 2024 | |||||||||||||||||
| Impairment of goodwill | |||||||||||||||||
| Goodwill, net, as of December 31, 2025 | $ | $ | $ | ||||||||||||||
The purchase accounting adjustments of $0.5 million to the carrying amount of goodwill in the Population Health Management Division for the year ended December 31, 2024 relates to the acquisition of two Florida based IPAs in the third quarter of 2023 for which the allocation of goodwill is subject to revision based on final allocation of the purchase price to the identifiable assets and liabilities acquired.
The impairment of goodwill of $3.2 million and the derecognition of goodwill of $0.5 million, both for the Population Health Management Division, for the year ended December 31, 2024 relate to the sale of Procare Health, Inc., a wholly-owned subsidiary of Nutex. Procare was considered part of the Population Health Management Division. Prior to the sale of Procare, the Company recognized a goodwill impairment amount of $3.2 million. On the sale of Procare, the Company recognized the derecognition of goodwill of $0.5 million based on the remaining carrying amount of goodwill for the Procare business after impairment. See Note 3 - Mergers, Acquisitions and Divestitures for Procare sale.
Due to the sale of Procare, the Company tested for impairment the remaining goodwill in the Population Health Management Division of $13.9 million. On June 30, 2024, we determined that the fair value of our Population Health Management Division was greater than its carrying value. Therefore, no goodwill impairment was recognized for the quarter ended June 30, 2024. Additionally, the Company tested for annual goodwill impairment on October 1, 2024 and determined that no additional impairment was necessary.
On October 1, 2025, the Company performed its annual qualitative assessment of goodwill and concluded it is not more likely than not that the fair value of the Population Health Management Division is less than the carrying amount and therefore, did not perform a quantitative goodwill test or record impairment for the year ended December 31, 2025.
78
Note 7 – Accrued Expenses and Other Current Liabilities
Accrued expenses and other current liabilities consisted of the following (in thousands):
| December 31, | December 31, | ||||||||||
| 2025 | 2024 | ||||||||||
| Accrued wages and benefits | $ | $ | |||||||||
| Accrued supplier expenses | |||||||||||
| Accrued medical claims | |||||||||||
| Accrued other taxes | |||||||||||
| Accrued other | |||||||||||
| Total accrued expenses and other current liabilities | $ | $ | |||||||||
Note 8 – Debt
The Company’s outstanding debt is shown in the following table (dollars in thousands):
| Maturity Dates | Interest Rates | December 31, | December 31, | ||||||||||||||||||||
| 2025 | 2024 | ||||||||||||||||||||||
| Term loans secured by all assets | 12/2026 - 12/2030 | $ | $ | ||||||||||||||||||||
| Term loans secured by property and equipment | 09/2026 - 01/2030 | ||||||||||||||||||||||
| Term loan secured by deposits | 04/2025 | ||||||||||||||||||||||
| Line of credit secured by all assets | 01/2026 - 09/2026 | ||||||||||||||||||||||
| Term loans of consolidated Real Estate Entities | 05/2028 - 03/2037 | ||||||||||||||||||||||
| Seller note | 09/2035 | ||||||||||||||||||||||
| Deferred payment | 09/2035 | ||||||||||||||||||||||
| Unsecured convertible term notes | 10/2025 | ||||||||||||||||||||||
| Total | |||||||||||||||||||||||
| Less: unamortized issuance costs and discount | |||||||||||||||||||||||
| Less: short-term lines of credit | |||||||||||||||||||||||
| Less: current portion of long-term debt | |||||||||||||||||||||||
| Total long-term debt | $ | $ | |||||||||||||||||||||
Term loans and lines of credit. We have entered into private debt arrangements with banking institutions for the purchase of equipment and to provide working capital and liquidity through cash and lines of credit. Unless otherwise delineated above, these debt arrangements are obligations of Nutex and/or its wholly-owned subsidiaries. Consolidated Real Estate Entities have entered into private debt arrangements with banking institutions for purposes of purchasing land, constructing new emergency room facilities and building out leasehold improvements which are leased to our hospital entities. Nutex is a guarantor or, in limited cases, a co-borrower on the debt arrangements of the Real Estate Entities for the periods shown. Since the second quarter of 2022, we deconsolidated 18 Real Estate Entities after the third-party lenders released our guarantees of associated mortgage loans.
Certain outstanding debt arrangements require minimum debt service coverage ratios and other financial covenants. At December 31, 2025, we were in compliance with these debt arrangements; we had remaining availability of an aggregate of $5.3 million under outstanding lines of credit.
September 2025 Note Payable
In connection with the acquisition of September 2025 Acquiree, the Company, through its consolidated subsidiary, issued a seller note (the "September 2025 Note Payable") with a fair value of approximately $5.8 million. The September 2025 Note
79
Payable bears interest at 8 % per annum and is payable over 10 years, with the first principal and interest payment deferred for 12 months following the closing date. The September 2025 Note Payable was issued as consideration for the acquired assets, which primarily included a certificate of need with a fair value of $7.0 million. The September 2025 Note Payable represents long-term financing associated with the acquisition and is classified within on the consolidated balance sheet.
As part of the same transaction, the Company also agreed to make a deferred cash payment of $1.0 million, which was recognized at its present value at a 10 % discount rate. The deferred payment is payable in installments over 10 years, with the first payment due 19 months after the closing date of September 19, 2025. This obligation was included as part of the total purchase consideration and is reflected within long-term debt on the consolidated balance sheet.
December 2025 Note Payable
In connection with the acquisition of December 2025 Acquiree, the Company, through its consolidated subsidiary, entered into a note payable (the “December 2025 Note Payable”) with a fair value of approximately $7.9 million. The December 2025 Note Payable bears interest at the Secured Overnight Financing Rate (the “SOFR”) plus a margin of 2.63 % and is payable monthly over five years , with the first payment due in January 2026. The December 2025 Note Payable represents long-term financing associated with the acquisition and is classified within long-term debt on the consolidated balance sheet.
Pre-Paid Advance Agreement (convertible debt)
On February 15, 2024 the parties terminated the Pre-Paid Advance Agreement (the “PPA”) dated April 11, 2023, between the Company and YA II PN, Ltd. (“Yorkville”) pursuant to which the Company requested an advance of $15.0 million from Yorkville (a “Pre-Paid Advance”) purchased by Yorkville at 90 % of the face amount. Interest accrued on the outstanding balance of the Pre-Paid Advance at an annual rate equal to 0 % subject to an increase to 15 % upon events of default described in the PPA. The Pre-Paid Advance has a maturity date of 12 months from the Pre-Paid Advance Date.
The Company, at its option, has the right, but not the obligation, to repay early in cash a portion or all amounts outstanding under any Pre-Paid Advance, provided that the VWAP of the Common Stock is less than the Fixed Price during a period of ten consecutive trading days immediately prior to the date on which the Company delivers a notice to Yorkville of its intent and such notice is delivered at least 10 trading days prior to the date on which the Company will make such payment (“Optional Prepayment”). If elected, the Optional Prepayment includes a 6 % payment premium (“Payment Premium”).
On April 11, 2023, the Company requested a $15.0 million initial Pre-Paid Advance in accordance with the PPA. The net proceeds of $13.5 million received by the Company from Yorkville reflect a 10 % discount of $1.5 million in accordance with the PPA. Additionally, in connection with the PPA, the Company incurred $0.9 million in placement and legal fees, which the Company classifies as debt issuance costs. The discount and the debt issuance costs are reported as a direct deduction from the face amount of the PPA and are amortized monthly based on the effective interest rate method. The amortization of the discount and debt issuance costs are reported as interest expense in the consolidated statements of operations.
As a result of the Pre-Paid Advance, the Company (i) issued 0.2 million shares of common stock to Yorkville (23.1 million prior to the 2024 Reverse Stock Splits), reducing the principal of initial Pre-Paid Advance to $7.3 million, (ii) made Optional Prepayments of $8.2 million in accordance with the PPA, consisting of $7.7 million of principal and $1.0 million attributed to the Payment Premium offset by $0.5 million in debt discount amortization, and (iii) paid off in full the remaining outstanding balance of the PPA on January 30, 2024 and the parties terminated the Yorkville PPA on February 15, 2024.
September 2023 Convertible Debt Issuance
From September 2023 to December 2023, the Company conducted a private offering of convertible notes (“Unsecured Convertible Term Notes”) and six-year warrants (“Warrants”) to accredited investors (the “Holders”) as defined in Rule 501 under the 1933 Act and issued Unsecured Convertible Term Notes convertible into an aggregate of 89,751 shares (13,462,500 prior to the 2024 Reverse Stock Splits) of common stock at a conversion price of $60.00 per share ($0.40 prior to the 2024 Reverse Stock Splits) and Warrants to purchase an aggregate of 44,875 shares of common stock (6,731,250 prior to the 2024 Reverse Stock Splits) at an exercise price of $60.00 per share ($0.40 prior to the 2024 Reverse Stock Splits). We also issued Warrants for the purchase of 26,925 shares (4,038,750 prior to the 2024 Reverse Stock Splits) to the
80
placement agent. The Unsecured Convertible Term Notes matured on October 31, 2025 and the Warrants expire on December 31, 2029.
On March 26, 2024, the Company and the Holders agreed to amend the conversion price of the Unsecured Convertible Term Notes and exercise price of the Warrants to $30.00 each ($0.20 prior to the 2024 Reverse Stock Splits), resulting in the Unsecured Convertible Term Notes being convertible into 179,500 shares of common stock (26,925,000 prior to the 2024 Reverse Stock Splits), the Warrants exercisable for 89,750 shares of common stock (13,462,500 prior to the 2024 Reverse Stock Splits) and the placement agent Warrants exercisable for 53,850 shares of common stock (8,077,500 prior to the 2024 Reverse Stock Splits).
The Unsecured Convertible Term Notes bear an annual interest rate of 8 % if paid in cash or an annual interest rate of 10 % if paid in the form of common stock. The payment of interest in the form of common stock is at the discretion of the Company. When paid in common stock, the number of shares is equal to the quotient of the total accrued interest due divided by the last reported sale price of the Company’s common stock on the last complete trading day of such quarter. The Holders have the option, at any time, to convert all or any portion of the unpaid principal and interest outstanding in common stock at the conversion price of $30.00 per share. If the Company fails to pay the outstanding principal amount and all accrued interest within 30 days of the maturity date, the interest rate payable is adjusted to 12 %.
As of October 31, 2025, the remaining note holders of unsecured convertible term notes converted $4.9 million of principal and $0.1 million of interest to 165,030 shares of the Company's common stock, valued at $30.00 per share.
The Company appointed Emerson Equity LLC as placement agent for the September 2023 Private Offering. Per the Placement Agent Agreement, the Company agrees to pay (i) a cash commission equal to 10 % of the gross proceeds and (ii) warrants to purchase a number of Common Stock equal to 20 % of the total number of shares issuable upon conversion or exercise of the Unsecured Convertible Term Notes and Warrants, as applicable.
On December 16, 2025, the Company entered into an amendment of the terms of the September 2023 Private Offering. The amendment permits the Holder to exercise the Warrant on a cashless basis in the event that there is no effective registration statement available for the resale of the underlying securities. The amendment did not change the exercise price of the Warrant, which remains $30.00 per share, nor did it modify the number of Warrants issued. On December 16, 2025, pursuant to the amended terms, a Holder completed a cashless exercise of a Warrant and the Company issued 40,387 shares of its common stock.
The net carrying amount of the Unsecured Convertible Term Notes was zero as of December 31, 2025 and the weighted average effective interest rate on the convertible debt is 21.5 %. For the year ended December 31, 2025, interest expense was $1.1 million, comprising of $0.8 million in amortization expense and $0.3 million in accrued interest expense. The Unsecured Convertible Term Notes interest expense was $1.3 million for the year ending December 30, 2024, comprising of $0.9 million in amortization expense and $0.4 million in accrued interest expense.
Scheduled Maturities. Maturities of our outstanding debt are as follows (in thousands):
| Year ended December 31, | Amount | |||||||
| 2026 | $ | |||||||
| 2027 | ||||||||
| 2028 | ||||||||
| 2029 | ||||||||
| 2030 | ||||||||
| Thereafter | ||||||||
| Total | $ | |||||||
81
Note 9 – Leases
As Lessee
We have entered into hospital property, office and equipment rental agreements with various lessors including related parties. The following tables disclose information about our leases of property and equipment (in thousands):
| Year Ended December 31, | |||||||||||||||||
| 2025 | 2024 | 2023 | |||||||||||||||
| Operating lease cost | $ | $ | $ | ||||||||||||||
| Finance lease cost: | |||||||||||||||||
| Amortization of right-of-use assets | |||||||||||||||||
| Interest on lease liabilities | |||||||||||||||||
| Total finance lease cost | |||||||||||||||||
| Cash paid for amounts included in the measurement of lease liabilities: | |||||||||||||||||
| Operating cash flows from operating leases | |||||||||||||||||
| Operating cash flows from finance leases | |||||||||||||||||
| Financing cash flows from finance leases | |||||||||||||||||
| Net cash paid for amounts included in the measurement of lease liabilities | |||||||||||||||||
| Right-of-use assets obtained in exchange for lease obligations: | |||||||||||||||||
| Operating leases | |||||||||||||||||
| Finance leases | |||||||||||||||||
| Total right-of-use assets obtained in exchange for lease obligations | $ | $ | $ | ||||||||||||||
| Weighted average remaining lease term (years): | |||||||||||||||||
| Operating leases | |||||||||||||||||
| Finance leases | |||||||||||||||||
| Weighted average discount rate: | |||||||||||||||||
| Operating leases | % | % | % | ||||||||||||||
| Finance leases | % | % | % | ||||||||||||||
For the year ended December 31, 2025, the Company opened two facilities throughout the year. For both facilities, the Company recognized financing right-of-use (ROU) assets of $14.2 million related to the hospital property and equipment leases entered into as a result of the openings.
For the year ended December 31, 2024, the Company opened four facilities throughout the year. For three facilities, the Company recognized financing right-of-use (ROU) assets of $53.2 million related to the hospital property and equipment leases entered into as a result of the openings. For one facility, we recognized operating ROU assets of $16.7 million related to the hospital property lease entered into as a result of the facility opening. The recognized operating ROU asset also increased the weighted average discount rate.
Due to the closures of two facilities in January 2023 and two facilities in January 2024, we remeasured the one lease associated with a facility, recording a reduction to financing lease liabilities and financing right-of-use assets of $11.4
82
million as of December 31, 2023. After remeasurement, we recognized an impairment loss of $24.6 million for the year ended December 31, 2023 for the remaining carrying value of the right-of-use assets associated with the four facilities.
The following table shows minimum lease payments for the next five years (in thousands):
| Operating leases | Finance leases | |||||||||||||||||||||||||
| Minimum lease payments for the next five years: | Third-parties | Related parties | Third-parties | Related parties | ||||||||||||||||||||||
| 2026 | $ | $ | $ | $ | ||||||||||||||||||||||
| 2027 | ||||||||||||||||||||||||||
| 2028 | ||||||||||||||||||||||||||
| 2029 | ||||||||||||||||||||||||||
| 2030 | ||||||||||||||||||||||||||
| Thereafter | ||||||||||||||||||||||||||
| Total minimum lease payments | ||||||||||||||||||||||||||
| Less interest | ( | ( | ( | ( | ||||||||||||||||||||||
| Total lease liabilities | $ | $ | $ | $ | ||||||||||||||||||||||
As Lessor
We lease space to tenants under operating leases in an office building purchased in December 2025, see Note 3 for more details on the acquisition. The remaining rental terms range from approximately less than to six years . The leases provide for the payment of fixed base rents payable monthly. For the year ended December 31, 2025, lease income is included in Hospital division revenue in the consolidated statements of operations.
The following table shows future undiscounted cash flows under our contractual operating leases as of December 31, 2025 (in thousands):
| Year ended December 31, | Amount | |||||||
| 2026 | $ | |||||||
| 2027 | ||||||||
| 2028 | ||||||||
| 2029 | ||||||||
| 2030 | ||||||||
| Thereafter | ||||||||
| Total | $ | |||||||
Note 10 – Commitments and Contingencies
Litigation. The Company, its consolidated subsidiaries or VIEs may be named in various claims and legal actions in the normal course of business. Based upon counsel and management’s opinion, the outcome of such matters is not expected to have a material adverse effect on the consolidated financial statements.
Note 11 – Employee Benefit Plans
The Company’s employees aged 21 years and older are eligible to participate in the 401(k) Savings Plan. Salary deferrals are allowed in amounts up to 90 % of an eligible employee’s salary, not to exceed the maximum allowed by law. Two facilities contribute discretionary matches up to 5 -6 % of employees’ salaries. For the years ended December 31, 2025, 2024 and 2023, the two
83
Note 12 – Stock-based Compensation
In 2023, the stockholders of the Company approved the Amended and Restated Nutex Health Inc. 2023 Equity Incentive Plan (the “2023 Plan”), providing a total of 73,426 shares of Common Stock (11,013,943 prior to the 2024 Reverse Stock Splits) for issuance. Awards granted under the 2023 Plan may be incentive stock options, non-statutory stock options, restricted stock, restricted stock units, stock appreciation rights, performance units or performance shares. The awards are granted at an exercise price equal to the fair market value on the date of grant. The 2023 Plan is subject to annual increases on January 1st of each calendar year through January 1, 2033 of up to 1 % of the issued and outstanding shares of the Company’s Common Stock on the final day of the preceding calendar year, at the discretion of the Compensation Committee of our Board of Directors. During the second quarter of 2024, the number of shares to be issued under the 2023 Plan increased to 118,563 shares, most of which were issued as restricted stock units in June 2024, as discussed below. During the first quarter of 2025, the number of shares to be issued under the 2023 Plan increased to 55,115 shares, most of which were issued as restricted stock units in 2025, as discussed below. On July 14, 2025, stockholders of the Company approved an amendment to the 2023 Plan to increase the number of shares available for issuance under the Plan by 1,100,000 over the 10 year term of the Plan and to allow the number of shares available to automatically increase on January 1st of each calendar year through January 1, 2033 in an amount equal to 5 % of the number of outstanding shares at December 31 of the previous fiscal year, provided that the Board may decide that there shall be no or lesser increase.
Total stock-based compensation expense for the years ended December 31, 2025, 2024, and 2023 was $117.0 million, $16.6 million, and $2.8 million, respectively. Stock-based compensation expense includes amounts recognized for awards granted to employees for services rendered and non-employee arrangements, specifically the obligations for under-construction and ramping hospitals.
Obligations for under-construction and ramping hospitals. Under the terms of the Contribution Agreements, contributing owners of the under-construction hospitals and ramping hospitals (as determined on April 1, 2022), including Dr. Vo, our Chairman and CEO, are eligible to receive a one-time additional issuance of Company common stock.
•With respect to ramping hospitals that were acquired before the Merger, 24 months after the opening date (the “Determination Date”) of the applicable ramping hospital, such owner is eligible to receive such owner’s pro rata share of a number of shares of Company Common Stock equal to (i) the trailing twelve months earnings before interest, taxes, depreciation and amortization on the respective Determination Date, multiplied by (ii) 10 , (iii) minus the initial equity value received at the Closing of the Merger, and (iv) minus such owner’s pro rata share of the aggregate debt of the applicable ramping hospital outstanding as of the closing of the Merger. The number of additional shares to be issued will be determined based on the greater of (a) the price of the Company’s common stock at the time of determination or (b) $2.80 ($420.00 after the 2024 Reverse Stock Splits), as adjusted for any stock dividends, combinations, splits, recapitalizations and the like with respect to the Company’s common stock.
•With respect to under construction hospitals that were acquired before the Merger, contributing owners of under construction hospitals will be eligible to receive, on the Determination Date, such owner’s pro rata share of a number of shares of Company common stock equal to (a)(i) the trailing twelve months earnings before interest, taxes, depreciation and amortization as of the Determination Date multiplied by (ii) 10 , minus (iii) the aggregate amount of such owner’s capital contribution to the under construction hospital, minus (iv) such owner’s pro rata share of the aggregate debt of the applicable under construction hospital outstanding as of the Closing of the Merger, divided by (b) the greater of (i) the price of the Company common stock at the time of determination or (ii) $2.80 ($420.00 after the 2024 Reverse Stock Splits), as adjusted for any stock dividends, combinations, splits, recapitalizations and the like with respect to the Company’s common stock.
Ramping Hospitals are hospitals that at the time of the Merger had less than two years of operating results and as such were not considered mature hospitals. Under Construction Hospitals are hospitals that at the time of the Merger had not started accepting patients and as such did not have any operating results to serve as a basis for a valuation. At the time of the Merger, the parties agreed to additional issuances of common stock once these Ramping and Under Construction Hospitals had operated for at least 24 months, with the valuation to be based on trailing twelve months operating results determined at the end of such 24-month period (“Measurement Period”).
Pursuant to the Merger Agreement, and based on a valuation of $2.80 per share ($420.00 per share after the 2024 Reverse Stock Splits) of Clinigence common stock, each member interest in Nutex Holdco issued and outstanding immediately
84
prior to the effective time of the Merger was converted into the right to receive 3.571428575 shares of Clinigence common stock.
With respect to the Under Construction Hospitals, the aggregate number of shares of Clinigence common stock issued in the Merger to such Nutex Owners was equal to the aggregate capital contribution amounts received from the contributing Nutex Owners of the Under Construction Hospitals divided by (b) $2.80 per share ($420.00 per share after the 2024 Reverse Stock Splits) In addition, Nutex Health assumed all the debt of such Under Construction Hospitals outstanding at the closing of the Merger.
Under the Contribution Agreements, the Ramping and Under Construction Hospitals are entitled to additional shares of Company Common Stock. The number of additional shares depends on two main factors: the trailing twelve-month operating results of the particular hospital and the trading price of Nutex Health common stock, with both factors determined at the end of the applicable Measurement Period. There is no threshold of certain operating results to be achieved; however, there is a floor price of common stock to be applied to the calculation. The exact amount a Nutex Owner of a particular hospital will receive will accordingly depend on (i) the trailing twelve months of operating results of that particular hospital, minus the initial capital contribution and debt assumption, (ii) the current Nutex common stock trading price, and (iii) the ownership percentage in the hospital such Nutex Owner held prior to the Contribution Transaction and the Merger.
At the closing of the Merger, four hospitals were identified as Ramping Hospitals and 17 hospitals were identified as Under Construction Hospitals. Of the four Ramping Hospitals:
•The Measurement Period of two Ramping Hospitals ended on June 30, 2022, with no additional issuances of common stock due to operating results.
•The Measurement Period of one Ramping Hospital ended on June 30, 2023, with no additional issuances of common stock due to operating results.
•The Measurement Period of one Ramping Hospital ended on November 30, 2023, with no additional issuances of common stock due to hospital closure in February 2023.
Of the 17 Under Construction Hospitals:
•Seven hospitals with Measurement Periods ended on or before December 31, 2025.
•Three hospitals with Measurement Periods that end after December 31, 2025.
•Three hospitals with no defined Measurement Periods as these hospitals have not opened as of December 31, 2025.
•Four hospitals with no Measurement Period as these hospitals' development plans have been abandoned.
In the tables below, we show the number of shares issuable, the number of shares issued to date, and compensation expense recognized with respect to four hospitals with Measurement Periods that ended prior to the end of December 31, 2025.
Measurement Periods ending on or prior to December 31, 2025 (dollars in thousands):
| Number of Hospitals | End of Measurement Period | Number of Shares Issuable | Number of Shares Issued to Date | Inception-to-date Compensation Expense | Year-to-date 2025 Compensation Expense | |||||||||||||||||||||||||||
| 1 | February 28, 2023 | $ | $ | |||||||||||||||||||||||||||||
| 2 | February 29, 2024 | |||||||||||||||||||||||||||||||
| 1 | February 28, 2025 | |||||||||||||||||||||||||||||||
| 2 | June 30, 2025 | |||||||||||||||||||||||||||||||
| 1 | August 31, 2025 | |||||||||||||||||||||||||||||||
| 7 | $ | $ | ||||||||||||||||||||||||||||||
In the table below, we show the estimated number of shares issuable to three hospitals with Measurement Periods that end after December 31, 2025 and are operating, but showing a pro forma calculation as of December 31, 2025. Since we cannot
85
predict the future operating results of a particular hospital or the Nutex Health trading price at the end of such particular Measurement Period, the actual number of shares issuable to the Nutex Owners of such Hospital cannot be determined.
Measurement Periods ending after December 31, 2025 (dollars in thousands):
| Number of Hospitals | End of Measurement Period | Estimated Number of Shares Issuable | Estimated Compensation Expense | Inception-to-date Compensation Expense | Year-to-date 2025 Compensation Expense | |||||||||||||||||||||||||||
| 1 | March 31, 2026 | $ | $ | $ | ||||||||||||||||||||||||||||
| 1 | November 30, 2026 | |||||||||||||||||||||||||||||||
| 1 | December 31, 2026 | |||||||||||||||||||||||||||||||
| 3 | $ | $ | $ | |||||||||||||||||||||||||||||
The Company measures these obligations as liability-classified stock-based compensation at fair value (level 3) on each reporting date until settlement, with changes in fair value recognized in the consolidated statements of operations. The fair value of these awards is determined using Monte Carlo simulation, which incorporates inputs such as expected term, volatility, risk-free interest rate, dividend yield and the probability of achieving performance conditions. At December 31, 2025, the aggregate liability recorded for these obligations was $8.3 million as compared to $16.4 million at December 31, 2024. The change in fair value recognized in the consolidated statements of operations for the years ended December 31, 2025 and 2024 was $116.0 million and $16.2 million, respectively.
Options. The following table summarizes stock-based awards activity:
| Options Outstanding | Weighted Average Exercise Price | Weighted Average Remaining Contractual Life (Years) | |||||||||||||||
| Options outstanding at December 31, 2023 | $ | ||||||||||||||||
| Options exercised | |||||||||||||||||
| Options cancelled | ( | ||||||||||||||||
| Options outstanding at December 31, 2024 | $ | ||||||||||||||||
| Options exercised | |||||||||||||||||
| Options cancelled | ( | ||||||||||||||||
| Options outstanding at December 31, 2025 | $ | ||||||||||||||||
Options outstanding as of December 31, 2025 consisted of:
| Expiration Date | Number Outstanding | Number Exercisable | Exercise Price | |||||||||||||||||
| May 11, 2027 | ||||||||||||||||||||
| June 9, 2027 | ||||||||||||||||||||
| January 27, 2030 | ||||||||||||||||||||
| January 28, 2031 | ||||||||||||||||||||
| September 9, 2031 | ||||||||||||||||||||
| December 17, 2031 | ||||||||||||||||||||
| Total | ||||||||||||||||||||
Restricted Stock Units. On June 16, 2024, the Company issued 118,538 RSUs (1,184,946 prior to the 1:10 Reverse Stock Split) valued at $0.6 million to certain employees participating in the Company’s long-term incentive program. 39,514 RSUs vested on March 1, 2025, 39,514 RSUs will vest on March 1, 2026, and 39,510 will vest on March 1, 2027.
86
On March 10, 2025, the Company issued 60,365 RSUs valued at $2.5 million to certain employees participating in the Company’s long-term incentive program. 20,122 RSUs will vest on March 1, 2026, 20,122 RSUs will vest on March 1, 2027, and 20,123 will vest on March 1, 2028. On July 14, 2025, the Company issued 2,413 RSUs valued at $0.3 million to certain members of the Board of Directors, vesting on July 14, 2026.
For grants of restricted stock units, we recognize compensation expense over the applicable vesting period equal to the fair value of our common stock at grant date. Grants of restricted stock units generally vest one third per year on each of the first three anniversaries of the grant date. The following table summarizes the changes in restricted stock units during the years ended December 31, 2025 and 2024.
| Shares (in thousands) | Weighted Average Grant-Date Fair Value Per Share | ||||||||||
| Non-vested awards, December 31, 2023 | $ | ||||||||||
| Granted | |||||||||||
| Forfeitures | ( | ||||||||||
| Vested | ( | ||||||||||
| Non-vested awards, December 31, 2024 | $ | ||||||||||
| Granted | |||||||||||
| Forfeitures | ( | ||||||||||
| Vested | ( | ||||||||||
| Non-vested awards, December 31, 2025 | $ | ||||||||||
As of December 31, 2025 and 2024, we estimate $1.6 million and $0.6 million, respectively, of unrecognized compensation cost related to restricted stock units issued to our employees to be recognized over the weighted-average vesting period of 1.6 and 1.5 years, respectively.
Employee Stock Purchase Plan. In May 2023, the Board of Directors adopted the 2023 Employee Stock Purchase Plan (“2023 ESPP”), which was subsequently approved by the Company’s stockholders and became effective in June 2023. The 2023 ESPP authorizes the initial issuance of up to 33,333 shares (5,000,000 prior to the 2024 Reverse Stock Splits) of the Company’s common stock to eligible employees, who are entitled to purchase shares of common stock equal to 85 % of the closing price on the purchase date with accumulated payroll deductions. During the years ended December 31, 2025 and 2024, the Company issued 3,502 shares and 8,405 shares, respectively, under the 2023 ESPP.
Note 13 – Equity
We are authorized to issue up to a total of 950,000,000 0.001 one vote for each share held of record on all matters submitted to a vote of stockholders and to receive ratably in proportion to the shares of common stock held by them any dividends declared from time to time by the Board. Our common stock has no preferences or rights of conversion, exchange, pre-exemption or other subscription rights.
Common Stock Issued. Following is a discussion of common stock issuances during the periods presented:
Securities Purchase Agreement. On January 22, 2024, the Company entered into a Securities Purchase Agreement (the “Purchase Agreement”) with a single healthcare focused institutional investor for the sale by the Company of 444,445 shares (66,666,666 prior to the 2024 Reverse Stock Splits) of the Company’s common stock and warrants (the “Warrants”) to purchase 444,445 shares (66,666,666 prior to the 2024 Reverse Stock Splits) of the Company’s common stock. The shares and the warrants were issued separately and issued on a one -to-one ratio at a public offering price of $22.50 per share and accompanying warrant ($0.15 prior to the 2024 Reverse Stock Splits).
The Warrants have an exercise price of $22.50 per share ($0.15 prior to the 2024 Reverse Stock Splits), are exercisable immediately upon issuance and expire five years from the Closing Date. The Warrants may only be exercised on a cashless basis if there is no registration statement registering, or the prospectus contained therein is not available for, the issuance or
87
resale of shares of common stock underlying the Warrants to or by the holder. The holder of a Warrant is prohibited from exercising any such warrants to the extent that such exercise would result in the number of shares of common stock beneficially owned by such holder and its affiliates exceeding 4.99 % (or, upon election by the holder prior to the issuance of any Warrants, 9.99 %) of the total number of shares of common stock outstanding immediately after giving effect to the exercise. In the event of certain fundamental transactions, the holder of the Warrants will have the right to receive the Black Scholes Value of its Warrants calculated pursuant to a formula set forth in the Form of Warrant, payable either in cash or in the same type or form of consideration that is being offered and being paid to the holders of common stock.
The gross proceeds to the Company from the offering were $9.2 million after deducting the placement agent’s fees and other offering expenses of $0.8 million. The allocation of the proceeds was $7.7 million to warrant liability and $1.5 million to APIC.
The Company used the Black-Scholes option model to compute the fair value (level 3) of the Warrants, with inputs including volatility (approximately 120 %) and risk-free rate based on US Treasury yield curve rates. The Company classified the Warrants as liabilities due to certain contractual provisions and recorded $7.7 million in warrant liability on January 25, 2024.
Under the Purchase Agreement, if the Company, at any time while the Warrants are outstanding, combines (including by way of reverse share split) outstanding shares of common stock into a smaller number, then, on the tenth trading day following, the exercise price will be reduced, and only reduced, to the lesser of (i) the then exercise price and (ii) 100 % of the average of the volume weighted average prices for the ten trading day period immediately following. On April 26, 2024, as required under the terms of the Purchase Agreement in response to the 1:15 Reverse Stock Split, the exercise price was reduced from $2.25 per share to $0.68 per share based on a calculation based on the Company’s trading price as set forth in the Purchase Agreement. On July 23, 2024, in response to the 1:10 Reverse Stock Split, the exercise price was reduced from $6.80 per share to $5.34 per share.
All 444,445 Warrants were exercised in 2024 and the Company received $2.4 million in proceeds from Warrant exercises. For each exercise, the Company remeasured the Warrants based on the exercise date, recognized a gain or loss on warrant liability, and allocated the exercised portion of the warrant liability to APIC. The warrant liability balance was zero 0.0 million and $1.6 million loss on warrant liability, respectively.
Other Common Stock Issued. All issuances referenced below were unregistered and were exempt from the registration requirements of the Securities Act of 1933, as amended, under Section 4(a)(2).
•At the time of the Merger, Clinigence had 339,741 common shares outstanding (50,961,109 prior to the 2024 Reverse Stock Splits). These amounts are shown as issued by us in the presentation of consolidated financial statements as the accounting acquiror.
•In March 2023, we issued 6,667 common shares (1,000,000 prior to the 2024 Reverse Stock Splits) to Apollo Medical Holdings, Inc. for IPA managerial services. We recognized $1.9 million of stock-based compensation expense for this issuance.
•We issued 16,943 shares of common stock (2,541,511 prior to the 2024 Reverse Stock Splits) in 2023 and 64,746 shares of common stock in 2024 in connection with the acquisition of two Florida IPAs. See Note 3 - Mergers, Acquisitions and Divestitures for discussion of 2023 Acquisitions.
•We issued 142,348 shares of common stock (21,357,603 prior to the 2024 Reverse Stock Splits) in 2023 and 11,824 (1,773,645 prior to the 2024 Reverse Stock Split) shares of common stock in 2024 to Yorkville for PPA share conversions.
Common Stock Warrants. During the year ended December 31, 2024, as part of the Securities Purchase Agreement, the Company issued warrants to purchase 444,445 shares (66,666,666 prior to 2024 Reverse Stock Splits) of Common Stock at a strike price of $22.50 ($0.15 prior to the 2024 Reverse Stock Splits) for a period of five years . These warrants were exercised as of December 31, 2024.
88
Warrant activity is as follows:
| Warrants Outstanding | Weighted Average Exercise Price | Weighted Average Remaining Contractual Life (years) | |||||||||||||||
| Warrants outstanding at December 31, 2023 | $ | ||||||||||||||||
| Warrants issued | |||||||||||||||||
| Warrants amended | |||||||||||||||||
| Warrants exercised | ( | ||||||||||||||||
| Warrants outstanding at December 31, 2024 | $ | ||||||||||||||||
| Warrants issued | |||||||||||||||||
| Warrants amended | |||||||||||||||||
| Warrants exercised | ( | ||||||||||||||||
| Warrants expired | ( | ||||||||||||||||
| Warrants outstanding at December 31, 2025 | $ | ||||||||||||||||
Warrants outstanding as of December 31, 2025 consisted of:
| Expiration Date | Number Outstanding | Number Exercisable | Exercise Price | |||||||||||||||||
| February 26, 2026 | ||||||||||||||||||||
| July 31, 2026 | ||||||||||||||||||||
| May 31, 2027 | ||||||||||||||||||||
| September 30, 2029 | ||||||||||||||||||||
| October 31, 2029 | ||||||||||||||||||||
| November 30, 2029 | ||||||||||||||||||||
| December 31, 2029 | ||||||||||||||||||||
| Total | ||||||||||||||||||||
Share Repurchase Program. On August 14, 2025, the Board authorized a stock repurchase program (the "Repurchase Program") of up to $25.0 million of the Company’s common stock over the subsequent six months. Pursuant to the Repurchase Program, the Company may repurchase, from time to time, up to an aggregate of $25.0 million of its outstanding shares of common stock, exclusive of any fees, commissions or other expenses related to such repurchases. The Repurchase Program permits the Company to repurchase shares of common stock at any time or from time to time at management’s discretion in open market transactions made in accordance with the provisions of Rule 10b-18 and/or Rule 10b5-1 under the Securities Exchange Act of 1934, as amended, privately negotiated transactions or by other means in accordance with applicable securities laws. The Repurchase Program authorization does not obligate the Company to acquire any shares of its common stock and may be amended, suspended or discontinued at any time.
During the year ended December 31, 2025, the Company repurchased 27,870 shares of common stock under the Repurchase Program in open market transactions at a weighted-average price of $177.73 for an aggregate purchase price of $5.0 million, inclusive of transaction costs. There were no repurchases during the year ended December 31, 2024. At December 31, 2025, we had approximately $20.0 million available under the Repurchase Program. In January 2026, subsequent to year end, the Company repurchased the remaining shares available under the Repurchase Program for an aggregate purchase price of $20.0 million, thereby completing the Repurchase Program. All shares repurchased under the
89
Repurchase Program were immediately retired in accordance with state laws and regulations. See Note 20 - Subsequent Events for additional information.
Note 14 – Income Taxes
On July 4, 2025, the One Big Beautiful Bill Act was signed into law, enacting significant changes to the U.S. tax code and coverage benefits for certain public healthcare insurance beneficiaries. The legislation includes several changes to federal tax law that generally allow for more favorable deductibility of certain business expenses beginning in 2025, including the reinstatement of 100% bonus depreciation. While certain provisions of the Act have and will continue to affect the timing of cash payments in 2025 and future years, there has not been nor do we anticipate a material impact on our financial statements.
Income tax expense (benefit) consisted of the following (in thousands):
| Year ended December 31, | |||||||||||||||||
| 2025 | 2024 | 2023 | |||||||||||||||
| Current taxes: | |||||||||||||||||
| Federal | $ | $ | $ | ( | |||||||||||||
| State | |||||||||||||||||
| Deferred taxes: | |||||||||||||||||
| Federal | ( | ( | |||||||||||||||
| State | ( | ( | |||||||||||||||
| Total income tax expense (benefit) | $ | $ | $ | ( | |||||||||||||
The items accounting for differences between income taxes computed at the federal statutory rate and the provision recorded for income taxes were as follows (in thousands):
| Year ended December 31, | ||||||||
| 2025 | ||||||||
| Tax Rate (%) | ||||||||
| US Federal statutory tax rate | $ | |||||||
State and local income taxes, net of federal income tax effect(1) | ||||||||
| Changes in valuation allowances | ( | ( | ||||||
| Noncontrolling interest | ( | ( | ||||||
| Stock compensation | ||||||||
| Other permanent adjustments | ||||||||
| Nontaxable or nondeductible items | ||||||||
| Other adjustments | ||||||||
| Total income tax expense | $ | |||||||
1.For 2025, state taxes in Arkansas, New Mexico and Oklahoma made up the majority (greater than 50%) of the tax effect in this category.
90
| Year ended December 31 | |||||||||||
| 2024 | 2023 | ||||||||||
| Income taxes computed at the federal statutory rate | $ | $ | ( | ||||||||
| Effect of: | |||||||||||
| State taxes, net of federal benefits | ( | ||||||||||
| Income of flow-through entities | ( | ( | |||||||||
| Change in valuation allowance | ( | ||||||||||
| Non-deductible stock compensation | |||||||||||
| Non-deductible goodwill impairment expense | |||||||||||
| Worthless Stock deduction | ( | ||||||||||
| Other, net | ( | ||||||||||
| Total income tax expense | $ | $ | ( | ||||||||
Deferred tax assets and liabilities were as follows (in thousands):
| December 31, | |||||||||||
| 2025 | 2024 | ||||||||||
| Deferred tax assets: | |||||||||||
| Net operating loss carryforwards | $ | $ | |||||||||
| Capital loss carryforwards | |||||||||||
| Accrued liabilities | |||||||||||
| Accrued professional fees | |||||||||||
| ROU Liability | |||||||||||
| Stock-based compensation | |||||||||||
| Interest expense limitation | |||||||||||
| Other | |||||||||||
| Total deferred tax assets | |||||||||||
| Deferred tax liabilities: | |||||||||||
| Cash to accrual adjustments | ( | ||||||||||
| Property and equipment | ( | ( | |||||||||
| ROU Asset | ( | ( | |||||||||
| Deferred revenue | ( | ||||||||||
| Intangible assets | ( | ( | |||||||||
| Other | ( | ( | |||||||||
| Total deferred tax liabilities | ( | ( | |||||||||
| Net deferred tax assets before valuation allowance | ( | ||||||||||
| Valuation allowance | ( | ||||||||||
| Net deferred tax assets (liabilities) | $ | ( | $ | ||||||||
During 2025, Nutex concluded, based on applicable tax law, relevant authorities, and a decision from the Fifth Circuit in June of 2025 that its right to recognize revenue from HaloMD arbitration activities under the No Surprises Act was not sufficiently fixed for income tax purposes. As a result, the Company deferred the related revenue on its 2024 federal income tax return filed in October 2025. The resulting net balance sheet adjustment between the current tax payable and the deferred tax liability was a change in estimate and did not materially affect the Company’s 2025 effective tax rate.
As of December 31, 2025 the Company fully utilized its federal and state net operating losses. As of December 31, 2025 and 2024, the Company had a capital loss carryforward of $0.2 million and $4.5 million, respectively. Due to the uncertainty about the Company's ability to utilize the capital loss prior to the expiration date, the Company maintained a
91
valuation allowance against that deferred tax asset as of December 31, 2024. The expired capital loss was written off and the corresponding valuation allowance was reversed as of December 31, 2025.
Cash paid for income taxes, net of refunds, was $0.8 Cash paid for income taxes, net of refunds for the year ended December 31, 2025 was as follows (in thousands):
| Jurisdiction | Amount | |||||||
| Federal | $ | |||||||
| Arizona | ||||||||
| Arkansas | ||||||||
| California | ||||||||
| Florida | ||||||||
| Idaho | ||||||||
| Indiana | ||||||||
| Kansas | ||||||||
| Louisiana | ||||||||
| New Mexico | ||||||||
| Oklahoma | ||||||||
| Texas | ||||||||
| Wisconsin | ||||||||
| Total | $ | |||||||
Note 15 – Earnings (loss) per Share
The following is the computation of earnings (loss) per basic and diluted share (in thousands, except share and per share data):
| Year Ended December 31, | |||||||||||||||||
| 2025 | 2024 | 2023 | |||||||||||||||
| Basic and diluted earnings (loss) per share: | |||||||||||||||||
| Numerator: | |||||||||||||||||
| Net income (loss) attributable to common stockholders | $ | $ | $ | ( | |||||||||||||
| Denominator: | |||||||||||||||||
| Weighted average shares used to compute basic and diluted EPS | |||||||||||||||||
| Basic earnings (loss) per share: | $ | $ | $ | ( | |||||||||||||
| Diluted earnings (loss) per share: | |||||||||||||||||
| Numerator: | |||||||||||||||||
| Dilutive net income (loss) attributable to common stockholders | ( | ||||||||||||||||
| Denominator: | |||||||||||||||||
| Weighted average shares used to compute basic EPS | |||||||||||||||||
| Dilutive effect of convertible note | |||||||||||||||||
| Dilutive effect of common stock warrants | |||||||||||||||||
| Dilutive effect of unvested restricted stock | |||||||||||||||||
| Dilutive effect of contingently issuable shares | |||||||||||||||||
| Weighted average shares used to compute diluted EPS | |||||||||||||||||
| Diluted earnings (loss) per share: | $ | $ | $ | ( | |||||||||||||
92
For the year ended December 31, 2023, the computation of diluted earnings per common share excludes the exercise of 27,581 common stock options (4,137,149 prior to the 2024 Reverse Stock Splits), 135,731 warrants (20,343,562 prior to the 2024 Reverse Stock Splits), 2,596 unvested restricted stock units (389,439 prior to the 2024 Reverse Stock Split) and 16,226 shares of common stock (2,433,908 prior to the 2024 Reverse Stock Splits) issuable upon conversion of outstanding convertible debt.
The dilutive effect of convertible debt was calculated using the if-converted method, whereas the dilutive effect of the assumed exercise of outstanding options, warrants, unvested restricted stock and contingently issuable shares was calculated using the treasury stock method.
Note 16 - Supplemental Cash Flows Information
| Year ended December 31, | |||||||||||||||||
| (In thousands) | 2025 | 2024 | 2023 | ||||||||||||||
| Cash paid for interest | $ | $ | $ | ||||||||||||||
| Cash paid for income taxes | |||||||||||||||||
| Non-cash investing and financing activities: | |||||||||||||||||
| Financed capital expenditures | |||||||||||||||||
| Acquisition of financing leases | |||||||||||||||||
| Exercise of warrants on a cashless basis | |||||||||||||||||
| Deconsolidation of Real Estate Entities | ( | ||||||||||||||||
| Debt converted to common stock | |||||||||||||||||
| Warrants issued with convertible debt | |||||||||||||||||
| Warrant liability related to common stock issuance | ( | ||||||||||||||||
| Non-cash effect of warrant exercises | |||||||||||||||||
| Payment for acquisition in common stock | |||||||||||||||||
| Common stock issued for Employee Stock Purchase Plan | |||||||||||||||||
| Common stock received in sale of business | ( | ||||||||||||||||
| Reclassification of related party payables to equity contributions | |||||||||||||||||
| Reversal of financing lease due to acquisition of lessor | ( | ||||||||||||||||
Note 17 – Segment Information
We report the results of our operations as three
The Company’s chief operating decision maker (“CODM”) is our Chief Executive Officer. The determination of our reporting segments was made based on our strategic priorities, which corresponds to the manner in which our CODM reviews and evaluates operating performance to make decisions about resources to be allocated. For our operating segments, the CODM uses segment operating income and segment income before tax to allocate resources (including financial and capital resources) in the annual and forecasting processes. On a monthly basis, the CODM considers month-to-month and budget-to-actual variances on a monthly basis for both measures when allocating resources to segments.
Other hospital division expenses include expenses such as facility-specific utilities, marketing and advertising, repairs and maintenance, and other tax expenses. Corporate costs primarily include expenses for support functions and salaries and benefits for corporate employees and are excluded from segment operating results.
Reportable segment information, including intercompany transactions, is presented below (in thousands):
93
| Year ended December 31, | |||||||||||||||||
| 2025 | 2024 | 2023 | |||||||||||||||
| Revenue from external customers: | |||||||||||||||||
| Hospital division | $ | $ | $ | ||||||||||||||
| Population health management division | |||||||||||||||||
| Total revenue | $ | $ | $ | ||||||||||||||
| Revenue from inter-segment activities (expense): | |||||||||||||||||
| Real estate division | $ | $ | $ | ( | |||||||||||||
| Segment expenses: | |||||||||||||||||
| Hospital division | |||||||||||||||||
| Payroll | $ | $ | $ | ||||||||||||||
| Contract services | |||||||||||||||||
| Medical supplies | |||||||||||||||||
| Other hospital division expenses | |||||||||||||||||
| Hospital division expenses | |||||||||||||||||
| Population health management division expenses | |||||||||||||||||
| Total segment expenses | $ | $ | $ | ||||||||||||||
| Depreciation and amortization: | |||||||||||||||||
| Hospital division | $ | $ | $ | ||||||||||||||
| Population health management division | |||||||||||||||||
| Real estate division | |||||||||||||||||
| Total depreciation and amortization | $ | $ | $ | ||||||||||||||
| Segment operating income (loss): | |||||||||||||||||
| Hospital division | $ | $ | $ | ||||||||||||||
| Population health management division | ( | ||||||||||||||||
| Real estate division | ( | ( | ( | ||||||||||||||
| Total segment operating income | $ | $ | $ | ||||||||||||||
| Consolidated operating income (loss) | |||||||||||||||||
| Total segment operating income | $ | $ | $ | ||||||||||||||
| Corporate and other costs | ( | ( | ( | ||||||||||||||
| Consolidated operating income (loss) | $ | $ | $ | ( | |||||||||||||
| Segment other income (loss): | |||||||||||||||||
| Hospital division | |||||||||||||||||
| Interest expense, net | $ | $ | $ | ||||||||||||||
| Other expense (income) | ( | ||||||||||||||||
| Hospital division income before income taxes | $ | $ | $ | ||||||||||||||
| Population health management division income (loss) before income taxes | ( | ||||||||||||||||
| Real estate division loss before income taxes | ( | ( | ( | ||||||||||||||
| Non-segment loss before income taxes | ( | ( | ( | ||||||||||||||
| Income (loss) before income taxes | $ | $ | $ | ( | |||||||||||||
| Capital expenditures: | |||||||||||||||||
| Hospital division | $ | $ | $ | ||||||||||||||
| Total capital expenditures | $ | $ | $ | ||||||||||||||
94
| December 31, | |||||||||||
| 2025 | 2024 | ||||||||||
| Assets: | |||||||||||
| Hospital division | $ | $ | |||||||||
| Population health management division | |||||||||||
| Real estate division | |||||||||||
| Total Assets | $ | $ | |||||||||
Note 18 – Related Party Transactions
Related party transactions included the following:
•The Physician LLCs employ the doctors who work in our hospitals. We have no direct ownership interest in these entities but they are owned and, in some instances, controlled by related parties including our CEO, Dr. Thomas Vo. The Physician LLCs are consolidated by the Company as VIEs because they do not have significant equity at risk, and we have historically provided support to them in the event of cash shortages and received the benefit of their cash surpluses.
The Physician LLCs had outstanding obligations to their member owners, who are also Company stockholders, totaling $0.0 million and $0.8 million at December 31, 2025 and 2024 are reported within accounts payable – related party in our consolidated balance sheets.
•Most of our hospital division facilities are leased from real estate entities which are owned by related parties. These leases are typically on a triple net basis where our hospital division is responsible for all operating costs, repairs and taxes on the facilities. Our obligations under these leases are presented in Note 9 - Leases. During the years ended December 31, 2025 and 2024, we made cash payments for these lease obligations totaling $22.4 million and $20.0 million, respectively. In addition, the building that housed the Company's corporate headquarters until February 2026 was owned by our CEO and leased to the Company, and lease payments under this arrangement are included in the lease obligation totals.
•We consolidate Real Estate Entities as VIEs when they do not have sufficient equity at risk and our hospital entities are guarantors or co-borrowers under their outstanding mortgage loans. Two of the three consolidated Real Estate Entities have mortgage loans payable to third parties which are collateralized by the land and buildings, and continue to be consolidated in our financial statements as of December 31, 2025. We have no direct ownership interest in these entities but they are owned and, in some instances, controlled by related parties including our CEO.
•Accounts receivable – related party included $6.0 million at December 31, 2025 and $4.3 million at December 31, 2024 due from noncontrolling interest owners of consolidated hospital facilities.
•Accounts payable – related party in our consolidated balance sheets included $1.1 million at December 31, 2025 and $0.0 million at December 31, 2024 for reimbursement of expenses incurred on our behalf.
In addition, we have outstanding obligations of contributions for facilities currently under construction totaling $2.0 million at December 31, 2025 and $1.6 million at December 31, 2024 reported within accounts payable-related party in our consolidated balance sheet.
•In connection with the closing of the Merger Agreement, our CEO, as an original owner, is entitled to receive his pro-rata share of 50 % of the aggregate distributable cash flow as determined by the Company once all debt and tax obligations are satisfied. For the years ended December 31, 2025 and 2024, total distributable cash paid was $3.4 million and $0.4 million, respectively.
95
Note 19 – Variable Interest Entities
The following tables provide the balance sheet amounts for consolidated VIEs (in thousands):
| December 31, 2025 | |||||||||||||||||||||||
| Real Estate Entities | Physician LLCs | Facility Entity | IPAs | ||||||||||||||||||||
| Current assets | $ | $ | $ | $ | |||||||||||||||||||
| Property and equipment, net | |||||||||||||||||||||||
| Other long-term assets | |||||||||||||||||||||||
| Total assets | $ | $ | $ | $ | |||||||||||||||||||
| Current liabilities | |||||||||||||||||||||||
| Long-term liabilities | |||||||||||||||||||||||
| Total liabilities | |||||||||||||||||||||||
| Equity | |||||||||||||||||||||||
| Total liabilities and equity | $ | $ | $ | $ | |||||||||||||||||||
| December 31, 2024 | |||||||||||||||||
| Real Estate Entities | Physician LLCs | IPAs | |||||||||||||||
| Current assets | $ | $ | $ | ||||||||||||||
| Property and equipment, net | |||||||||||||||||
| Total assets | $ | $ | $ | ||||||||||||||
| Current liabilities | |||||||||||||||||
| Long-term liabilities | |||||||||||||||||
| Total liabilities | |||||||||||||||||
| Equity | |||||||||||||||||
| Total liabilities and equity | $ | $ | $ | ||||||||||||||
The assets of each of the hospital facilities may only be used to settle the liabilities of that entity or its consolidated VIEs and may not be required to be used to settle the liabilities of any of the other hospital facilities, other VIEs, or corporate entities. Additionally, the assets of corporate entities cannot be used to settle the liabilities of VIEs. The Company has aggregated all Physician LLCs and certain Real Estate Entities into two categories above, because they have similar risk characteristics, and presenting distinct financial information for each VIE would not add more useful information.
Two Real Estate Entities are consolidated by the Company as VIEs because they do not have sufficient equity at risk and our hospital entities are guarantors of their outstanding mortgage loans. We have been working with the third-party lenders
96
to remove our guarantees of their outstanding mortgage loans. As these guarantees are released, the associated Real Estate Entity no longer qualifies as a VIE and is deconsolidated. As of December 31, 2025, two Real Estate Entities continue to be consolidated as VIEs in our financial statements.
Note 20 - Subsequent Events
The Company has evaluated subsequent events through the filing of this report. Management identified the following events that warrant disclosure:
•During January 2026, the Company repurchased 118,867 shares of common stock under the Repurchase Program in open market transactions at a weighted-average price of $168.65 for an aggregate purchase price of $20.0 million, inclusive of transaction costs, thereby completing the Repurchase Program.
* * * * *
97
Item 9. Changes in and Disagreements with Accountants on Accounting and Financial Disclosure
None.
Item 9A. Controls and Procedures
Evaluation of Disclosure Controls and Procedures. We maintain disclosure controls and procedures as that term is defined in Rules 13a-15(e) and 15d-15(e) under the Exchange Act that are designed to ensure that information required to be disclosed by the Company in reports that it files or submits under the Exchange Act, is recorded, processed, summarized and reported within the time periods specified in the SEC’s rules and forms, and that such information is accumulated and communicated to our management, including our Chief Executive Officer (“CEO”) and our Chief Financial Officer (“CFO”), as appropriate, to allow timely decisions regarding required disclosures. Any controls and procedures, no matter how well designed and operated, can provide only reasonable assurance of achieving the desired control objectives. In accordance with Rule 13a-15(b) of the Exchange Act, we have evaluated, under the supervision of our CEO and our CFO, the effectiveness of disclosure controls and procedures as of December 31, 2025. Based on this evaluation, the Company concluded that our disclosure controls and procedures were effective as of December 31, 2025.
Management's Report on Internal Control over Financial Reporting. Management is responsible for establishing and maintaining adequate internal control over financial reporting and for assessing the effectiveness of internal control over financial reporting. The Company has designed its internal control over financial reporting to provide reasonable assurance on the reliability of financial reporting and the preparation of the consolidated financial statements in accordance with U.S. generally accepted accounting principles.
The Company’s internal control over financial reporting includes those policies and procedures that:
•Pertain to the maintenance of records that, in reasonable detail, accurately and fairly reflect the Company’s transactions and dispositions of the Company’s assets;
•Provide reasonable assurance that transactions are recorded as necessary to permit preparation of the consolidated financial statements in accordance with U.S. generally accepted accounting principles, and that receipts and expenditures of the Company are being made only in accordance with authorizations of the Company’s management and directors; and
•Provide reasonable assurance regarding prevention or timely detection of unauthorized acquisition, use, or disposition of the Company’s assets that could have a material effect on the consolidated financial statements.
Because of inherent limitations in internal control over financial reporting, such controls may not prevent or detect misstatements. Also, projections of any evaluation of the effectiveness of internal controls to future periods are subject to the risk that controls may become inadequate because of changes in conditions, or that the degree of compliance with the policies or procedures may deteriorate.
In connection with the preparation of the Company’s annual consolidated financial statements, management assessed the effectiveness of the Company’s internal control over financial reporting as of December 31, 2025, based on criteria established in the Internal Control-Integrated Framework (2013) issued by the Committee of Sponsoring Organizations of the Treadway Commission (the “COSO criteria”).
Based on this assessment, management has determined that our internal control over financial reporting was effective as of December 31, 2025.
Remediation of Material Weaknesses in Internal Control Over Financial Reporting. The material weaknesses that were previously disclosed as of December 31, 2024 were remediated as of December 31, 2025. See “Item 9A. Controls and Procedures – Management’s Report on Internal Control over Financial Reporting” and “Item 9A. Controls and Procedures – Remediation Plan” contained in the Company’s report on Form 10-K for the fiscal year ended December 31, 2024, and “Item 4. Controls and Procedures” contained in the Company’s subsequent quarterly reports on Form 10-Q during 2025, for disclosure of information about the material weaknesses that were reported as a result of the Company’s annual assessment as of December 31, 2024 and the remediation plan for those material weaknesses. As disclosed in the quarterly reports on Form 10-Q for the first three quarters of 2025, the Company has monitored the controls necessary to remediate the material weaknesses. Affected controls have been addressed and additional compensating controls added, as
98
appropriate, to address the material weaknesses. As of December 31, 2025, such controls were successfully tested, and the material weaknesses were remediated. The Company continues to refine its control environment on an ongoing basis.
Changes in Internal Control Over Financial Reporting. No change in our internal control over financial reporting occurred during the fiscal year ended December 31, 2025 that has materially affected, or is reasonably likely to materially affect, our internal control over financial reporting, other than continued monitoring of the controls implemented to remediate the material weaknesses disclosed in our Annual Report on Form 10-K for the fiscal year ended December 31, 2024.
Inherent Limitations on Effectiveness of Disclosure Controls and Procedures. Our senior members of management do not expect that our disclosure controls and procedures or our internal control over financial reporting will prevent all errors and all fraud. A control system, no matter how well designed and operated, can provide only reasonable, not absolute, assurance that the objectives of the control system are met. Because of its inherent limitations, internal control over financial reporting may not prevent or detect material misstatements. Also, projections of any evaluation of effectiveness to future periods are subject to the risk that controls may become inadequate because of changes in conditions, or that the degree of compliance with the policies or procedures may deteriorate.
Attestation Report of the Registered Public Accounting Firm. See the following page.
99
REPORT OF INDEPENDENT REGISTERED PUBLIC ACCOUNTING FIRM
Board of Directors and Shareholders
Nutex Health Inc.
Opinion on internal control over financial reporting
We have audited the internal control over financial reporting of Nutex Health Inc. (a Delaware corporation) and subsidiaries (the “Company”) as of December 31, 2025, based on criteria established in the 2013 Internal Control—Integrated Framework issued by the Committee of Sponsoring Organizations of the Treadway Commission (“COSO”). In our opinion, the Company maintained, in all material respects, effective internal control over financial reporting as of December 31, 2025, based on criteria established in the 2013 Internal Control—Integrated Framework issued by COSO.
We also have audited, in accordance with the standards of the Public Company Accounting Oversight Board (United States) (“PCAOB”), the consolidated financial statements of the Company as of and for the year ended December 31, 2025, and our report dated March 5, 2026 expressed an unqualified opinion on those financial statements.
Basis for opinion
The Company’s management is responsible for maintaining effective internal control over financial reporting and for its assessment of the effectiveness of internal control over financial reporting, included in the accompanying Management’s Report on Internal Control over Financial Reporting. Our responsibility is to express an opinion on the Company’s internal control over financial reporting based on our audit. We are a public accounting firm registered with the PCAOB and are required to be independent with respect to the Company in accordance with the U.S. federal securities laws and the applicable rules and regulations of the Securities and Exchange Commission and the PCAOB.
We conducted our audit in accordance with the standards of the PCAOB. Those standards require that we plan and perform the audit to obtain reasonable assurance about whether effective internal control over financial reporting was maintained in all material respects. Our audit included obtaining an understanding of internal control over financial reporting, assessing the risk that a material weakness exists, testing and evaluating the design and operating effectiveness of internal control based on the assessed risk, and performing such other procedures as we considered necessary in the circumstances. We believe that our audit provides a reasonable basis for our opinion.
Definition and limitations of internal control over financial reporting
A company’s internal control over financial reporting is a process designed to provide reasonable assurance regarding the reliability of financial reporting and the preparation of financial statements for external purposes in accordance with generally accepted accounting principles. A company’s internal control over financial reporting includes those policies and procedures that (1) pertain to the maintenance of records that, in reasonable detail, accurately and fairly reflect the transactions and dispositions of the assets of the company; (2) provide reasonable assurance that transactions are recorded as necessary to permit preparation of financial statements in accordance with generally accepted accounting principles, and that receipts and expenditures of the company are being made only in accordance with authorizations of management and directors of the company; and (3) provide reasonable assurance regarding prevention or timely detection of unauthorized acquisition, use, or disposition of the company’s assets that could have a material effect on the financial statements.
Because of its inherent limitations, internal control over financial reporting may not prevent or detect misstatements. Also, projections of any evaluation of effectiveness to future periods are subject to the risk that controls may become inadequate because of changes in conditions, or that the degree of compliance with the policies or procedures may deteriorate.
/s/ GRANT THORNTON LLP
Houston, Texas
March 5, 2026
100
Item 9B. Other Information
Trading Arrangements. During the fiscal quarter ended December 31, 2024, none of the Company’s directors or officers (as defined in Rule 16a-1(f) of the Securities Exchange Act of 1934, as amended) adopted terminated
Item 9C. Disclosures Regarding Foreign Jurisdiction that Prevent Inspections
None.
PART III
Item 10. Directors, Executive Officers and Corporate Governance
The information required by this Item is incorporated herein by reference to our Proxy Statement for the 2026 Annual Meeting of Stockholders, which is expected to be filed with the SEC within 120 days after the close of our fiscal year.
Securities Trading
The Company has adopted a securities trading policy that governs the purchase, sale, and/or other transactions of our securities by our directors, officers and employees and the Company itself. A copy of our insider trading policy is filed as Exhibit 19.1 to this Annual Report on Form 10-K for the fiscal year ended December 31, 2025.
Item 11. Executive Compensation
The information required by this Item is incorporated herein by reference to our Proxy Statement for the 2026 Annual Meeting of Stockholders, which is expected to be filed with the SEC within 120 days after the close of our fiscal year.
Item 12. Security Ownership of Certain Beneficial Owners and Management and Related Stockholder Matters
The information required by this Item is incorporated herein by reference to our Proxy Statement for the 2026 Annual Meeting of Stockholders, which is expected to be filed with the SEC within 120 days after the close of our fiscal year.
Item 13. Certain Relationships and Related Persons Transactions
The information required by this Item is incorporated herein by reference to our Proxy Statement for the 2026 Annual Meeting of Stockholders, which is expected to be filed with the SEC within 120 days after the close of our fiscal year.
Item 14. Principal Accountant Fees and Services
The information required by this Item is incorporated herein by reference to our Proxy Statement for the 2026 Annual Meeting of Stockholders, which is expected to be filed with the SEC within 120 days after the close of our fiscal year.
101
Item 15. Exhibits and Financial Statement Schedules
(a)The following documents are filed as part of this Report:
Management Report on Internal Control Over Financial Reporting | |||||
Reports of Independent Registered Public Accounting Firm (PCAOB ID Number 248 and 688) | |||||
102
(b)Exhibits:
Incorporated by Reference (File No. 001-41346) | ||||||||||||||||||||||||||
| Exhibit No | Description | Form | Exhibit | File Date | ||||||||||||||||||||||
| 2.1 | 8-K | 99.1 | Nov. 24, 2021 | |||||||||||||||||||||||
| 2.2 | 10-Q | 2.5 | Aug. 22, 2022 | |||||||||||||||||||||||
| 2.3 | 10-Q | 2.6 | Aug. 22, 2022 | |||||||||||||||||||||||
| 2.4 | 10-Q | 2.7 | Aug. 22, 2022 | |||||||||||||||||||||||
| 3.1 | 8-K | 3.1 | July 5, 2023 | |||||||||||||||||||||||
| 3.2 | 8-K | 3.2 | Apr. 4, 2022 | |||||||||||||||||||||||
| 3.3 | 8-K | 3.1 | Apr. 11, 2024 | |||||||||||||||||||||||
| 3.4 | 8-K | 3.1 | July 5, 2024 | |||||||||||||||||||||||
| 4.1 | 8-K | 10.3 | Nov. 22. 2019 | |||||||||||||||||||||||
| 4.2 | S-8 (333-267710) | 10.2 | Sep. 30, 2022 | |||||||||||||||||||||||
4.3* | ||||||||||||||||||||||||||
| 4.4 | Schedule 13D | 99.2 | Apr. 11, 2022 | |||||||||||||||||||||||
| 4.5 | 10-Q | 4.9 | Aug. 22, 2022 | |||||||||||||||||||||||
| 4.6 | Schedule 14A | Appendix A | May 19, 2023 | |||||||||||||||||||||||
4.7* | ||||||||||||||||||||||||||
| 4.8 | 8-K | 10.2 | July 5, 2023 | |||||||||||||||||||||||
| 4.9 | 10-K | 4.13 | Mar. 29, 2024 | |||||||||||||||||||||||
| 4.10 | 8-K | 4.1 | Jan. 24, 2024 | |||||||||||||||||||||||
4.11* | ||||||||||||||||||||||||||
| 10.1 | 8-K | 2.2 | Mar. 2, 2021 | |||||||||||||||||||||||
10.2* | ||||||||||||||||||||||||||
| 10.3 | 8-K | 10.1 | Apr. 4, 2022 | |||||||||||||||||||||||
103
| 10.4 | 8-K | 10.2 | Apr. 4, 2022 | |||||||||||||||||||||||
| 10.5 | 8-K | 10.2 | Jun. 10, 2022 | |||||||||||||||||||||||
| 10.6 | 10-Q | 10.11 | Aug. 22, 2022 | |||||||||||||||||||||||
| 10.7 | 10-Q | 10.12 | Aug. 22, 2022 | |||||||||||||||||||||||
| 10.8 | 8-K | 10.1 | Apr. 12, 2023 | |||||||||||||||||||||||
| 10.9 | 10-K | 10.25 | Mar. 29, 2024 | |||||||||||||||||||||||
| 10.10 | 10-K | 10.26 | Mar. 29, 2024 | |||||||||||||||||||||||
| 10.11 | 10-K | 10.27 | Mar. 29, 2024 | |||||||||||||||||||||||
| 10.12 | 10-K | 10.28 | Mar. 29, 2024 | |||||||||||||||||||||||
| 10.13 | 8-K | 10.1 | Feb. 9, 2024 | |||||||||||||||||||||||
| 10.14 | 10-K | 10.30 | Mar. 29, 2024 | |||||||||||||||||||||||
| 10.15 | 10-K | 10.31 | Mar. 29, 2024 | |||||||||||||||||||||||
| 10.16 | 8-K | 10.1 | Sep. 22, 2025 | |||||||||||||||||||||||
10.17* | ||||||||||||||||||||||||||
| 19.1 | 10-K | 19.1 | Mar. 31, 2025 | |||||||||||||||||||||||
| 21.1* | ||||||||||||||||||||||||||
| 23.1* | ||||||||||||||||||||||||||
23.2* | ||||||||||||||||||||||||||
| 31.1* | ||||||||||||||||||||||||||
| 31.2* | ||||||||||||||||||||||||||
| 32.1** | ||||||||||||||||||||||||||
| 32.2** | ||||||||||||||||||||||||||
| 97.1 | 10-K | 97.1 | Mar. 31, 2025 | |||||||||||||||||||||||
| 101.INS* | XBRL Instance Document - the instance document does not appear in the Interactive Data File because its XBRL tags are embedded within the Inline XBRL document. | |||||||||||||||||||||||||
| 101.SCH* | XBRL Taxonomy Extension Schema Document. | |||||||||||||||||||||||||
| 101.CAL* | XBRL Taxonomy Extension Calculation Linkbase Document. | |||||||||||||||||||||||||
| 101.DEF* | XBRL Taxonomy Extension Definition Linkbase Document. | |||||||||||||||||||||||||
| 101.LAB* | XBRL Taxonomy Extension Label Linkbase Document. | |||||||||||||||||||||||||
| 101.PRE* | XBRL Taxonomy Extension Presentation Linkbase Document. | |||||||||||||||||||||||||
| 104 | Cover Page Interactive Data File - The cover page interactive data file does not appear in the Interactive Data File because its XBRL tags are embedded within the Inline XBRL document. | |||||||||||||||||||||||||
104
*Filed herewith
**Furnished herewith. This exhibit shall not be deemed “filed” for the purposes of Section 18 of the Securities Exchange Act of 1934, as amended, or otherwise subject to the liability of that section. Further, this exhibit shall not be deemed to be incorporated by reference into any filing under the Securities Act of 1933, as amended, or the Securities Exchange Act of 1934, as amended.
105
SIGNATURES
Pursuant to the requirements of Section 13 or 15(d) of the Securities Exchange Act of 1934, the registrant has duly caused this report to be signed on its behalf by the undersigned thereunto duly authorized.
| March 5, 2026 | /s/ Thomas T. Vo | ||||
| Thomas T. Vo, M.D. | |||||
| Chief Executive Officer and Chairman of the Board (principal executive officer) | |||||
Pursuant to the requirements of the Securities Exchange Act of 1934, this report has been signed below by the following persons on behalf of the registrant and in the capacities and on the dates indicated.
| March 5, 2026 | /s/ Thomas T. Vo | ||||
| Thomas T. Vo, M.D. | |||||
| Chief Executive Officer and Chairman of the Board (principal executive officer) | |||||
| March 5, 2026 | /s/ Jon C. Bates | ||||
| Jon C. Bates | |||||
| Chief Financial Officer (principal financial officer and principal accounting officer) | |||||
| March 5, 2026 | /s/ Warren Hosseinion | ||||
| Warren Hosseinion | |||||
| President and Director | |||||
| March 5, 2026 | /s/ Kelvin Spears | ||||
| Kelvin Spears, M.D. | |||||
| Director | |||||
| March 5, 2026 | /s/ Cheryl Grenas | ||||
| Cheryl Grenas, R.N., M.S.N. | |||||
| Director | |||||
| March 5, 2026 | /s/ Michael L. Reed | ||||
| Michael L. Reed | |||||
| Director | |||||
| March 5, 2026 | /s/ Scott J. Saunders | ||||
| Scott J. Saunders | |||||
| Director | |||||
| March 5, 2026 | /s/ Frank Jaumot | ||||
Frank Jaumot | |||||
| Director | |||||
106